
Remember me
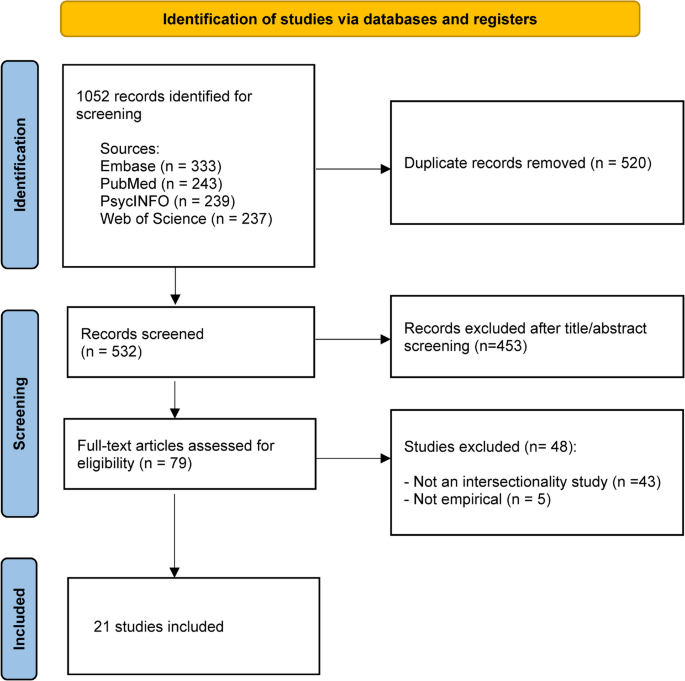


A comprehensive literature search was conducted in four electronic databases: Scopus, PubMed, Web of Science and CENTRAL, yielding a total of 6,169 records. Following import into COVIDENCE software, 2,695 duplicates were removed. This resulted in 3,474 unique records eligible for title and abstract screening. During screening, 3,435 studies were excluded for not meeting the inclusion criteria, leaving 39 studies underwent for full-text review. All full-text studies were retrieved, and 8 were subsequently excluded. Ultimately, 31 studies met all eligibility criteria and were included in the final qualitative synthesis (Fig. 1).
Fig. 1
PRISMA (Preferred reporting items for systematic reviews and meta-analyses) flowchart
The included studies spanned across all stages of the maternal continuum, with most conducted during pregnancy (n = 20), followed by postpartum (n = 15), and a few during preconception (n = 3). One study included both pregnant and contemplating pregnancy populations [26], and six studies followed pregnant women into the postpartum period [27,28,29,30,31,32]. A total of 7153 women were included across the studies, with individual sample sizes ranging from 24 to 1075 participants. Interventions varied in duration, spanning from 4-weeks to 12-months. Studies were conducted across multiple countries including six in the USA [28, 33,34,35,36,37], five in China [29, 31, 32, 38, 39], four in the Netherlands [26, 30, 40, 41], two in Taiwan [27, 42], one in Iran [38], two in Belgium [43, 44], two in Germany [45, 46], two in Malaysia [5, 47], and one in Pakistan [48], one in Brazil [40], Indonesia [49], Spain [50], Portugal [51], Sweden [52], Singapore [53], and Australia [54]. Of the 31 studies included, 12 featured fully digitalized interventions (38.7%), while the remaining 19 were partially digitalized (61.3%) (Supplementary Material 1).
Across the CDC-defined lifestyle outcomes, nutrition and physical activity were the most prevalent intervention targets, particularly during pregnancy and postpartum. Sleep outcomes were less commonly assessed, whereas smoking and alcohol consumption were rarely measured. Anthropometric indicators including body weight, BMI, fat percentage, and waist circumference, as well as those relevant to a reproductive stage (e.g., gestational weight gain (GWG), postpartum weight retention/loss) were also frequently measured. Limited interventions on insomnia, fertility, breastfeeding, GDM, gestational hypertension, and urinary incontinence were measured. Metabolic outcomes were well represented across all maternal stages (Fig. 2).
Fig. 2
Matrix heatmap of the outcome distribution across the reproductive lifespan (Preconception. pregnancy, postpartum)
PreconceptionOut of the 31 included studies, 3 focused specifically on the preconception period [26, 41, 47]. Two studies were conducted in the Netherlands [26, 41] and one in Malaysia [47] with sample sizes ranging from 254 to 848 participants. Mean baseline BMI varied among trials, ranging from 23.2 kg/m2 to 25.5 kg/m2, with participants classified in the overweight or obese category spanning from approximately one-quarter to nearly half. Two of the three studies included a uniform protocol comprised of a 24-week mHealth intervention targeting women undergoing IVF/ICSI, to improve nutrition [26, 41], smoking and alcohol parameters [41], compared to a lighter app version [26, 41]. Hanafiah et al. (2022) provided an e-health tool combining behavioral communication and lifestyle app-based challenges, compared to non-digital standard care [47].
NutritionImprovement in dietary-related parameters was assessed in all three trials [26, 41, 47]. Participants in the Smarter Pregnancy program noted improvements in the dietary risk score (DRS) compared to the control group (β = 0.75, 95% CI 0.18–1.34) following a 24-week personalized app program, largely due to improved vegetable intake (β = 0.55, 95% CI 0.25–0.86) [26]. Likewise, participants engaging with the IVF-targeted Smarter Pregnancy platform had a notably higher decrease in DRS at the 24-week assessment point, compared to the control group (β = 0.779 for women), with effects remaining sustained till 36 weeks (β = 0.816 for women; β = 0.639 for men) [41]. In Malaysia, the Jom Mama app plus counselling (three face-to-face and three via phone sessions) did not result in dietary differences in selected food items post-intervention compared to standard care over 33-weeks, except for a significantly reduced rice portion size (71.7% vs. 50.0%, p = 0.001) [47].
Physical ActivityThe Jom Mama app incorporated targeted physical activity prompts (e.g., brisk walking, stair use, planks), delivered over 33 weeks. Participants reported significantly greater vigorous job-related activity than controls post intervention(IG:259.9 vs. CG: 153.8 MET/week, p = 0.032), with no significant effects on other types of physical activity [47].
Smoking and AlcoholSmoking and alcohol consumption were addressed only in the study of Oostingh et al. (2020). After 24 weeks, women in the intervention group showed a statistically significant reduction in Lifestyle Risk Score (LRS, daily smoking use and weekly alcohol consumption) compared to the control group (β = 0.108, 95% CI 0.021–0.203), whereas no significant differences were observed after 36 weeks [41].
Health-Related Outcomes (Anthropometrics, Metabolic Outcomes, Fertility)In Jom Mama Program, changes in weight and BMI were modest and inconsistent. After the 33-week preconception intervention, there was no significant reduction in waist circumference (WC), despite high compliance in the intervention group, i.e. all women completing six sessions and downloading the app; however, weight and BMI increases were significantly lower in the intervention group (weight: +0.8 kg, BMI: +0.3 kg/m²) compared to the control group (weight: +1.6 kg, BMI: +0.7 kg/m²). In a subgroup analysis of participants classified as obese, the intervention group gained significantly less weight than the control group (0.1 vs. 1.7 kg, p = 0.023) [47]. Regarding metabolic parameters, fasting blood samples, including HbA1c, TC, HDL, TGs, alongside with standardized blood pressure measurements for Systolic (SBP) and Diastolic Blood Pressure (DBP) were used in both groups, with significant findings only observed in SBP between the intervention group (107.6, SD: 14.0) and control group (104.7, SD: 10.6, p = 0.031) [47]. Lastly, at 52 weeks follow-up, rates of successful pregnancies did not differ significantly between intervention and control groups [41] (Supplementary Material 1).
PregnancyOverall, pregnancy interventions showed consistent benefits for diet quality, physical activity and GWG among women with overweight/obesity, with mixed effects on metabolic markers. Twenty of the 31 studies focused on pregnancy -four in China [26, 29, 31, 32], three in the USA [28, 34, 37], two in the Netherlands [30, 40], two in Taiwan [27, 42], two in Iran [39, 55], and one in Brazil [48], Indonesia [49], Germany [46], Spain [50], Portugal [51], Malaysia [5], and Sweden [52], with sample sizes ranging from 24 to 306 participants and recruitment between 6th and 31st gestational weeks. The study duration varied with 5/20 trials lasting 6 weeks [5, 28, 31, 34, 37], 3/20 lasting 8 weeks [30,
Comments (0)