NECs of the pancreatobiliary tract are rare, aggressive malignancies characterized by rapid progression, early metastatic spread, and limited therapeutic options. The present case illustrates the clinical challenges associated with advanced NEC, as well as the potential value and limitations of PDOs for modeling tumor biology and their potential clinical implications.
Despite initial surgical resection followed by adjuvant chemotherapy, the patient experienced early disease relapses, consistent with the aggressive nature of NECs. Subsequent lines of systemic therapy showed limited efficacy, with only a temporary partial response observed during FOLFIRI treatment. This underscores the necessity for improved predictive biomarkers and functional models to guide personalized treatment strategies in NEC. As often reported for surgically resected NECs, the dismal outcome in this aggressive cancer calls for better and novel systemic therapy to improve survival. In a recent, large multicenter study, median NEC survival was a median of 7.4 months [19].
Currently, there is no consensus or established standard of care for sequencing systemic therapies in advanced NEC beyond the second line [9]. While NEC and well-differentiated Grade 3 NETs differ in their biology and treatment pathways, retrospective data show that an oxaliplatin/5-FU (FOLFOX) backbone can yield meaningful anti-tumor activity in heavily pretreated neuroendocrine malignancies [20].
Molecular profiling of the patient's tumor tissue revealed common alterations associated with NEC, including a TP53 mutation, RB1 loss, and a high Ki-67 value. These findings align with previous reports describing TP53 and RB1 inactivation as hallmark events in poorly differentiated NECs, contributing to impaired cell cycle control and uncontrolled cell division [21]. The absence of NET-associated mutations further supports the NEC characterization.
Although no NEC-specific targeted therapies are established in routine clinical practice, NGS may identify rare but potentially actionable alterations, including mismatch repair deficiency, high tumor mutational burden, and oncogenic drivers such as NTRK fusion and BRAF V600E mutation [22]. Several precision oncology trials use NGS to guide treatment recommendations or targeted therapy selection across different tumor types, including rare cancers [23, 24].
The neuroendocrine biomarker CgA remained consistently low in serum, including at recurrence. Studies have shown that CgA is rarely increased in blood for poorly differentiated NECs and is more commonly elevated in well to moderately differentiated NETs. It has also been found that CgA requires sufficient tumor size to be detectable in serum [25]. Carcinoembryonic antigen (CEA) levels in serum were significantly higher during third-line chemotherapy when a partial regression was detected radiologically. Cancer antigen 19–9 (CA 19–9) was within the normal range until it increased at radiological recurrence and remained elevated when the radiological partial regression was detected. This suggests that traditional serum biomarkers such as CgA, CEA, and CA 19–9 may not reliably reflect disease activity in poorly differentiated NEC.
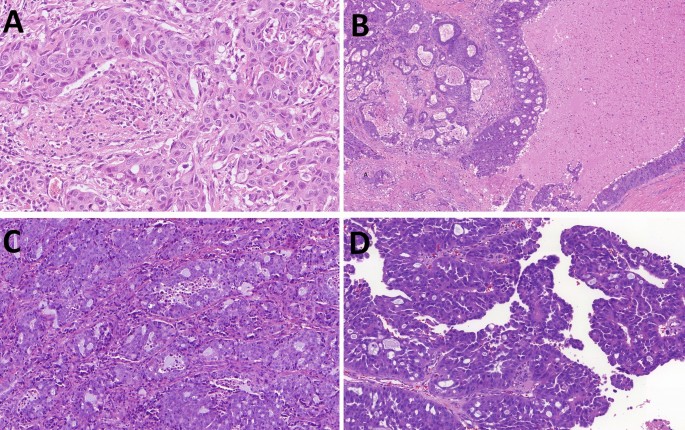
Establishing PDOs could enable comparison between the in vivo tumor and an ex vivo model system. The current PDO of NEC retained key phenotypic features of the primary tumor, including neuroendocrine marker expression and high proliferative activity, supporting their relevance as a preclinical model for NEC. The PDOs revealed the presence of an ALK mutation and concordant amplification of NTRK1, alterations also observed in the patient's tumor. Although these changes currently lack therapeutic relevance, this underscores the ability of the PDO to recapitulate key aspects of the patient’s tumor biology. Notably, the TP53 mutation exhibited a markedly lower allele frequency in the PDO than the patient tumor tissue, suggesting a selection of specific subclones during organoid establishment and propagation. Such differences should be considered when interpreting PDO-based functional studies or drug-screening results.
Metabolite profiling of tryptophan metabolism revealed changes in both patient serum and PDO-conditioned medium following tumor resection. IAA showed the highest postoperative fold change in serum (1.89), with lower levels before surgery and higher levels after tumor removal. By comparing the metabolite levels in NEC to previously published healthy controls [18], IAA and IPA are markedly lower in NEC. Notably, IAA levels were lower preoperatively than in any healthy control measured with this method (n = 32) but presented normal levels after tumor resection. Both IAA and IPA have been implicated in antitumor immunity and inhibition of tumor growth in other cancers [26,27,28], but there is a general lack of data on tryptophan metabolite levels in NEC. The normalization of IAA after tumor resection suggests that the tumor may have altered tryptophan metabolism, creating a microenvironment that is less favorable for antitumor immune activity.
Analysis of the PDO-conditioned media revealed a 70% increase in I3A compared with media without PDOs present. In contrast, I3A decreased by 46% in patient serum postoperatively. Together, the decrease in circulating I3A after tumor removal and the increase of I3A in the presence of PDOs suggest that the tumor may actively secrete I3A. Although traditionally considered microbiota-derived, recent evidence indicates that endogenous I3A also exists [29], explaining accumulation under sterile PDO conditions.
Collectively, these findings suggest that the tumor modulates tryptophan metabolism, both directly and indirectly, to influence antitumor immune responses in NEC, though the significance of these results remains uncertain given the single-patient design. Some serum changes, such as the postoperative rise in IAA, align with the expected recovery of host metabolism, whereas the PDO-specific increase in I3A represents a novel, potentially tumor-intrinsic phenomenon that warrants further investigation.
Some important limitations should be acknowledged. The method used to quantify tryptophan metabolites was validated for serum samples but not specifically for organoid culture media. Thus, matrix-related effects may influence metabolite measurements in PDO-conditioned media, and these findings should be regarded as exploratory. In addition, the PDO culture was compromised at later time points, showing limited recovery and progressive cell loss after thawing. Immunohistochemical and metabolomic analyses were performed during this period, which may have affected cellular composition, metabolic activity, and protein expression levels. As this is a single-patient report, generalizability is inherently limited, particularly regarding the demographic and biological variability across patient populations. Moreover, clonal selection during organoid establishment and propagation could contribute to differences in variant allele frequencies and copy number profiles between the patient tumor and PDO. Finally, interpretation of several genomic alterations was constrained by current clinical reporting guidelines, highlighting the gap between biological findings and clinical actionability in rare malignancies such as NEC.
Important limitations exist in current approaches to personalized therapy and are demonstrated in the current case discussion of an NEC. Despite comprehensive molecular profiling, no actionable therapeutic targets were identified. Similarly, although a PDO was successfully established and recapitulated several phenotypic and genomic characteristics of the patient's tumor, it did not reveal clinically actionable findings or therapeutic vulnerabilities that could have informed alternative treatment strategies.
Nevertheless, the PDOs provided a platform for investigating tumor biology in an ex vivo setting and revealed both shared and divergent molecular features compared with the original tumor, highlighting the strengths and limitations of this approach. These findings support the use of PDOs as a research tool to study NEC biology and explore potential therapeutic vulnerabilities. While emerging studies suggest that PDO-based approaches may have clinical relevance in selected settings, further evidence is needed to define their role in the management of NECs.
In conclusion, this case highlights the aggressive clinical course of pancreatobiliary NEC and demonstrates the feasibility of establishing PDOs from this rare tumor type. Although the PDOs preserved key molecular features of the original tumor, challenges remain. Future research should focus on validating the reproducibility of PDO models and establishing their clinical applicability in NECs.

Comments (0)