
Remember me
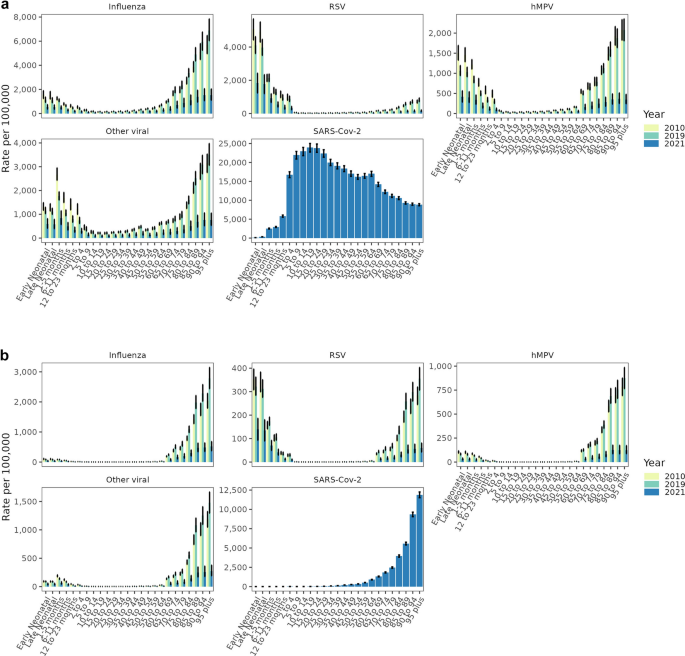
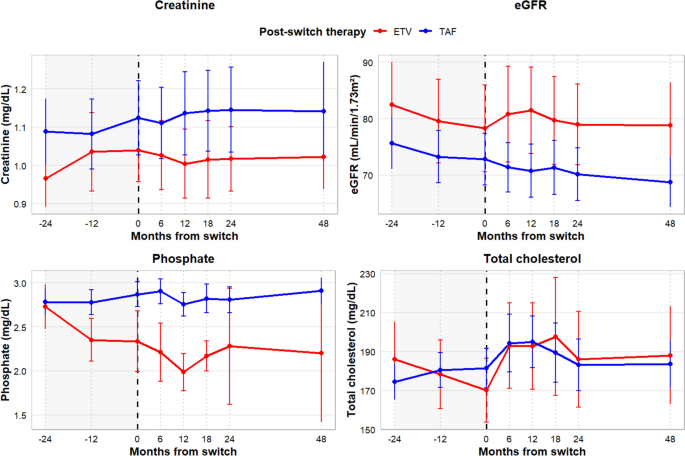
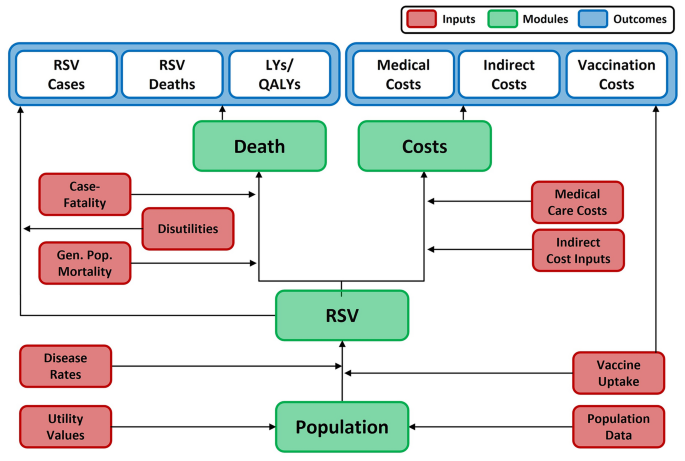
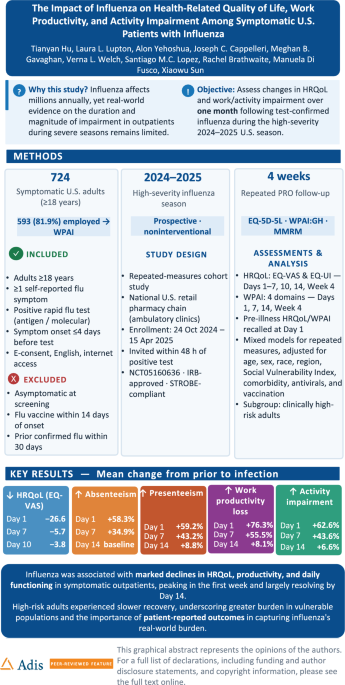
The study is planned as a two-stage adaptive design study (Fig. 1). Since there is no evidence for safety of oxfendazole in patients with LF, stage I of this study is designed as a sentinel stage with staggered ascending cohort to adequately monitor, control and evaluate the safety of the drug in patients with LF. Stage II is a parallel, randomised double-blind, placebo-controlled trial designed to evaluate the efficacy of two doses of oxfendazole as a dose ranging study i.e. 800 mg and 400 mg for 5 days.
Fig. 1 Intervention Description
Stage I is an open-label safety cohort at one of the study sites. This stage will enrol six participants, i.e. two groups of three participants in each sequence, on 400 mg and 800 mg doses of the investigational product (IP). All the drugs are to be administered orally, once daily for 5 days. Each subsequent dose cohort would start on or after 7 days of the first dose of the previous cohort.
Stage II is a double-blind, randomised, parallel-group, placebo-controlled, multiple-dose study in 66 participants with LF. Three parallel groups in a 1:1:1 ratio will receive five doses of either of placebo, 400 mg oxfendazole or 800 mg oxfendazole. Stage II may be adapted as a two-arm study with 400 mg of oxfendazole and placebo, depending on whether 800 mg oxfendazole used in stage I was associated with safety signals.
The IP used in the study is manufactured at a GMP-certified manufacturing facility (Syngene International Limited, India). The IP labels are approved by the Central Licensing Authority of India. The IP is labelled by a third-party vendor (Bilcare Research, India) to maintain blinding during the labelling process.
Sample SelectionThe participants will be identified through a field survey, where people in the age group of 18 to 60 years will undergo a rapid antigen blood test to detect circulating filarial antigen. If positive they will undergo a battery of biochemical investigations and USG for identification of live filarial worm at the hospital. Eligible and consenting participants will then be admitted on the night before dosing and a night blood smear taken for baseline mf status and load. The participant will then be randomised.
Eligibility CriteriaInclusion Criteria 1.Adults aged 1–60 years (both inclusive), of all genders, with a confirmed diagnosis of LF, with or without symptoms
2.Body weight ≥ 40 kg
3.Filarial test strip (FTS) positive (confirm presence of circulating filarial antigen, CFA)
4.Harbour at least one motile worm detected by USG
5.Agree to practice at least one highly effective method of contraception up till 3 months after randomisation
Exclusion Criteria 1.Symptoms, physical signs, vital signs or biological/laboratory signs suggestive of past or present systemic disorders, including but not limited to, cardiovascular, pulmonary, cutaneous, immunodeficiency, psychiatric disorders, drug/alcohol abuse and other abnormalities likely to interfere with the interpretation results of the test) or to significantly affect the study outcomes as judged by the investigator
2.Abnormal hepatic enzymes level that are more than 1.5 times the upper limit of normal values
3.Renal impairment confirmed by serum creatinine levels exceeding the upper limit of normal values
4.Clinical condition requiring chronic medication—diabetes, hypertension, chronic kidney disease, hypothyroidism, chronic respiratory disease, malignancy, human immunodeficiency virus (HIV), acquired immunodeficiency syndrome (AIDS); any other clinical condition requiring long-term medication (at the discretion of the physician)
5.Currently participating in any other drug trial or having participated in a trial in a period less than five half-lives of the investigational product
6.Any antifilarial drug intake in the previous month
7.Known HIV-positive status
8.Hemoglobin below 10 mg/dL at baseline
9.Epileptic seizures within the past 10 years
10.Acute and/or febrile illness requiring therapy within 14 days prior to baseline
11.Use of concomitant medications that are contraindicated with albendazole and/or known hypersensitivity to albendazole or any other ingredient in its formulation
12.Unacceptably high tobacco, alcohol or drug abuse
13.Pregnant (by urine pregnancy test) or breastfeeding women
14.Anyone who is planning to relocate to another state within the next 6 months
15.Participant with LF who needs surgical intervention
Investigational Products and Study TreatmentOxfendazole and placebo are being provided by DNDi in blister packs of 100-mg tablets.
Each participant will be in the study for a period of 6 months. The details of the timelines of enrolment, assessments and visits are provided is Table 1 (available in the online supplementary material).
Planned OutcomesPrimary Outcome 1.Parasitological cure (no adult worm motility) at 6 months identified by USG. It will be assessed as the proportion of participants with no worm motility at 6 months as seen on USG.
Secondary Outcomes 1.Parasitological cure (no adult worm motility) at 1 and 3 months identified by USG, assessed by the proportion of participants with no worm motility at 1 and 3 months as seen on USG.
2.Absolute value and mean change in microfilaria load at 1, 3 and 6 months as compared to the baseline.
3.Change in proportion of participants positive for circulating antigen at 1, 3 and 6 months as compared to the baseline.
4.The proportion of participants with AEs and SAEs within 6 months of starting the intervention.
5.The proportion of participants with change of laboratory parameters and vital signs as compared to the baseline recorded as AE.
6.Cmax, Tmax, AUC0–t, AUC0–inf, t1/2 of oxfendazole and its metabolites following first dose.
7.Average steady state plasma concentration, percentage fluctuation (variation between maximum and minimum concentration at steady state) (on day 5).
8.Accumulation following multiple (five) doses.
As the primary endpoint is the identification of filarial dance sign (FDS) on USG, which requires specialized expertise, all participating sonographers will complete a centralized, standardized training module led by a single expert radiologist prior to trial initiation. Study procedures, machine calibration, and scoring will be strictly governed by a study-specific standard operating procedure (SOP) dedicated to the uniform identification and grading of the FDS. Recognizing that individual worm counts are structurally impractical, the primary visual metric will be the tracking of distinct lymphatic nest counts. Furthermore, to verify true macrofilaricidal activity and eliminate false-positive endpoints, any initial observation of absent motility will mandate a confirmatory repeat USG within 24–72 h. Persistent lack of motility across both scans is strictly required to classify a nest as non-viable; otherwise, it will be classified as viable. Additionally, the statistical analysis plan includes a planned sensitivity analysis using this robust binary motility outcome to cross-verify primary efficacy endpoints.
To ensure participant safety following exposure to the IP, safety laboratory assessments, including liver function tests, renal function tests, hematology parameters and urinalysis, will be performed at day 3, day 6, and the 1-month follow-up visit from day 1 (the day of first dosing). These assessments will be conducted to monitor any potential treatment-related changes in organ function and to support the safety evaluation of oxfendazole.
Exploratory Outcomes: PK AnalysisBlood samples will be collected for measurement of plasma concentrations of oxfendazole, its primary metabolite as specified in Supplementary Table 1 (Schedule of Activities).
A total of 20 samples of approximately 3-mL volume each will be collected for PK assessments during stage I (n = 6) and II (n = 66) of the study. Samples will be shipped with data logger, and stored in a freezer at − 80 °C ± 10 °C, until completion of analysis. The Advanced Centre for Treatment, Research and Education in Cancer (ACTREC) clinical pharmacology lab will develop and validate a bioanalytical liquid chromatography–mass spectrometry (LCMS)/MS method to quantify oxfendazole and its metabolite. Genetic analyses will not be performed on these plasma samples.
Data Management and Statistical MethodsData ManagementAll trial-related data are being recorded in source documents by the site research team and subsequently entered in an electronic case report form (eCRF). Each participant is assigned a unique participant identifier (UPI) to ensure confidentiality and prevent identification of individuals from the study data. Similarly, all biological samples collected during the study will be labelled with the corresponding UPI.
Participant-related data is being stored in a secure, password-protected electronic database accessible only to authorized study personnel at the respective clinical sites. Access to the database is role-based and restricted to authorized users only.
The eCRF system is maintaining an audit trail documenting all data entries, modifications and corrections, including the date, time and identity of the user making the changes. Sponsor-designated monitors will perform source data verification (SDV) to ensure the accuracy, completeness and consistency of the data recorded in the eCRF, as per the predefined monitoring plan. Any discrepancies identified during monitoring will be addressed through queries raised to the site investigators and resolved in a timely manner.
A medical monitor periodically reviews the clinical data to ensure medical accuracy and completeness. Data cleaning will be performed continuously throughout the conduct of the study and will be finalized after the last participant’s last visit. Once the clinical data management team confirms data completeness and quality, the database will be formally locked, after which the final dataset will be provided to the biostatistician for statistical analysis according to the pre-specified statistical analysis plan.
All data management procedures are being conducted in compliance with applicable regulatory requirements and Good Clinical Practice (GCP) guidelines to ensure the integrity, confidentiality and reliability of the trial data.
Sample Size EstimationAs this is a phase IIa study, there is no previous data available for use of oxfendazole among patients with LF.
All patients in endemic areas are being provided mass drug administration (MDA). There is evidence that diethylcarbamazine (DEC) may have some activity against adult filarial worms [7,8,9]. For the study, it has been assumed that there will be clearance of worms in 30% of patients (due to natural death as well as effect of DEC or DEC + albendazole that is being given annually/biannually) at 6 months.
On the basis of the preclinical efficacy outcomes, it has been assumed that there will be worm clearance in 90% of the patients in the two intervention arms. Considering the above assumptions, power of 90% and alpha of 0.025, the sample size in each of the three groups is 18 for stage II. Assuming 20% dropout/ loss to follow-up, the sample size is kept as 22 in each group. Sixty-six participants would be required in stage II of the current proof-of-concept trial. Additionally, six participants will be required in the sentinel cohort, which will be included only in the safety analysis and not in the primary efficacy analysis. Thus the total sample size of study will be 72 participants.
Given the absence of prior clinical efficacy data of oxfendazole in patients with LF, the expected worm clearance rate in the intervention groups was estimated on the basis of available preclinical efficacy findings and the objectives of this phase IIa proof-of-concept study. In validated animal models of filariasis, oxfendazole demonstrated substantial activity against adult filarial worms, with near-complete or complete clearance observed in experimental settings [4]. Although efficacy observed in preclinical models may not directly translate to humans, the assumed 90% worm clearance rate was selected as a study planning parameter to evaluate whether oxfendazole could achieve a clinically meaningful macrofilaricidal effect. Existing public health interventions, including MDA regimens involving diethylcarbamazine, albendazole and/or ivermectin, are assumed to result in approximately 30% adult worm clearance over 6 months through a combination of residual macrofilaricidal activity and natural worm attrition. Therefore, a higher clearance threshold was considered appropriate to demonstrate a clear proof-of-concept signal for a novel macrofilaria-targeted therapy. The assumed treatment effect was not intended to represent an established clinical efficacy estimate but rather a predefined target to assess whether oxfendazole could provide a substantial therapeutic advantage over the expected background clearance rate and support further clinical development.
Primary and Secondary Endpoint AnalysisAll statistical analyses will be conducted in accordance with International Council for Harmonisation (ICH) E9 guidelines and the statistical analysis plan (SAP). The data will be analysed using STATA version 17, licensed to ICMR.
Primary Endpoint AnalysisThe primary endpoint is the proportion of participants with adult filarial worms at 6 months post-treatment. The null hypothesis assumes no difference among the three groups (oxfendazole 400 mg for 5 days, oxfendazole 800 mg for 5 days, and placebo). The primary efficacy analysis will compare the treatment arms using a two-sided chi-square test or its appropriate variant. To control the overall type I error rate (α = 0.05) across the two dose levels, hierarchical testing using the Hochberg method will be applied. Statistical significance for each dose level will be claimed if the p value meets the pre-specified threshold as per hierarchical testing.
Secondary Endpoint AnalysisSecondary endpoints, including mf load response and CFA positivity, will be analysed using logistic regression, adjusting for baseline mf score and time. Other secondary outcomes such as worm motility at 1 and 3 months, change in mf load, and CFA positivity will be summarized descriptively and analysed per pre-specified methods. Safety endpoints, including AEs, vital signs, ECG, physical examinations and laboratory parameters, will be summarized descriptively by treatment group and visit.
No formal interim efficacy analysis is planned. However, the data safety monitoring board (DSMB) will review safety data after each stage, typically 7 days post-first dose in stage I. The DSMB will provide recommendations for progression to the next stage based solely on safety considerations and will not assess efficacy data. Decisions to halt or modify the trial will be made according to DSMB recommendations in consultation with the sponsor.
Methods for Additional Analyses (e.g. Subgroup Analyses)Exploratory analyses will include PK evaluations. Non-compartmental PK analyses (Cmax, Tmax, Cmin, AUC0–t, t1/2, degree of fluctuation) will be performed using Pumas software.
Methods in Analysis to Handle Protocol Non-adherence and Any Statistical Methods to Handle Missing DataProtocol non-adherence is addressed through the definition of analysis populations. The primary analysis will use the modified intent-to-treat (mITT) population, which excludes participants with major protocol violations. A supporting per protocol set (PPS) analysis will also be conducted to evaluate the robustness of the results. If the size of the full analysis set (FAS) and PPS differs by more than 15%, both analyses will be presented.
For handling missing data in the primary analysis, the mITT population will use all available cases without imputation. A secondary sensitivity analysis on the ITT population will use the last observation carried forward (LOCF) method, carrying forward the last available efficacy assessment (e.g. from 1 or 3 months) to the 6-month time point. An additional analysis will replace missing values with the baseline value.
Comments (0)