
Remember me
This study was approved by the institutional review board of the author’s affiliated institution (approval number: NCCH-2023-407). The requirement for informed consent was waived because of the retrospective nature of the study.
Overview of this studyThis study employed a combination of two techniques to improve the detectability of small PDAC. The first approach involved automatic PDAC detection utilizing a three-dimensional convolutional neural network (3D-CNN) based on residual squeeze and excitation U-Net (residual SE U-Net) to identify potential tumor regions. A heat map was generated as a voxelwise likelihood map to indicate the probable PDAC region. In this study, the maximum value of the heatmap was utilized to evaluate the detectability of small PDAC considering the characteristics of the output of CNN model. The detailed CNN architecture and hyperparameters are described in Figure S1 and Table S1 in the supplementary file. The second technique involved evaluating the ratio of the cross-sectional area of the MPD to that of the pancreatic parenchyma (D/P ratio). The D/P ratio is a novel indirect indicator of PDAC that leverages the automated MPD segmentation technology developed in this study [12]. Typically, PDAC is associated with MPD in dilatation and pancreatic parenchyma atrophy. In this study, the D/P ratio was found to be higher in patients with PDAC (Fig. 1). The D/P ratio was calculated in three steps. The first step involved the segmentation of pancreatic parenchyma and MPD. The second step focused on estimating the centerline of the pancreas based on the segmented pancreatic and MPD regions. Finally, the third step entailed calculating the D/P ratio. The D/P ratio was calculated for all cross sections perpendicular to the identified centerline. In this study, the 90th percentile value of the D/P ratios across all cross sections was utilized to evaluate the detectability of small PDAC. The detailed algorithm for calculating the D/P ratio has been described elsewhere [13]. A logical disjunction was used to determine whether PDAC or not, a patient is considered positive if they have a maximum heat map value above the threshold or the D/P ratio above the 90th percentile threshold.
Fig. 1
Schematic image of D/P ratio. The D/P ratio is the ratio of the cross-sectional area of the main pancreatic duct (MPD) to the pancreatic parenchyma. The MPD is dilated due to obstruction of the tumor (red arrowhead) and atrophy of the parenchyma due to inflammation. Consequently, the D/P ratio is elevated in pancreatic ductal adenocarcinoma
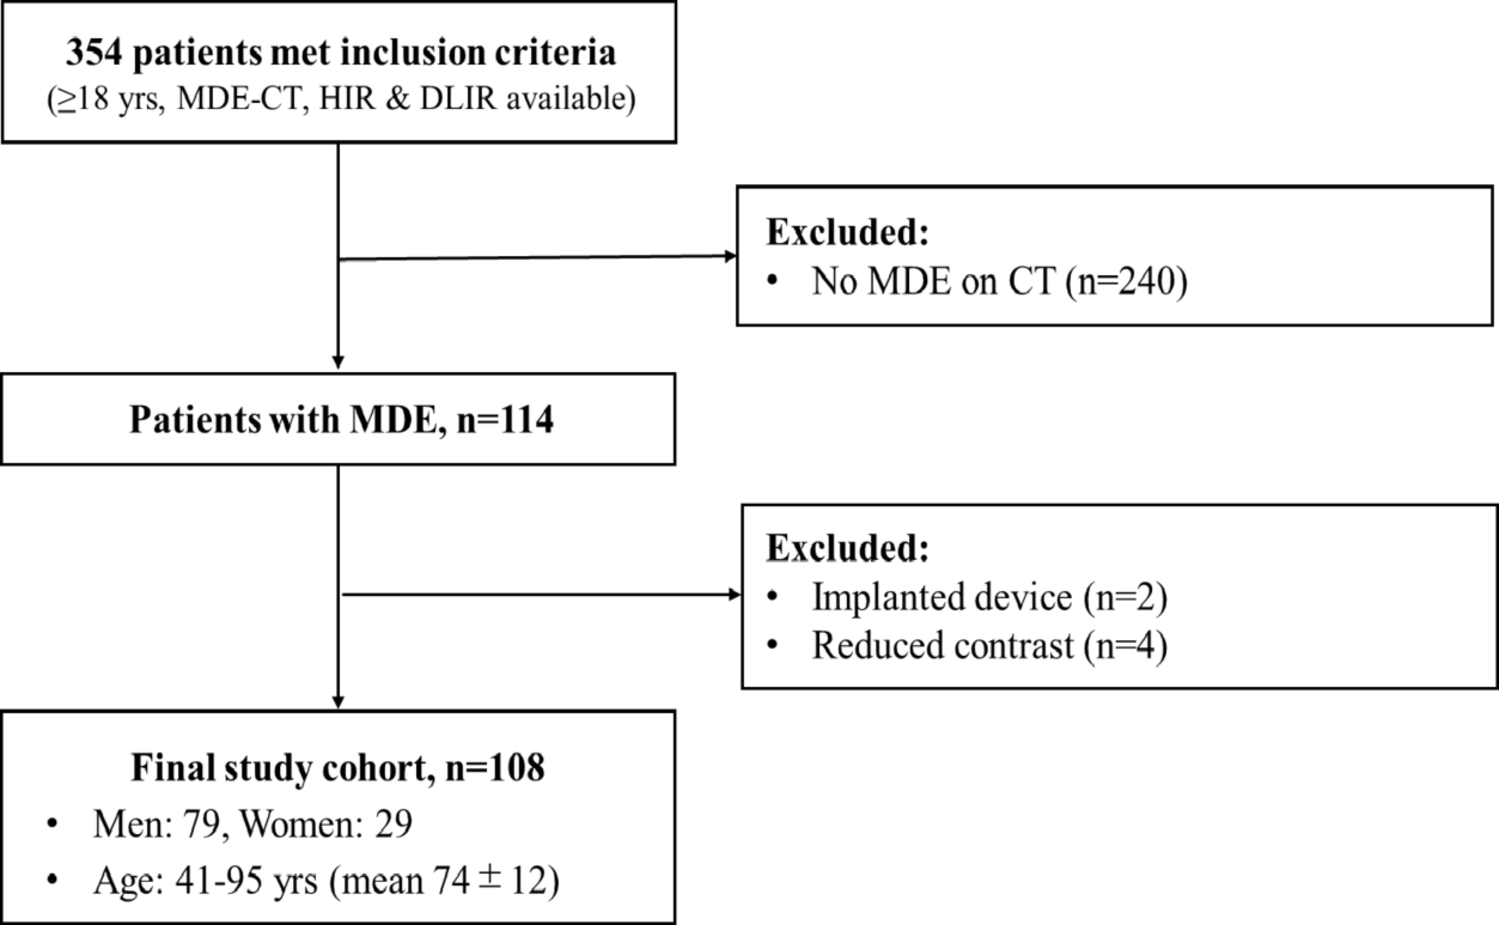
Patient data setCharacteristics of the data set that was used to develop the software are summarized in Fig. 2. Contrast-enhanced pancreatic protocol HR-CT scans from 181 consecutive patients diagnosed with T1 stage PDAC by endoscopic ultrasonography (EUS) between January 2018 and December 2023 at our institution were identified as an external data set. Of these, 100 patients were included in this study. The inclusion criteria were as follows: (a) a maximum PDAC diameter of ≤ 2 cm on axial image of CT and (b) age ≥ 18 years. The exclusion criteria were as follows: (a) a clinical history of pancreatic surgery or chemotherapy for PDAC and (b) inappropriate CT images phase (lack of pancreatic phase) or thickness. A total of 104 consecutive patients without pancreatic abnormalities were selected as controls. Additionally, 24 patients with PDAC and 26 patients without pancreatic abnormalities, who were not included in this study, were used to determine the thresholds for both tumor mass detection and the D/P ratio. The same imaging protocols were applied to these 50 patients for threshold setting as the patients for evaluation. All cases of PDAC were pathologically proven, and all cases without PDAC were determined by the consensus between two radiologists (M.O. and M.S., with 11 and 34 years of experience, respectively). Prior to the external test, data from 1538 patients were extracted for the training and validation sets from the following public data sets: The Cancer Imaging Archive (TCIA) and Medical Segmentation Decathlon (MSD) [14, 15].
Fig. 2
Overview of the study design and patient data set. TCIA the cancer imaging archive, MSD medical segmentation decathlon, PDAC pancreatic ductal adenocarcinoma
CT image acquisition and image reconstructionIn this study, the term “HR-CT” refers to dynamic contrast-enhanced CT with thin-slice (≤ 1 mm) reconstruction performed on various modern multidetector CT systems. While ultra-high-resolution CT using the Aquilion Precision was performed in a subset of cases, we adopted “HR-CT” as a collective term for all scans meeting the high spatial resolution criteria, to maintain consistency and avoid overgeneralization.
Seventy-eight CT images (78%, 78/100) were acquired using the ultra-high or high-resolution mode of a high-spatial-resolution CT (HSR-CT) scanner (Aquilion Precision; Canon Medical Systems, Otawara, Japan). The parameters employed were as follows: 1792 channels, 0.25 mm × 160 rows detector; slice thickness 1 mm; pitch factor of 0.569 or 0.813; gantry rotation period of 0.5 s; matrix size of 1024 × 1024 pixels; X-ray voltage of 120 kV; tube current optimized with automatic exposure control (Volume EC, Canon Medical Systems) using a noise level (standard deviation [SD]) of 12-HU with a thickness of 5.0 mm and a maximum value of 310 mA; and an arbitrary field of view. Some CT images were acquired using a different CT scanner (Aquilion ONE (5%, 5/100); Aquilion PRIME (17%, 17/100); Canon Medical Systems). The parameters employed were as follows: 896 channels; 0.5 mm × 80 rows detector; slice thickness of 1 mm; pitch factor of 0.813; gantry rotation period of 0.5 s; matrix size of 512 × 512 pixels; X-ray voltage 120 kVp; tube current optimized with automatic exposure control (Volume EC, Canon Medical Systems) using a noise level (Standard Deviation) of 12-HU with a thickness of 5.0 mm and a maximum value of 310 mA; and an arbitrary field of view.
The contrast-enhanced CT images were obtained using the following protocol. The first scan was initiated with the bolus-tracking method when the region of interest in the aorta achieved 150-HU. Subsequent scans were performed 20 and 45 s after the first scan, corresponding to the pancreatic and portal venous phases, respectively. The final scan was performed 180 s after the administration of the contrast agent. The contrast material, consisting of 600 mg of iodine per kilogram of total body weight, was injected over 30 s using a 20- or 22-gauge needle and a power injector (Dual shot; Nemoto Kyorindo, Tokyo, Japan). CT images were reconstructed using either hybrid iterative reconstruction (Adaptive Iterative Dose Reduction Three-Dimensional (3D) [AIDR3D, standard setting]; Canon Medical Systems) or deep learning reconstruction (Advanced Intelligent Clear-IQ Engine [AiCE, body sharp, mild]; Canon Medical Systems).
Evaluation and statistical analysisPancreatic phase of CT images was used for CNN input and the D/P ratio calculation. For tumor mass detection, each case was judged as pancreatic cancers if the maximum value of the heat map exceeded the threshold, and as normal otherwise. For the D/P ratio, each case was judged as pancreatic cancers if the 90th percentile value exceeded the threshold, and as normal otherwise. The threshold values were set so that the sensitivity for tumor mass detection was 80% and the specificity for the D/P ratio was 100% in threshold-setting cases. This is because the target of the heat map was to detect pancreatic cancers with high sensitivity, and the target of the D/P ratio was to detect pancreatic cancers that would keep the specificity of the heatmap alone when judged in combination with the heat map. The sensitivity, specificity, positive predictive value (PPV), and negative predictive value (NPV) with 95% confidence interval (CI) were calculated to evaluate the performance of each model: tumor mass detection, D/P ratio, and the combination of tumor mass detection and D/P ratio. The exact McNemar test was used to compare the sensitivity of the software with that of the radiologists as reported in the original radiology report for the same CT studies [6]. All radiology reports were retrieved from electronic health records and were interpreted by board-certified radiologists at a tertiary referral center with extensive experience in managing PDAC cases. Receiver operating characteristic (ROC) curve analyses were also performed. In addition, sensitivity, specificity, PPV, and NPV with 95% CI were calculated for each CT scanner, reconstruction technique, and tumor location. Each tumor location was classified into four patterns: head (uncinate process), head (the other), body, and tail using the CT images. Fisher’s exact test was used to compare the sensitivity, specificity, PPV, and NPV between classified groups. A p value of less than 0.05 was considered statistically significant for comparisons between tumor locations, and a p value of less than 0.05/4 = 0.0125 using Bonferroni correction for comparisons between CT scanners and between reconstruction methods. Moreover, decision curve analysis (DCA) was performed to assess the clinical utility of using our method in predicting the presence or absence of pancreatic cancer [16, 17]. Additionally, cases missed by the software or radiologists were thoroughly evaluated. To assess the accuracy of tumor localization in detecting PDAC, the software’s results were compared with findings from EUS, which has been reported to be superior to multidetector CT for PDAC detection in a previous prospective observational study [18]. The location of the pancreatic cancer detected in the software was defined as the location, where the heat map responds to pancreatic cancer-like structures observable on the image, and otherwise as the location, where the D/P ratio value increases sharply from the pancreatic head side to the pancreatic tail side. The location of the pancreatic cancer detected in the software was compared to the location of the pancreatic cancer detected with EUS. Accuracy analysis of the present software was performed by one cholangio-pancreatic endoscopist (S.H. with 27 years of experience). All statistical analyses were performed using the R software (R Foundation, Vienna, Austria). Statistical significance was determined using a p value < 0.05.
Comments (0)