
Remember me
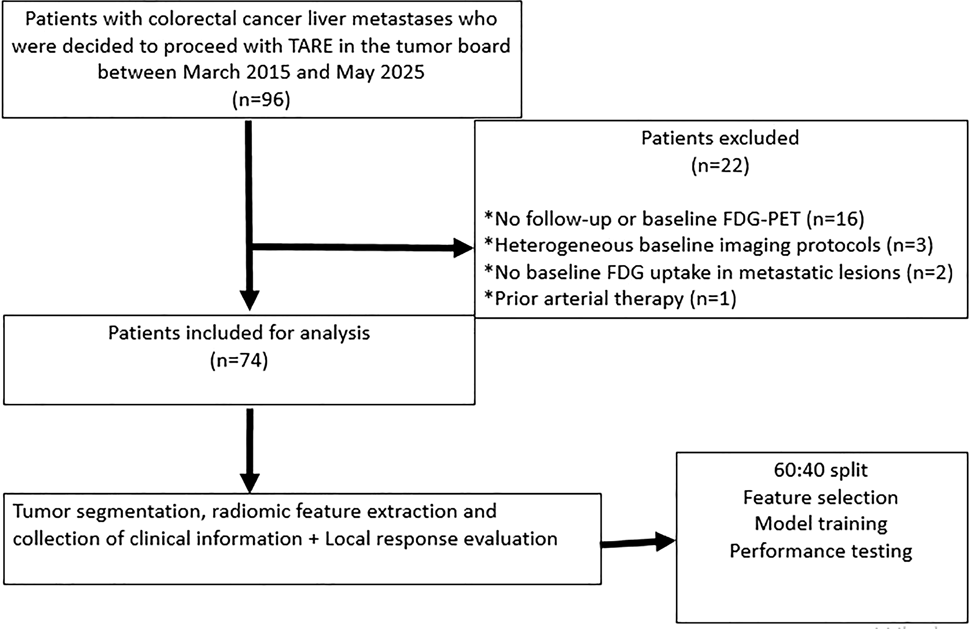
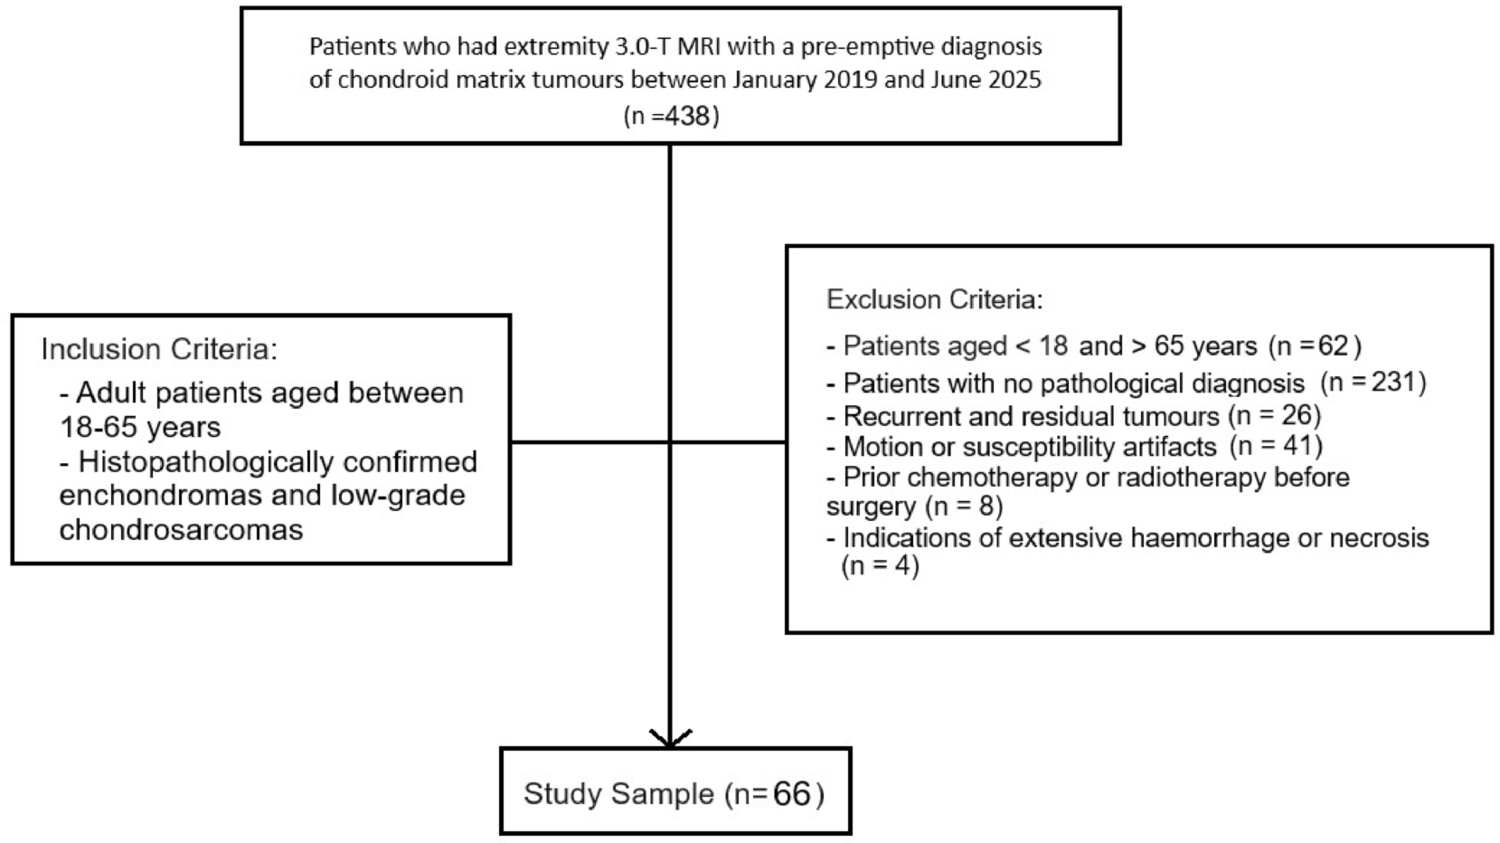
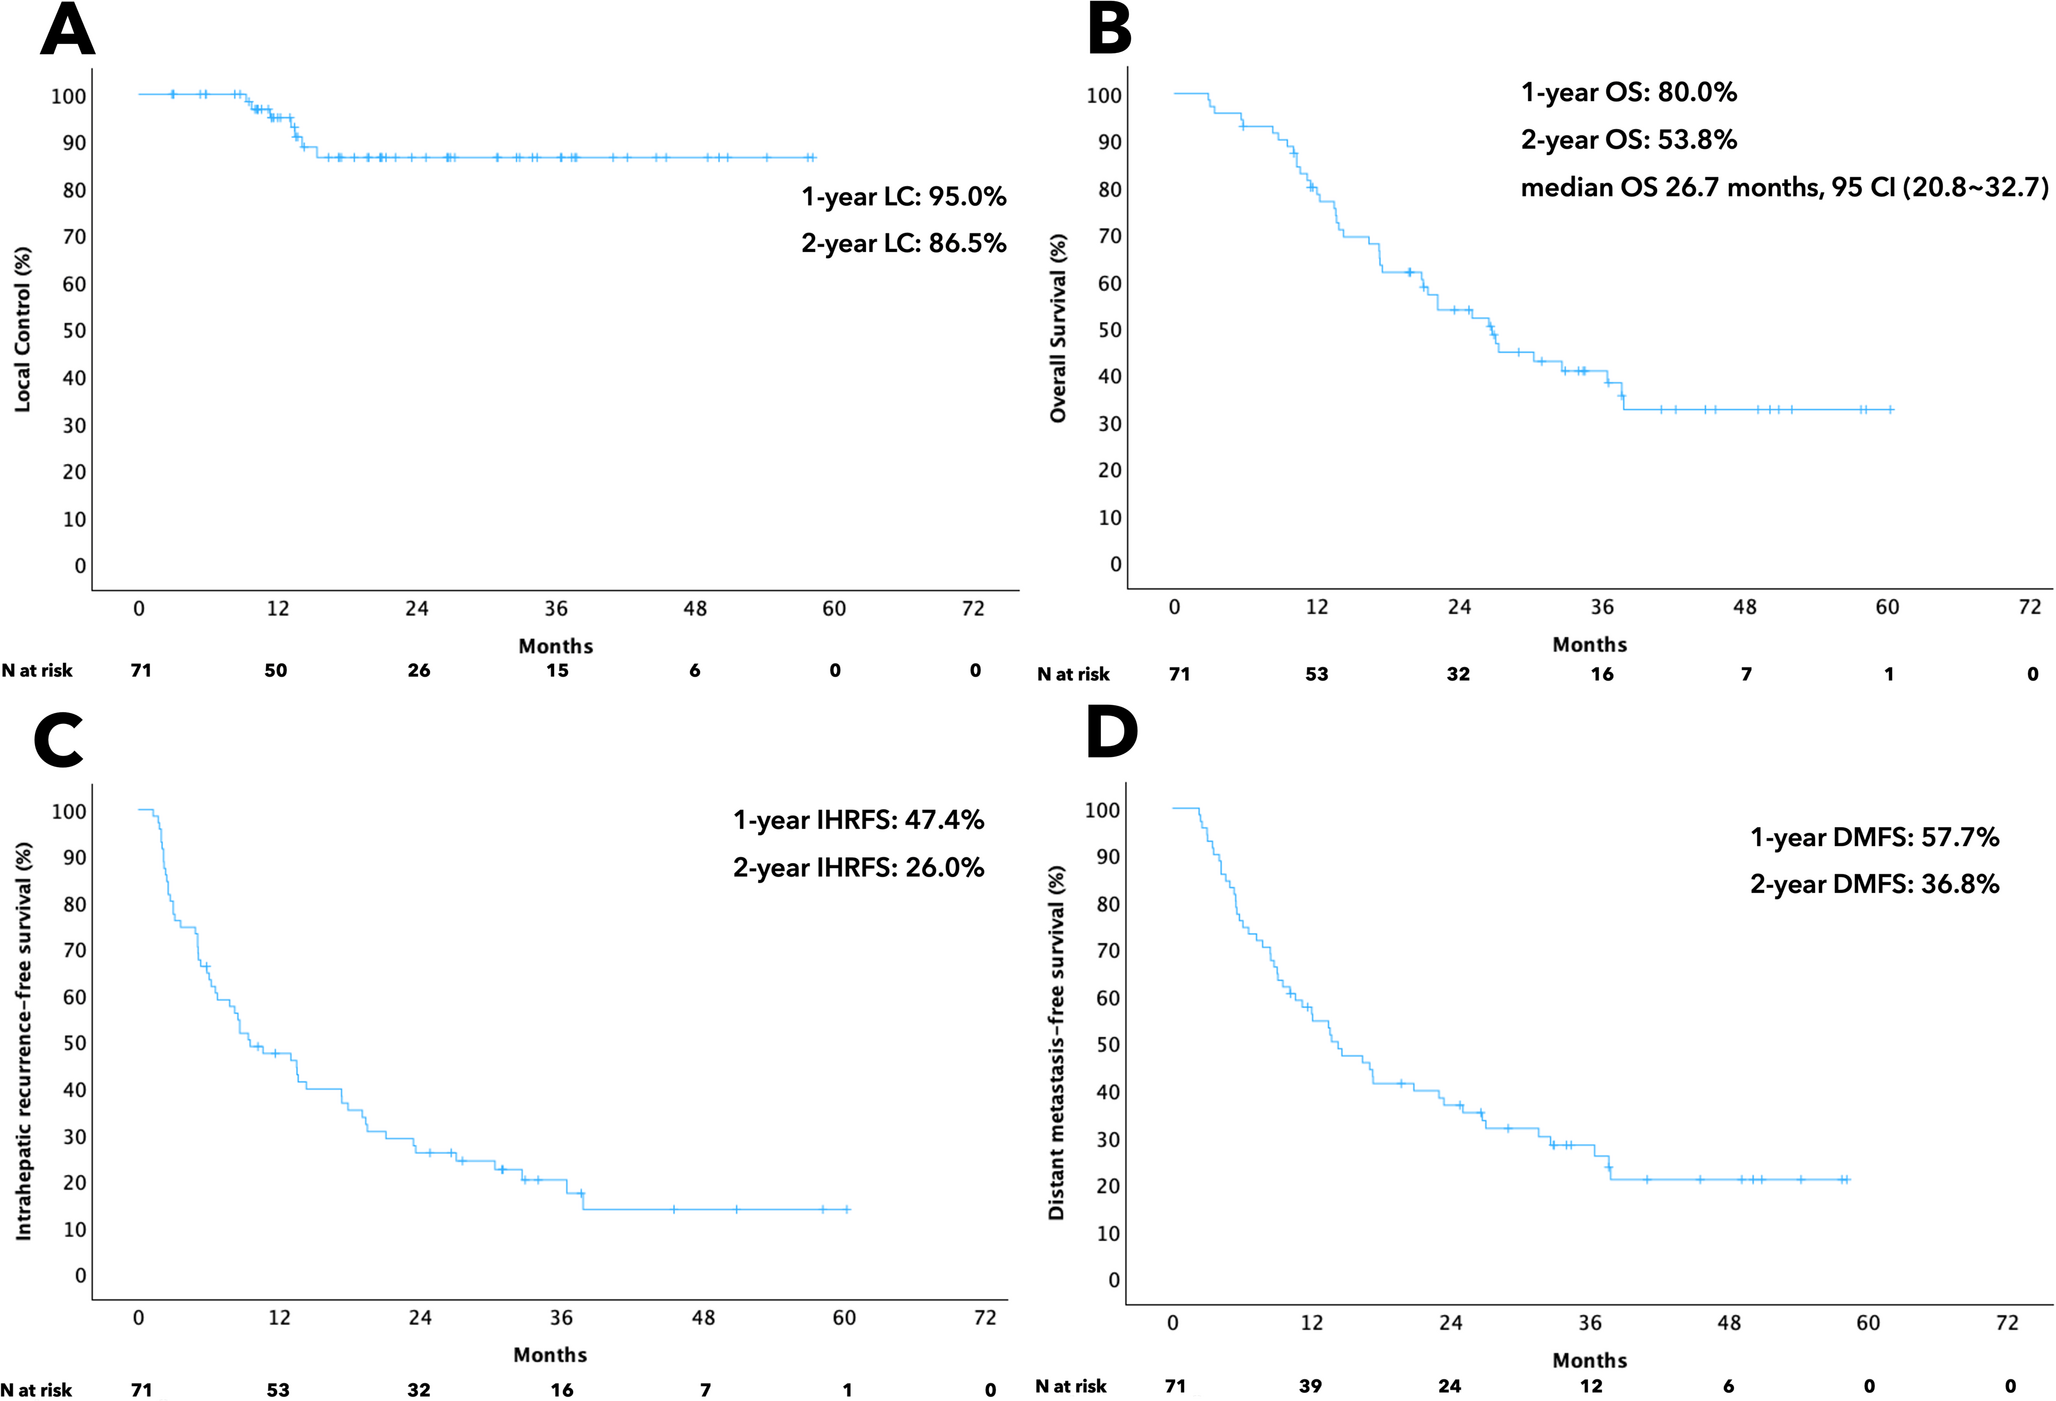
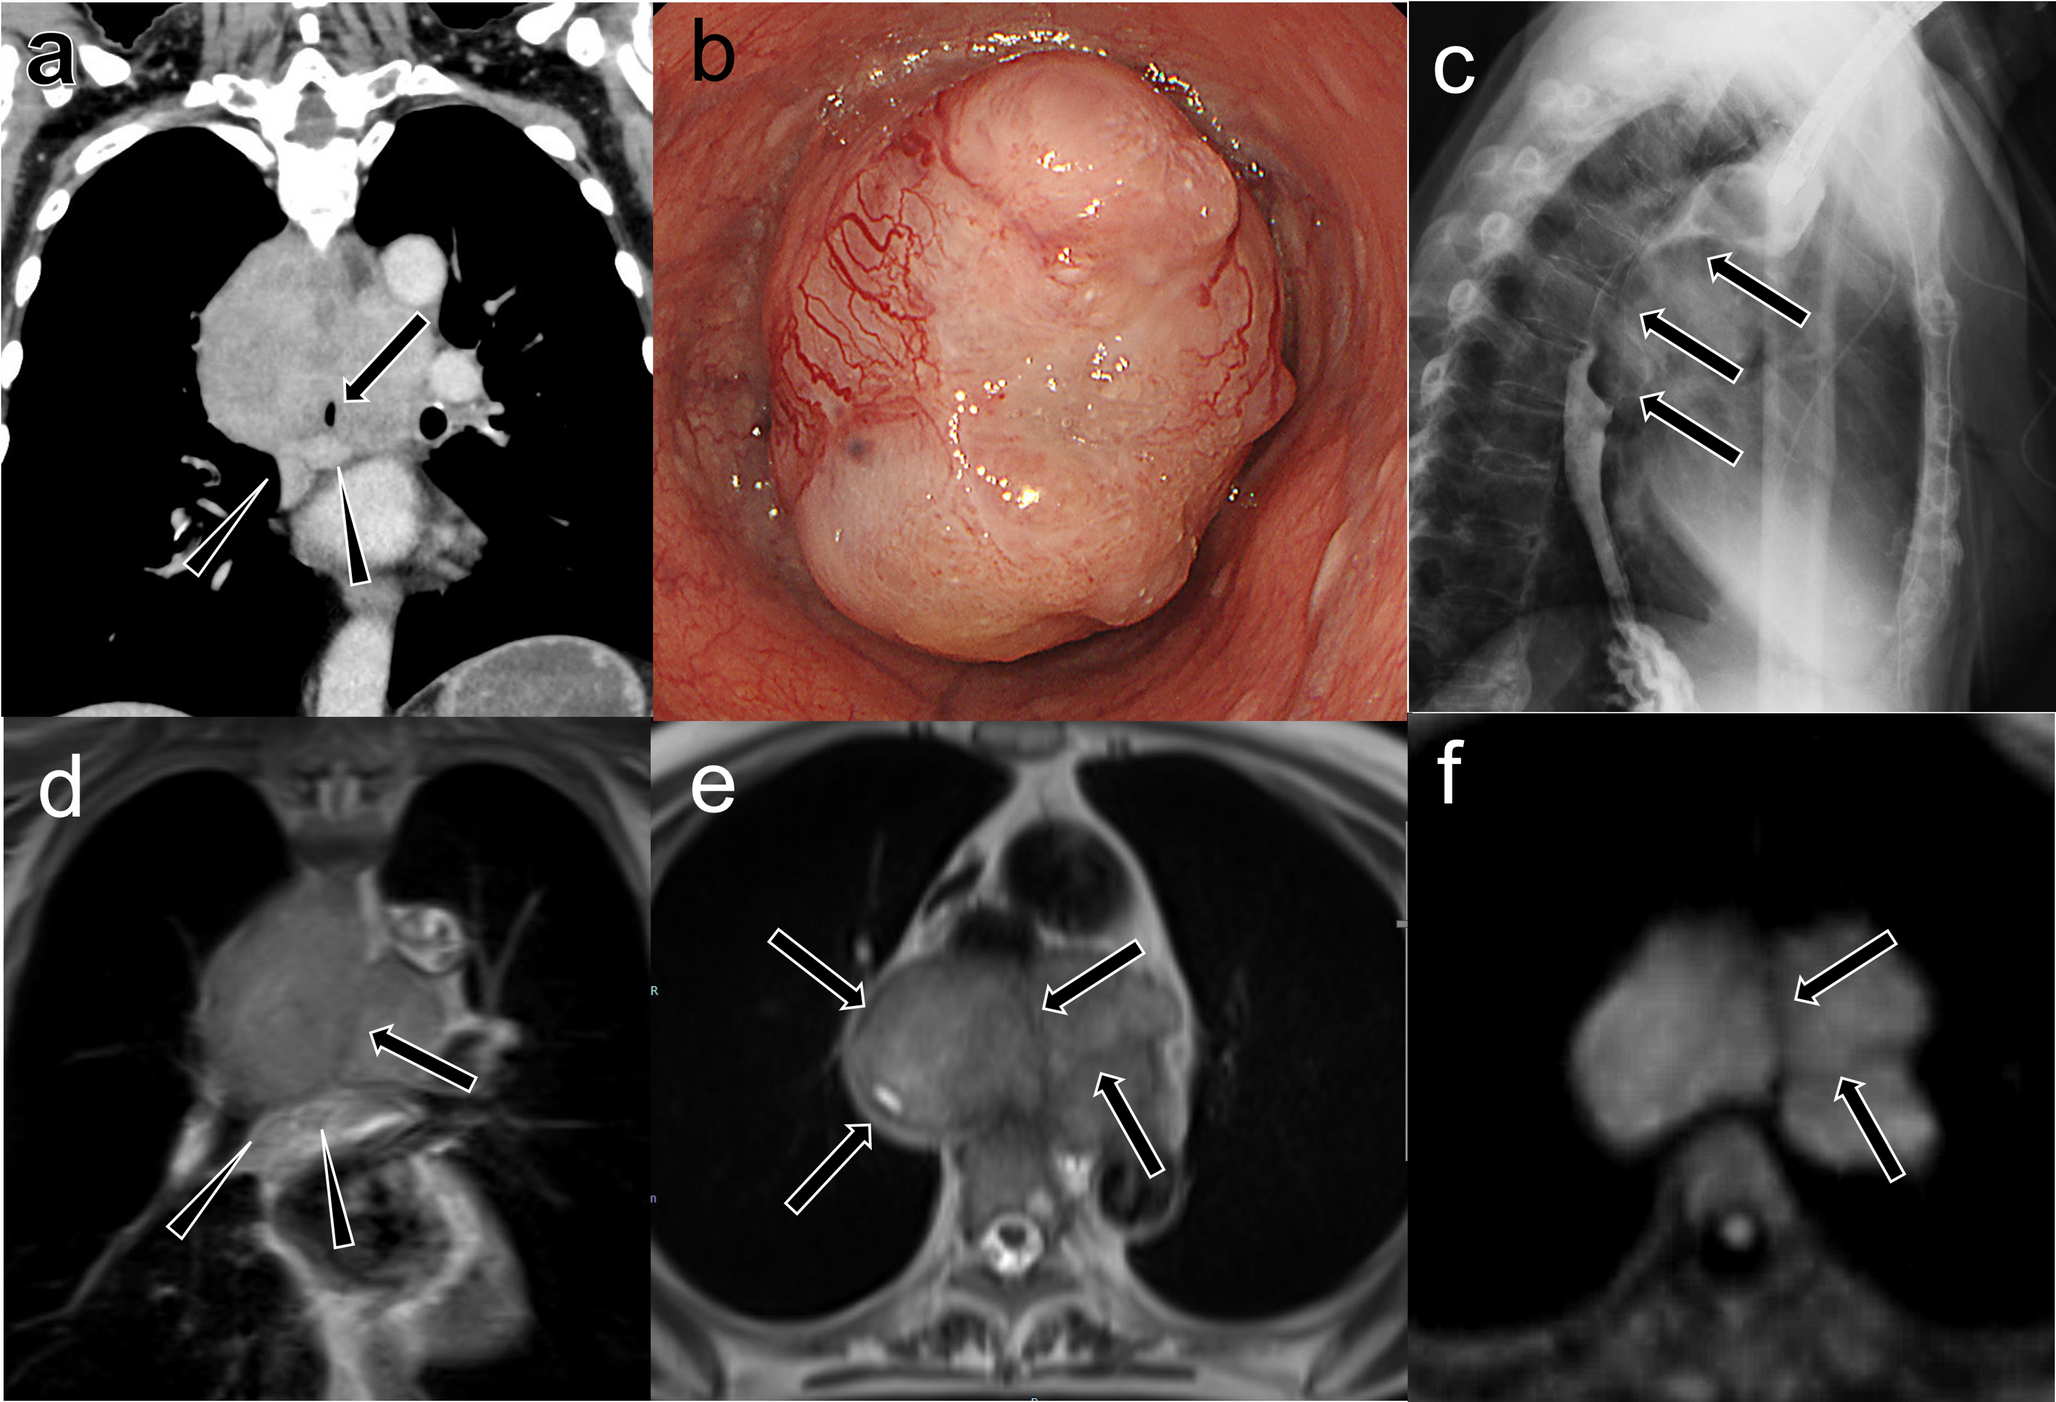
This study combined a retrospective observational study component and a single-case experimental study component. The study protocol was approved by the appropriate institutional ethics committee (file numbers: REC2024-071 and REC2024-072). For the retrospective study component, the requirement for written informed consent was waived due to data anonymization and the retrospective study design. Opt-out methods for participants were provided by publishing a summary of this study on the institutional websites. Written informed consent was obtained from the volunteer for the single-case experimental study component. This study was conducted in accordance with the ethical standards of the institutional and/or national research committee and the 1964 Helsinki Declaration and its later amendments or comparable ethical standards.
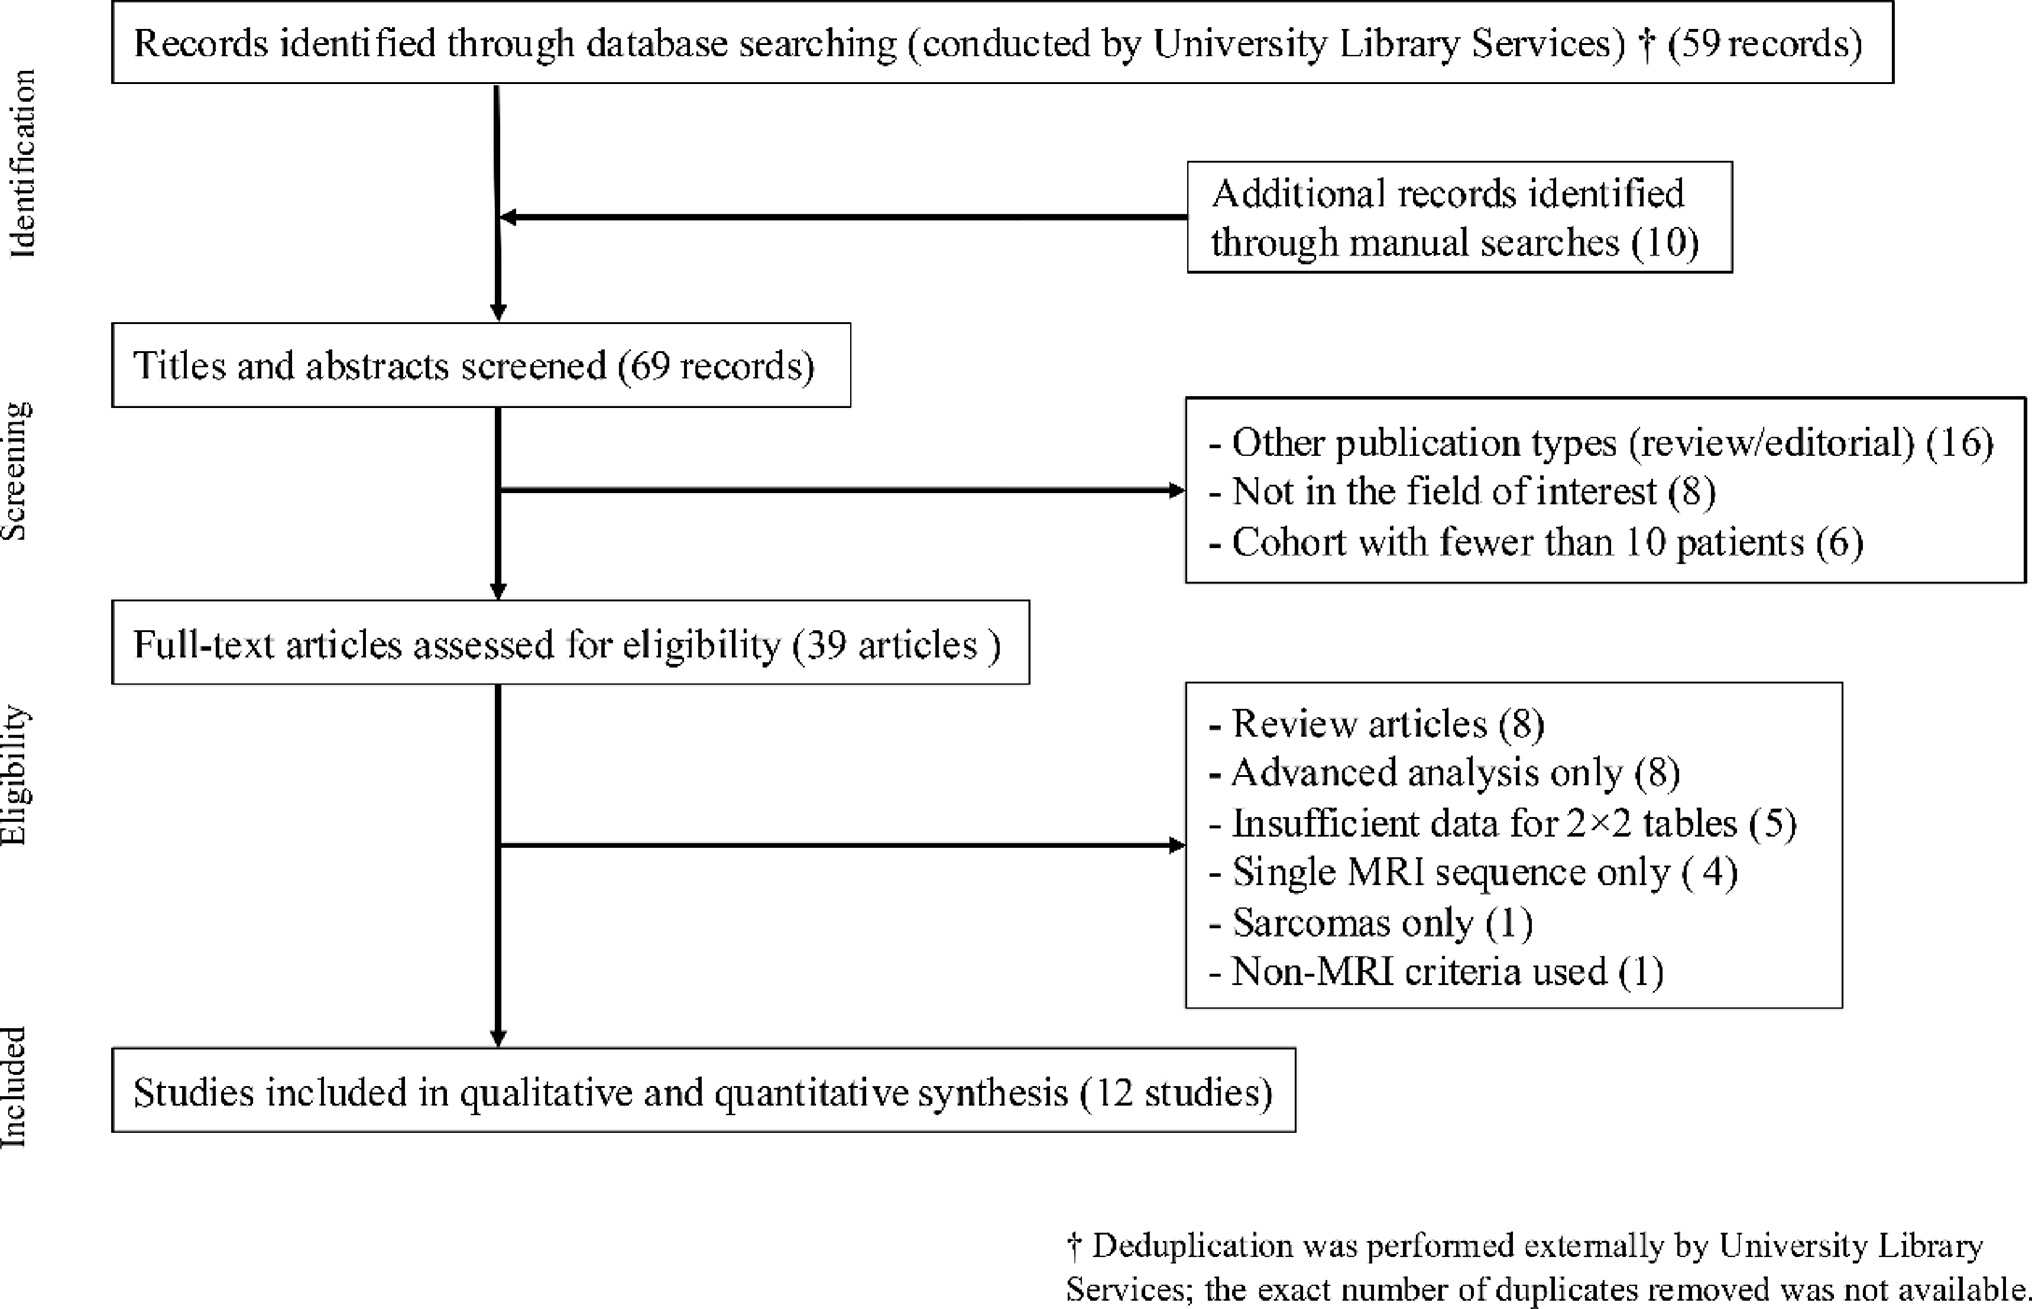
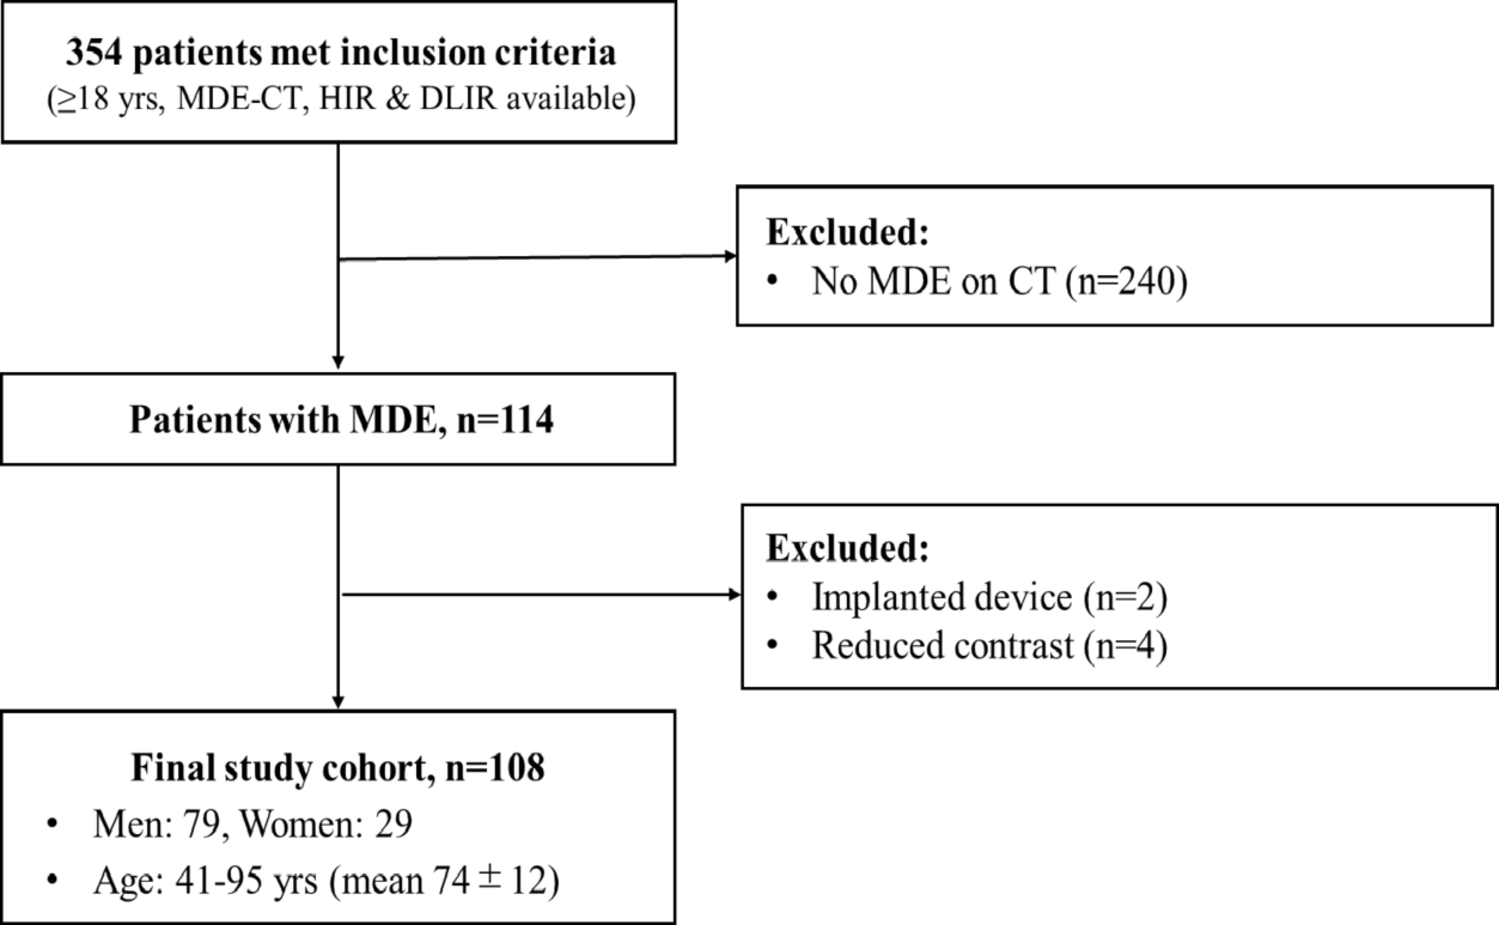
Retrospective study componentParticipantsThe patient selection flowchart for this study is shown in Fig. 2. Adult patients who had undergone brain MRI examinations, including whole-brain axial spin-echo T2WI using a 3.0-T MR scanner (MAGNETOM VIDA; Siemens Healthineers, Erlangen, Germany) at our institution between June 2024 and July 2024 were selected from the database. MRI scans with artifacts, including metal or motion, were excluded. Additionally, participants with lesions in any of the 22 evaluated brain areas were excluded.
Fig. 2
Flowchart of patient selection
MRIWhole-brain axial spin-echo T2WI was acquired using clinical imaging sequences. The axial plane extended from the anterior commissure to the orbitomeatal line (OM) line. Representative T2WI parameters are listed in Table 1.
Table 1 Representative parameters of axial spin echo T2WI in clinical use at our institutionImaging analysisFor the imaging analysis, T2-PR was defined as a low signal intensity on the brain surface, similar to or lower than that of the substantia nigra (SN), which has physiological iron deposition [9] and mainly shows a low signal intensity on T2WI [10]. Iron deposition in the SN is completed earlier than in the globus pallidus, putamen, and caudate nucleus and is less affected by aging [11]. Therefore, the SN was used as a reference region to identify a low T2WI signal intensity.
Visual estimation was performed independently by two radiologists (with 23 and 11 years of experience) who reviewed brain T2WI MRI scans using workstation software (EV Insite 3.17; PSP Corporation, Tokyo, Japan) to determine the presence of T2-PR. To facilitate a comparison with the midbrain SN, reversed T2WI was also evaluated. The window level of the reversed T2WI was set near each participant’s SN signal value, and a narrow window width (approximately 150) was set.
The presence of T2-PR was evaluated at 22 locations within the following areas: lower midbrain, upper pons, lower pons, medulla oblongata, cerebellum, and temporal lobe. The locations in the midbrain, pons, and medulla oblongata were defined based on the cisterns and ventricles that encountered the brainstem. The cistern regions were defined based on a report by Morris et al. [12]. For the cerebellum, both the left and right cerebellar hemisphere surfaces were evaluated, and for the temporal lobe, the surfaces of the left and right temporal poles were assessed. Additional details of the evaluation sites are presented in Table 2 and Fig. 3.
Table 2 List of twenty-two areas to assess T2 physioligical rim, T2-PR score, T2-PR thickness of each areasFig. 3
The 22 areas used to assess for T2 physiological rim (T2-PR). a midbrain, b upper pons (at the superior cerebellar peduncle level), c lower pons (at the middle cerebellar peduncle level), d medulla oblongata, e cerebellum (at the middle cerebellar peduncle level), and the temporal lobe. The definition of each site is presented in Table 2
T2-PR was evaluated for each of the 22 areas using the following scoring system: 0 points for the absence of T2-PR, 1 point for < 50% of the surface, 2 points for ≥ 50% of the surface but not the entire surface, and 3 points for the entire surface (Fig. 4). A scoring example is shown in Supplemental Digital Content 1. After assessing inter-tester agreement, the analysts’ scores for each area were averaged (averaged T2-PR score). Then, each participant’s T2-PR scores in the 22 areas were summed (summed T2-PR score).
Fig. 4
Representative examples of the 0–3 scoring system for T2 physiological rim (T2-PR). a 0 points for the absence of T2-PR, b 1 point if T2-PR is observed on < 50% of the surface, c 2 points if T2-PR is observed on ≥ 50% but not the entire surface, and d 3 points if thin T2-PR observed on the entire surface
To quantify the thickness of T2-PR, a radiologist with 11 years of experience measured its thickness on inverted T2WI using workstation software (EV Insite 3.17). For each of the 22 regions, the maximum thickness of the T2-PR was determined manually in a direction perpendicular to the brain surface tangent. An example of this measurement is shown in Supplemental Digital Content 1.
Validation cohortTo validate the T2-PR phenomenon, a separate T2-PR score estimation was performed using participants who underwent another brain MRI examination at our institution within one year before or after the index MRI scan. The MRI was performed on one of the six MRI scanner installed at our hospital. This supplementary examination included whole-brain axial spin-echo T2WI. If multiple eligible examinations were available, the MRI temporally closest to the index MRI was selected. Imaging analysis was performed using the same criteria and by the same two radiologists who analyzed the index MRI scan. Example MRI from index and validation MRIs is shown in Supplemental Digital Content 2. The representative parameters of the validation T2WI are presented in Supplemental Table 1 (Supplemental Digital Content 3). After assessing inter-tester agreement, the analysts’ scores for each area were averaged (averaged validation MRI T2-PR score).
Statistical analysisNonparametric statistical methods were employed because the Shapiro–Wilk test revealed a non-normal distribution of T2-PR scores. Inter-tester agreement and the agreement between the averaged T2-PR scores from index MRI and the averaged validation MRI T2-PR scores were assessed using weighted kappa statistics and intraclass correlation coefficient (ICC). The κ values were interpreted as follows: poor (κ = 0.0), small/slight (κ = 0.0–0.20), fair (κ = 0.21–0.40), moderate (κ = 0.41–0.60), substantial (κ = 0.61–0.80), and almost perfect (κ = 0.81–1.00) [13]. For ICC, a two-way random, single-score model (ICC(2,1)) was used.
The Friedman test was performed to evaluate differences in the T2-PR scores and T2-PR thickness of the 22 areas, and the Scheffé’s post-hoc test was performed for multiple comparisons. To confirm age-dependent differences in summed T2-PR scores, participants were categorized into two subgroups: adults (18 to under 65 years) and older adults (≥ 65 years). The summed T2-PR scores of the subgroups were compared using the Mann–Whitney U test.
All statistical analyses were performed using a commercial software program (Bell Curve for Excel 4.07; Social Survey Research Information, Tokyo, Japan). Statistical significance was set at P < 0.05.
Single-case experimental study componentParticipantThe participant was a 40-year-old, healthy male volunteer without a history of neurological diseases, including stroke, subarachnoid hemorrhage, cerebral hemorrhage, or head injury, and without neurological symptoms, including those suggestive of cerebrospinal fluid hypovolemia or SS, such as headaches [14, 15], ataxia [16], or hearing loss [5, 8]. MRI was performed to evaluate the effects of chemical shifts and magnetic susceptibility on T2-PR.
MRI scannerBrain MRI was performed using a 3.0-T MR scanner (MAGNETOM VIDA; Siemens Healthineers) and a 64-channel head coil.
Distribution of T2-PRTo investigate the distribution of T2-PR, brainstem-focused, high-resolution T2WI was performed using the following sequences: axial T2WI; repetition time (TR)/echo time (TE), 6230/99 ms; flip angle, 147°; matrix, 288 × 288; field of view (FOV), 160 mm; slice thickness, 2 mm, frequency encoding, right-left (RL) direction; and bandwidth, 395 Hz/pix. Deep Resolve (Siemens Healthineers), a deep-learning reconstruction method, was applied to denoise and improve resolution. The distribution of T2-PR was assessed in the same 22 areas used for the retrospective study component.
Chemical shift effectFirst, axial T2WI (TR/ TE, 4500/104 ms; flip angle, 160°; matrix, 368 × 294; FOV, 220 mm; slice thickness, 5 mm; frequency encoding, RL direction; bandwidth, 400 Hz/pix) was performed as a standard. To avoid the influence of filters, images were created without applying filters except for the sensitivity correction filter, which corrects for contrast irregularities.
To assess the effect of the chemical shift on T2-PR, the bandwidths and encoding directions were altered from those of the standard T2WI. The bandwidth was adjusted to 200 and 100 Hz/pix to determine whether the T2-PR varied in each image, while the other T2WI parameters remained unchanged. Second, the encoding direction was modified to left–right, anterior–posterior, and posterior-anterior, while the other T2WI parameters, including the bandwidth, were consistent with the standard T2WI.
Magnetic susceptibility effectTo determine whether T2-PR exhibits the magnetic susceptibility effect, the TE of T2WI and T2*WI were varied to determine whether any alterations in the size of the T2-PR occurred [17, 18].
In T2*WI, axial T2*WI (TR/TE, 1800/10 ms; flip angle, 20°; matrix, 224 × 224; FOV, 220 mm; slice thickness, 2 mm) was performed as a standard T2*WI. Subsequently, the TE was changed to 20, 30, 40, and 50 ms, while the other T2*WI parameters were unchanged.
In T2WI, axial T2WI (TR/TE, 4500/47 ms; flip angle, 160°; matrix, 368 × 294; FOV, 220 mm; slice thickness, 2 mm) was performed as a standard T2*WI. Subsequently, the TE was changed from 47 to 198 ms (47, 66, 85, 104, 122, 141, 160, 179, 198), while the other T2WI parameters remained unchanged.
Partial volume effect (PVE)To assess the PVE on T2-PR, the slice thickness was changed to 10, 5, and 2 mm, while the other parameters (TR/TE, 4500/103 ms; flip angle, 160°; matrix, 320 × 320; FOV, 160 mm; bandwidth, 400 Hz/pix) remained unchanged. To avoid the influence of filters, images were created without applying filters except for the sensitivity correction filter, which corrects for contrast irregularities.
Moreover, an 0.5-mm isotropic reconstruction three-dimensional (3D) T2WI sequence—namely, T2 sampling perfection with application-optimized contrast using different flip angle evolution (3D T2-SPACE)—was employed to acquire images with minimized partial volume effects (PVE).
Other MRI sequencesT1-weighted imaging (T1WI), T2-weighted fluid-attenuated inversion recovery (T2-FLAIR), diffusion-weighted imaging (DWI), and time-of-flight magnetic resonance angiography (TOF MRA) were also performed to rule out neurological diseases, such as brain infarctions, subdural hematomas, or brain tumors.
Magnetic susceptibility source separation (X-separation)To further investigation on magnetic susceptibility effect, χ-separation magnetic susceptibility source separation analysis [19] was performed using a 3.0-T MR scanner (MAGNETOM Skyra; Siemens Healthineers) and a 64-channel head coil. For the analysis, the 3D multiecho gladient echo MRI were acquired with the following parameters: TR = 44 ms, TEs = 3.6, 9.5, 15.4, 21.3, 27.3, 33.2, and 39.1 ms, FOV = 240 × 240 mm, voxel size = 0.94 × 0.94 × 1.00 mm3, flip angle = 15°, bandwidth = 240 Hz/ pixel, GRAPPA factor = 2, and time of acquisition = 5.05 min.
X-separation were performed using the χ-separation toolbox software (https://github.com/SNU-LIST/chi-separation) implemented in MATLAB 2025 (MathWorks Inc., Natick, MA, USA). The following techniques were applied for the analysis: phase unwrapping using Barbara’s method based on the rapid open-source minimum spanning tree algorithm [20]; background field removal using Bing’s method [21]; quantitative susceptibility mapping (QSM) using QSMnet [22]; and magnetic susceptibility source separation using χ-sepnet [23].
As a result of the χ-separation analysis, three types of susceptibility maps were generated: a positive (paramagnetic) susceptibility map, a negative (diamagnetic) susceptibility map, and a total susceptibility map, which is nearly equivalent to the conventional QSM image.
Comparison between MRI scannersTo confirm that T2-PR is not dependent on a specific MRI scanner, brain T2WI was performed using two additional 1.5-T MR scanners (Vantage Fortian; Canon Medical Systems, Otawara, Japan and Optima 450w; GE Healthcare, Milwaukee, WI, USA). Axial spin-echo T2-weighted brain images were acquired using clinical imaging sequences optimized for each MRI system, as routinely performed at our institution. The axial plane was aligned along the OM line. These T2WI parameters are listed in Supplementary Table 2 (in Supplemental Digital Content 3). To quantify the thickness of T2-PR, a radiologist with 11 years of experience measured its thickness using workstation software (EV Insite 3.17). For each of the 22 regions, the maximum thickness of the T2-PR was determined manually in a direction perpendicular to the brain surface tangent.
Comments (0)