
Remember me





According to PRISMA guidelines, our search produced 320 unique abstracts and full-text articles, of which 14 completely fulfilled the inclusion criteria (Figure 2). Articles were published between 2020 and 2025, were mostly from the United States, and examined one of five psychiatric indications (Figure 3). Of the 14 relevant articles identified (Table 2), 9 studies focused on major depressive disorder (MDD), 1 on generalized anxiety disorder (GAD), 1 on obsessive-compulsive disorder (OCD), 2 on substance use disorder (SUD), and 1 on schizophrenia (Figure 3A). We ultimately grouped three mixed-cohort studies with MDD as a primary indication given the researchers’ choice of clinical indices; one study enrolled patients with mixed affective disorders including MDD, GAD, and trauma-related disorders; one study included subjects with “mild-to-moderate depression” and excluded severely depressed or suicidal patients; and one study consisted of a 22-patient cohort of whom 20 were diagnosed with MDD and 2 with bipolar disorder, current episode depressive (Barksdale et al. 2025; Reznik et al. 2020; Riis et al. 2025)
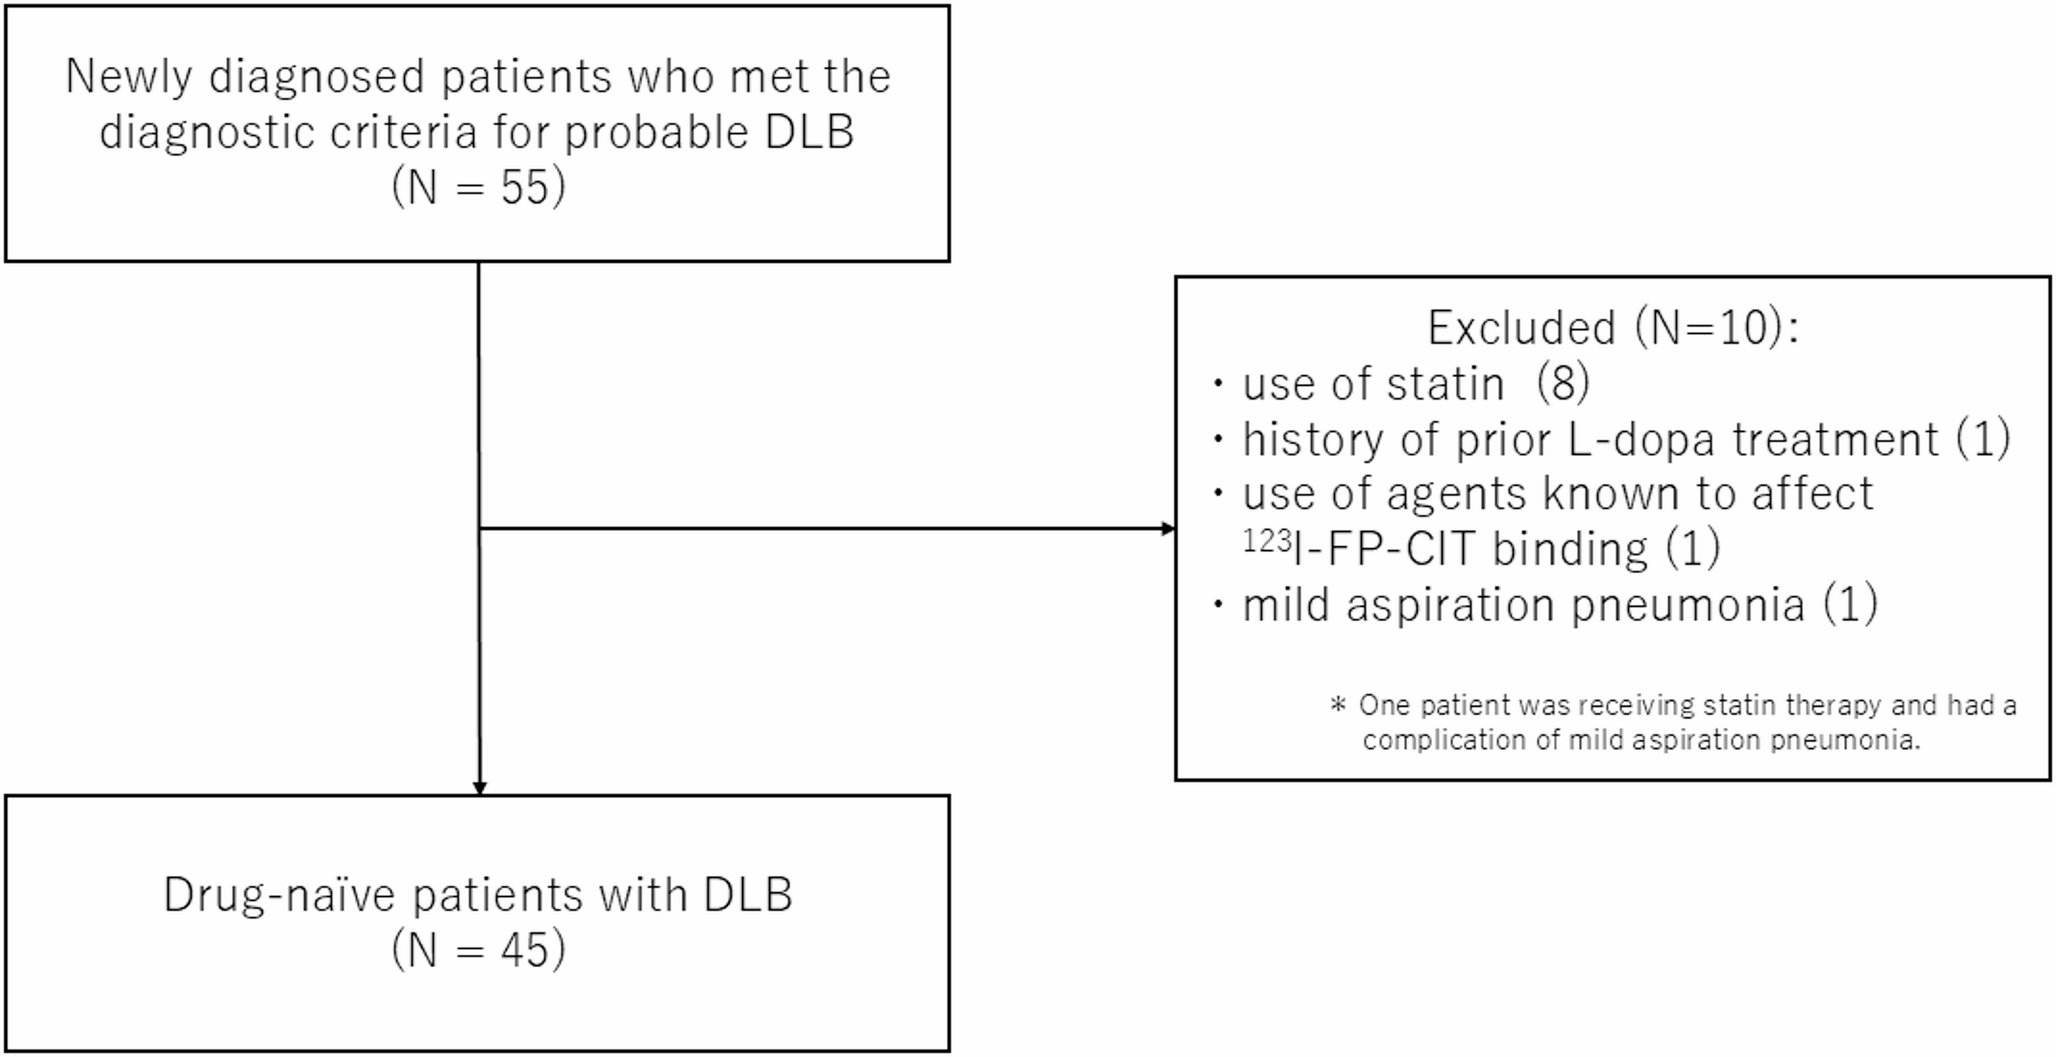
Fig. 2
PRISMA flowchart for identification and screening of psychiatric FUS studies. This figure outlines the study selection process for the scoping review. A total of 843 records were identified from PubMed, Embase, and Scopus. After removing 523 duplicate records, 320 studies were screened based on title and abstract. Of these, 296 were excluded, and 25 full-text reports were sought for eligibility assessment. Following exclusions based on study focus (evaluation of healthy networks, interim reports, and insufficient efficacy data), 14 studies were included in the final review (12 full texts and 2 abstracts)
In total, 242 subjects were identified across the included studies, the majority of which (65%) were patients with MDD (Figure 3B). Targets of sonication varied substantially and included the amygdala, subcallosal cingulate cortex (SCC), dorsolateral and/or anteromedial prefrontal cortex (PFC), fronto-temporal cortex, thalamus, and the basal ganglia (nucleus accumbens, caudate, ventral striatum) (Figure 1). Furthermore, there was significant heterogeneity in sonication devices and protocols, assessment/follow-up timelines, and study design; for example, studies varied from open-label pilots with custom ultrasound prototype devices, to sham-controlled RCTs with commercially available devices and standardized parameters. Many studies included mild adverse events (AEs), and one study reported two serious adverse events.
Fig. 3
Characterization of focused ultrasound neuromodulation studies. A shows the distribution of focused ultrasound neuromodulation studies by patients per indication. B Shows the number of patients and studies by indication. C shows the number of studies by year
Major depressive disorder (MDD)Nine studies investigating the effects of focused ultrasound for major depressive disorder (MDD) in 158 total patients were included in this review (Barksdale et al. 2025; Reznik et al. 2020; Cheung et al. 2023; Oh et al. 2024; Schachtner et al. 2025; Riis et al. 2025; Fan et al. 2024; Attali et al. 2025; Riis et al. 2023). Most studies reported reductions in depressive symptom severity with varying effect sizes, though outcomes were heterogeneous across study designs and outcome domains. Targets included the DLPFC, fronto-temporal cortex, SCC, amygdala, subcallosal cingulate white matter tracts, and anterior nucleus of the thalamus (ANT). Sonication parameters varied widely across the studies. Frequencies ranged from 250 kHz to 650 kHz and sonication duration ranged between 30 s and 64 min. Common outcome metrics included the Hamilton Depression Rating Scale (HDRS), Montgomery-Åsberg Depression Rating Scale (MADRS), Beck Depression Inventory-II (BDI-II), and others.
Three randomized controlled trials (RCT) were conducted for MDD two of which were sham-controlled and one waitlist controlled; a fourth study was a randomized controlled crossover pilot. Reznik et al. 2020 conducted the first placebo-controlled RCT of low-intensity ultrasound for major depression, enrolling 24 university students with mild-to-moderate symptoms (Reznik et al. 2020). Participants were randomized to active or sham groups and received five sessions of 30-second sonications of the right fronto-temporal cortex over seven days (500 kHz, ISPTA ≈ 71 mW cm⁻²; Neurotrek U+, Thync, Los Gatos, CA). Given the pilot nature and small sample size, the study was underpowered for conventional between-group effects. Across the treatment week, trait worry (a dispositional tendency to engage in uncontrollable worrying, typically indexed by the Penn State Worry Questionnaire) fell in the active group and rose in sham (PSWQ, t(20) = −1.74, p= 0.097), whereas BDI-II and anxiety impairment (OASIS) scores showed no differential change. At one month follow-up, no persistent group differences in BDI-II or OASIS were detected, and trait worry was not reassessed. No adverse events occurred (Reznik et al. 2020).
The largest study reported thus far Cheung et al. reported a single-blinded RCT in 2023 with 30 MDD patients, allocating 15 to transcranial pulse stimulation (TPS) and 15 to a waitlist control. TPS is a form of low-intensity focused ultrasound that delivers single, ultrashort acoustic pulses (Cheung et al. 2023). Using MRI-guided neuronavigation, six 30-minute sessions of 300 pulses per session (pulse repetition frequency 3–4 Hz) were administered to the left DLPFC over two weeks. Compared with control, the TPS group exhibited a significant immediate reduction in HDRS-17 scores with a mean difference of −6.60 compared to the control group (p = 0.02, Cohen’s d = −0.93), with effects further deepening at the 3-month follow-up (Cohen’s d = −1.35) (Cheung et al. 2023). Immediate improvements were also noted in the secondary outcomes of anhedonia (Cohen’s d = −0.79), cognition (Cohen’s d = 0.88), and working memory (Cohen’s d = 0.69), each of which similarly sustained or became even more prominent at the 3 month mark (Cohen’s d = −0.81, 1.20, 1.09, respectively) (Cheung et al. 2023).
The third MDD RCT was the 2024 study reported by Oh et al. This double-blind, sham-controlled trial randomized 26 adults with MDD to real or sham ultrasound treatment; 23 completed all procedures (treatment = 11, sham = 12) (Oh et al. 2024). Each participant received six 20-min sessions of low-intensity ultrasound (250 kHz, 3 W cm−2 ISPPA, 1 ms bursts at 50% duty cycle, 300 ms trains every 6 s) to the left DLPFC over two weeks. Mean MADRS ratings fell from 28.5 ± 8.4 to 16.8 ± 6.8 at end-of-treatment, further falling to 14.8 ± 7.2 two weeks later (p= 0.003), whereas the sham group showed only modest change (baseline: 29.2 ± 8.3, treatment: 25.7 ± 9.0, two weeks: 24.8 ± 9.3). Response (≥ 50% reduction) occurred in 54.5% of treatment patients versus 8.3% in sham, and remission (MADRS < 9) in 18.2% versus 8%. Suicidal ideation and overall mood state also improved in the treatment arm. Resting-state fMRI analysis was obtained at baseline and within 24 h of the final session. Functional connectivity (FC; temporal correlation of spontaneous BOLD fluctuations) increased between the right subgenual/subcallosal ACC (BA 25) and four regions (left medial PFC, left middle frontal gyrus, right caudate, left orbitofrontal cortex) only in the treatment group (Oh et al. 2024). Prior studies have suggested that hypoactivation and decreased volume of the sgACC may be related to symptomatology of major depressive disorder (Rodríguez-Cano et al. 2014). However, FC between the stimulated DLPFC and the ACC did not change, and FC shifts were not linked to clinical improvement. No imaging or longer follow-up was reported; further durability of effects was not assessed (Oh et al. 2024).
Schachtner et al. 2025 conducted an open-label case series targeting the default-mode network (DMN) in 20 adults with MDD who also scored high on repetitive negative thought, a state thought to be associated with DMN hyperconnectivity in depression (Schachtner et al. 2025). Participants received up to 11 ten-minute sessions of low-intensity ultrasound over one to three weeks (five sessions in week 1, then three sessions per week for two additional weeks if early-remission criteria were not met). Sonications (400 kHz, 5 ms pulses at 10 Hz, ISPTA ≈ 670 mW cm⁻²) were targeted to the anterior medial prefrontal cortex (amPFC), a default-mode network hub. Changes were measured at baseline, again after one week, then again upon conclusion of the final session; by end of treatment, BDI-II scores fell by 10.9 points (p < 0.001) while HDRS-17 fell by 4.2 points (p < 0.001). Response rates were 60% (BDI-II) and 45% (HDRS); 35% met remission on both scales. Repetitive negative thought (PTQ) scores dropped 8.4 points (p < 0.001) and the magnitude of PTQ change predicted symptom improvement (R² = 0.67 for BDI-II change). Overall quality of life improved as assessed by physical, psychological, and environmental subscores of WHOQOL-BREF (p ≤ 0.001); social satisfaction was unchanged. No serious adverse events were detected. No assessments were performed beyond the treatment window, and durability of these gains remains unknown (Schachtner et al. 2025).
Riis et al. carried out a randomized, double-blind, sham-controlled crossover pilot in 22 adults with treatment-resistant depression or bipolar disorder in a current non-psychotic depressive episode; 20 participants crossed over, and 19 were used for per-protocol analysis (Riis et al. 2025). At each stimulation visit, participants completed a 1-hour MRI session with concurrent SCC sonication using a 10-minute block design (five 1-minute ON epochs interleaved with five 1-minute OFF epochs) to quantify target engagement, followed immediately by a 1-hour treatment session delivering 39–41 min cumulative real or sham stimulation across three adjacent SCC targets. Participants returned 6 days later (day 7), crossed over to the alternate condition, and the MRI and treatment sessions were repeated. Pretreatment HDRS-6 and PANAS-X were collected on days 0 and 7; PANAS-X was repeated immediately post-treatment, and HDRS-6 was repeated 24 h later (days 1 and 8) and 7 days later (days 7 and 14). Active stimulation produced a target-specific decrease in SCC BOLD activity at the group level (p = 0.028; usable fMRI n= 16) and was detectable at the individual level in 7/16 participants during the single 10-minute scan. Clinically, sadness (PANAS-X) improved immediately pre- to post-treatment, and HDRS-6 changes favored active stimulation at 24 h, with no sustained between-condition difference at 7 days. Tolerability was generally acceptable during and immediately after stimulation; however, two delayed severe psychiatric adverse events occurred following real stimulation (worsening depression with suicidal ideation, including one intentional overdose not requiring medical intervention), both resolving over the subsequent two weeks. This study built upon earlier results from the same group which reported the case of a 30-year-old woman with treatment-resistant depression who received a single 64-minute session of sonication, resulting in an immediate decrease in SCC BOLD signal on fMRI and a fall in HDRS-6 score from 11 to 0 in 24 h with sustained remission for 44 days (Riis et al. 2023). Converging evidence shows that reduction in SCC BOLD signal correlates with reduced MDD symptoms in both medical treatment and DBS (Argyelan et al. 2016).
In another case report of treatment-resistant MDD, Fan et al. 2024 delivered low-intensity ultrasound to three deep targets in a 46-year-old man with a wearable phased-array (Fan et al. 2024). Eight 5-minute pulse trains (500 kHz, 25 Hz PRF, 13% duty) were alternated on a 15-minute regimen on separate days. Sonication of the anterior nucleus of the thalamus (ANT) produced the clearest response: visual-analogue depression scores fell significantly across the two-hour session (t(2) = −8.87, p = 0.013), while resting-state fMRI demonstrated a reduction of default-mode network hyperconnectivity (Fan et al. 2024). In contrast, sonication of ventral capsule and bed nucleus of the stria terminalis (BNST) did not produce reductions in symptom scores.
Barksdale investigated the effects of amygdala-targeted low-intensity ultrasound in a cohort with mixed affective disorders, including MDD, anxiety, and trauma-related conditions (Barksdale et al. 2025). The study had two phases: an MR-guided target-engagement experiment (n = 29) in which a single 10-minute train of sonications produced an immediate 8–10% drop in amygdala BOLD signal, followed by an open-label treatment arm which repeated the protocol 15 times over three weeks. By the final visit, depressive symptoms and general-distress scores fell (HDRS-17: −5.3 ± 4.6, p = 0.01; MASQ: 5.7 ± 7.4, d ≈ 0.8), with parallel improvements observed on anxiety and PTSD scales. Notably, 24 non-serious adverse events were reported across 29 participants, with an even distribution of AEs across active versus sham groups. Reported adverse symptoms included decreased concentration, tingling in limbs or hands, headache, and dizziness or lightheadedness; mean reported symptom severity was 5/7. Almost all AEs resolved during the study visit, with the exception of two cases of persistent headache and one case of irritability, each of which resolved in the following days (Barksdale et al. 2025).
Attali et al. piloted a portable, navigated, metalens-based transcranial ultrasound system in five adults with treatment-resistant MDD (Attali et al. 2025). Each participant received 25 sessions (five, 5-min sessions per day for five days) targeted to the SCC. Depression severity fell rapidly: immediately post-treatment on day 5/5, mean MADRS dropped 60.9% from 37.2 ± 6.9 to 14.8 ± 8.6 by day 5 (p = 0.031); four of five patients met response criteria, while two achieved clinical remission. HDRS-17/−6 and QIDS-SR moved in parallel; resting-state fMRI showed increased SCC and left DLPFC connectivity, along with decreased SCC and hippocampal connectivity, potentially indicating network changes consistent with other rapid-acting antidepressant interventions. Transient sleepiness was the only common mild side effect (31/125 sessions), and post-treatment MRI was normal. However, by week 4, mean MADRS scores increased (reverted) 38.5% from post-treatment levels and stabilized at ~ 22% gains, with no patients still meeting response criteria. Maintenance dosing or booster sessions may be needed (Attali et al. 2025).
Generalized anxiety disorder (GAD)Mahdavi et al. 2023 (Kuhn group, UCLA) conducted an open-label pilot study investigating the effects of low-intensity transcranial focused ultrasound (tFUS) on 25 participants with treatment-resistant generalized anxiety disorder (GAD) (Mahdavi et al. 2023). The amygdala is thought to be a relevant part of pathophysiology in anxiety disorders, involved with abnormal fear and emotional processing; each participant received eight weekly 10 min sessions of low-intensity FUS directed at the right amygdala (650 kHz; 5 ms pulses at 10 Hz; duty 5%; ISPPA ≈ 14.4 W cm⁻²; ISPTA ≈ 720 mW cm⁻²) (Roy et al. 2013). At post-treatment assessment, anxiety as measured by the Hamilton Anxiety Rating Scale (HAM-A) and Beck Anxiety Inventory (BAI) fell markedly (HAM-A −12.64 ± 12.51, BAI − 12.88 ± 10.42, both p < 0.001) and 8/25 patients (32%) entered remission (HAM-A ≤ 14) with 16/25 patients (64%) rating themselves “much” or “very much” improved on the Patient Global Impression (PGI-I) inventory. No adverse events occurred (Mahdavi et al. 2023).
Later expanding these findings into a double-blind RCT, the Kuhn group (in partnership with other UCLA investigators) has recently published interim data from 23 treatment-resistant GAD patients (anticipated n = 48) treated with four weeks of once-weekly ultrasound targeting the right amygdala (Spivak et al. 2025). Interim results show an improvement in anxiety in both treatment and control groups, with possible differences between groups which merit further investigation; not enough data was included in the published abstract for inclusion in our analysis. The same group has recently published a clinical trial protocol for the most ambitious effort yet to study ultrasound neuromodulation in psychiatric populations: an ongoing, double-blind, sham-controlled RCT that plans to enroll up to 100 right-handed adults with high anhedonia and moderate-to-severe MDD (Rotstein et al. 2025). It is planned that these individuals will receive three sessions of low-intensity focused ultrasound to the left caudate head across a 5–9 day window. Results have not yet been reported as of this writing.
SchizophreniaAs of this review, Zhai and colleagues have reported the only series using FUS neuromodulation as a treatment for schizophrenia (Dong et al. 2017; Insel 2010; Zhai et al. 2023). They conducted a double-blind, randomized, sham-controlled study evaluating the efficacy of low-intensity transcranial ultrasound targeting the left DLPFC in 26 patients with predominantly negative symptoms of schizophrenia (Zhai et al. 2023). Participants were randomized (13 active, 13 sham) to 15 weekday sessions over three weeks. The Scale for the Assessment of Negative Symptoms (SANS) reflected a significant reduction in negative symptoms in the ultrasound group compared to the sham group (interaction effect: F = 16.965, p < 0.001, partial η² = 0.414). As the Group x Time interaction only signals that treatment trajectories diverged, post-hoc contrasts were required to pinpoint where the difference lay. Post hoc analysis revealed that the active group exhibited a substantial decrease in SANS scores (t = 7.397, p < 0.001) with no change in the sham group. Secondary outcomes, including the Positive and Negative Syndrome Scale (PANSS), also showed significant improvements in the active group. Cognitive performance on the Continuous Performance Test (CPT) improved significantly (F = 4.277, p = 0.050), though no significant effects were observed in the Trail Making Test, Symbol Coding, or Digital Span tasks. Further follow-up was not assessed. No serious adverse events were reported, though two active-group patients experienced transient difficulty falling asleep, which resolved (< 7 days). Additionally, prior motor-evoked-potential (MEP) work in a separate schizophrenia cohort using the same FUS parameters showed LTP-like increases in ipsilateral M1 excitability lasting 15 min, supporting the capacity to induce short term neuroplasticity using this ultrasound protocol (Zhai et al. 2023).
Substance use disorder (SUD)Mahoney et al. investigated the effects of low-intensity focused ultrasound targeting the nucleus accumbens (NAc), a target implicated in addiction and other reward disorders (e.g. OCD), in an open-label safety/feasibility pilot in four adults (n = 4) receiving concomitant comprehensive treatment for opioid use disorder (OUD) and polysubstance use (Peng et al. 2024; Mahoney et al. 2023). Each participant first underwent 5 min of sham sonication per hemisphere, then 20 min of active FUS to the bilateral nucleus accumbens; the first two subjects received a “lower” dose, while the latter two an “enhanced” dose. Cue-reactivity testing showed little acute effect with the low dose protocol, but in the enhanced protocol cue-induced craving for preferred drugs (e.g., heroin, alcohol, benzodiazepines) fell sharply during sonication and remained lower through 24 h post-treatment. Daily ecological-momentary-assessment over the following week confirmed significant craving reductions—for example, in Participant 3 mean opioid visual analog scale (VAS) cue-induced cravings fell from 3.6 ± 0.6 to 1.9 ± 0.4 and methamphetamine from 3.2 ± 0.4 to 0.0 ± 0.0 (all p < 0.01). At 90 days, maximum cue-induced craving scores were still lower than baseline for all four participants, suggesting durable benefit, though the small sample and absence of a sham-only arm limit inference. FUS was well-tolerated, produced no structural MRI changes, and only mild adverse events occurred (n = 10), such as transient headache, and all resolved within one day. Overall, the study provides preliminary evidence that bilateral NAc FUS is safe and may suppress substance cravings (Mahoney et al. 2023).
The same group expanded their earlier pilot into a prospective, single-arm trial of eight adults with severe OUD and multiple co-occurring substance use disorders (Rezai et al. 2025). They sonicated the bilateral NAc over four 5-minute blocks in a single session. Results were significant; measured on a patient-reported VAS 0–10 scale which quantifies cue-induced opioid craving intensity, median craving scores fell immediately (from 6.9 to 1.1 at 24 h; p < 0.002) and remained 91% lower at day 90 (from 6.9 to 0.6; p < 0.0001). Similar reductions were observed for cravings for both methamphetamine and cocaine. Urine toxicology confirmed that seven participants were abstinent at 30 days following treatment, while five remained drug-free through 90 days. Resting-state fMRI showed progressive decreases in NAc connectivity to the ventromedial prefrontal and anterior/posterior cingulate cortices over the 90-day follow-up period, suggesting dampening of reward circuit hyperconnectivity. The procedure was overall well-tolerated (9 mild headaches, 1 moderate anxiety, and no device-related serious adverse events or MRI abnormalities were noted) (Rezai et al. 2025). These results demonstrate the preliminary safety and potential durability of bilateral NAc FUS as an adjunct treatment for refractory OUD/SUD.
Obsessive-compulsive disorder (OCD)A published abstract from Jordan et al. reported preliminary results from a protocol exploring the effects of LIFU targeting the basal ganglia in a cohort of 21 patients with treatment-resistant obsessive-compulsive disorder (OCD). Dysfunction of the basal ganglia has previously been established as related to OCD symptom severity (Jordan et al. 2023). Initially, six participants received ultrasound targeting the caudate nucleus, but only two completed the protocol for reasons not detailed. The next fifteen participants received FUS targeting the ventral striatum; one was excluded due to travel concerns, and ten completed the protocol. Among these 10 subjects, seven individuals (70%) demonstrated a clinical response, defined as ≥ 35% reduction in Yale-Brown Obsessive-Compulsive Scale (Y-BOCS) scores or + 2 or greater movement on the Global Rating of Change (GRC). No serious adverse events were reported, though one participant withdrew due to worsening anxiety symptoms. The high dropout rate was observed primarily in the caudate nucleus group, whereas the ventral striatum appeared to be a more tolerable target. Long-term efficacy remains unclear as no further data has been published at the time of this writing (Jordan et al. 2023).
Comments (0)