Odontogenic infections arise from deeply decayed teeth, cysts or after tooth extraction [22]. The underlying spectrum of pathogens originates from the oral microbiome [23, 24]. Depending on the various stages of infection, either practising dentists or oral and maxillofacial surgery clinics are involved in their treatment [6, 25]. Abscesses with a tendency to spread should be treated with surgical drainage and intravenous antibiotic therapy in an inpatient setting [26]. Precisely these abscesses often lead to complications during therapy, which makes it difficult for the treating physician to anticipate the outcome and manage treatment [27,28,29]. In order to better predict the progression of patients with infectious diseases, predictive markers such as PCT or interleukin 6 have already become established in various other specialties. PCT was first used for risk stratification of patients with sepsis and has now become firmly established in emergency and intensive care medicine [12, 13]. Currently, practitioners treating odontogenic infections cannot rely on such additional decision-making criteria, which can lead to delayed identification of high-risk groups and prolonged hospital stays for mildly affected patients. Our study therefore aimed to evaluate the value of PCT as a predictive marker in extensive odontogenic infections and to identify further prognostic factors in order to improve the evidence for treating physicians in the future.
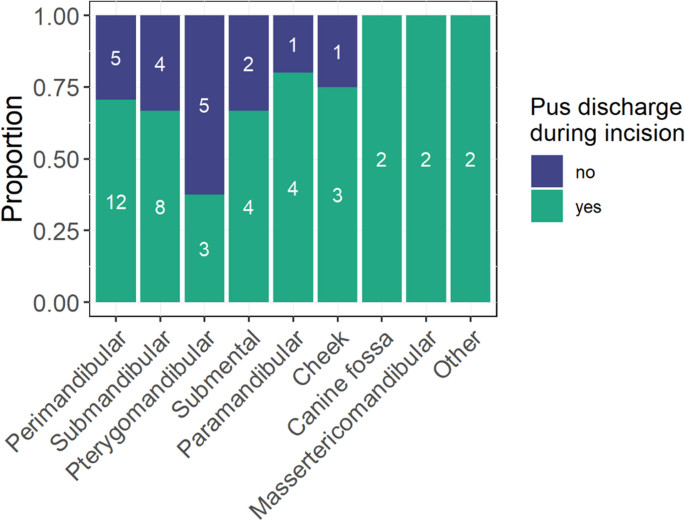
The course of action regarding appropriate treatment is determined during the initial contact with the patient. Thus, the presence of an infiltrate can be addressed with oral antibiotics, while patients with an abscess should undergo surgical drainage. Furthermore, if the abscess is spreading, the patient should be referred for inpatient treatment [26]. Decisions for or against surgery are primarily based on clinical experience and supported by laboratory parameters such as leukocytes or CRP. Whether laboratory parameters improve the differential diagnosis between infiltrate and abscess remains questionable, as our study data showed no association between inflammatory parameters (CRP, leukocytes and PCT) and the presence of pus during abscess incision. The distinction between infiltrate and abscess, on the other hand, was influenced by the location of the inflammation. In cases of pterygomandibular abscesses, surgical drainage more frequently failed to yield pus despite a clinical diagnosis of an abscess. However, it remains to be seen whether this diagnostic differentiation has an impact on treatment outcomes or whether both patients with infiltrates and abscesses benefit from drainage with lavage. Thus, our analyses did not show any significant effect of the presence of pus during abscess incision on the LOS.
In order to predict the LOS and better assess the discharge eligibility of patients, previous studies have attempted to identify prognostic markers for patients with odontogenic abscesses [7, 10, 30, 31]. Among inflammatory markers, CRP in particular has repeatedly been identified as a key parameter, with both CRP and leukocyte concentration being associated with prolonged hospitalization and increased recurrence rates [14,15,16, 32,33,34,35] Furthermore, a limited number of studies have recently begun to investigate the potential utility of other inflammatory biomarkers, such as PCT and presepsin, in the assessment of odontogenic infections. In contrast to established markers such as CRP, evidence supporting these novel biomarkers remains limited [36, 37].
Within our analyses, in addition to CRP, PCT also demonstrated potential utility as a prognostic marker, whereas leukocyte concentration showed no significant association. These findings suggest that PCT may serve as a useful prognostic marker for predicting LOS in patients with odontogenic infections.
In this regard, LOS differed in various PCT subgroups. Thus, patients with PCT concentrations > 0.5 µg/l remained hospitalized almost twice as long as patients with concentrations < 0.1 µg/l with regard to the median LOS. Results of our linear and tree-based analyses also supported the association between higher PCT concentration and a prolonged LOS.
In addition to the initial blood sample, changes in inflammatory parameters during treatment are also used to make decisions in everyday clinical practice. Therefore, the relationship between changes in blood values and LOS was also analysed in our study. In this regard, no association was found between the changes in PCT, CRP and leukocyte concentrations and LOS. This seems surprising, as a decrease in inflammatory parameters should hypothetically be associated with effective surgical drainage and antibiotic therapy, as well as an improvement in the patient’s condition. A possible explanation for this could be that the blood samples were usually taken on the first or second day after surgery, when inflammation values can be significantly influenced by the surgical procedure. Consequently, it does not seem sensible to take blood samples at this point in time. Further research is needed to determine the appropriate time to include the decrease in inflammatory parameters in the prognostic assessment and to avoid unnecessary costs associated with blood sampling.
With regard to the clinical relevance of our findings, our decision tree model identified three patient subgroups with median LOS of 4, 6, and 10 days. Although these absolute differences may appear modest at first glance, even a reduction of one to two inpatient days can be clinically meaningful by reducing hospital-associated risks and facilitating earlier recovery. In addition, these differences carry economic relevance within the German DRG reimbursement system. For submandibular abscess treatment, the lower and upper LOS thresholds are 1 and 7 days, respectively, with hospital stays beyond these thresholds being associated with financial losses. Early identification of patients at risk for extended hospitalization may therefore improve both patient management and resource utilization.
When interpreting our findings, several limitations should be considered. In particular, the relatively small sample size of 61 patients limits the robustness of the statistical analyses and carries a potential risk of overfitting. This reduces the generalisability of the results to other patient populations and therefore requires external validation. This limitation applies in particular to the tree-based model, which showed considerable variation in our bootstrap analyses. Although these thresholds are consistent with established laboratory recommendations [38, 39], their application in the context of odontogenic infections still requires further validation. With regard to the transferability of our findings, it should also be noted that the study was conducted during the COVID-19 pandemic. As clinical care pathways differed substantially during this period, these circumstances may have influenced both the patient cohort as well as admission and discharge practices. This could represent an additional confounding factor affecting LOS and might limit the applicability of our findings to non-pandemic healthcare settings. It should also be noted that further multivariable analyses are required to confirm the value of PCT as an independent prognostic parameter, as LOS may additionally be influenced by various medical and non-medical confounding factors. Furthermore, the retrospective study design represents an important limitation. As a result, discharge criteria could not be prospectively standardised or systematically documented. Future prospective randomized studies are therefore warranted to further investigate the role of PCT as an independent prognostic marker in odontogenic infections.
However, our findings indicate that PCT may represent a potentially useful prognostic marker in odontogenic infections and provide a preliminary decision tree model that could support the assessment of LOS in affected patients.




Comments (0)