Paediatric limb-salvage surgery remains challenging because reconstruction must be adapted to smaller skeletal dimensions, immature bone, and residual skeletal growth [4]. VFET has biological and mechanical advantages because it may provide a living graft capable of hypertrophy, remodelling, and potential longitudinal growth, but these advantages must be balanced against a high rate of complications [10, 21]. Few studies have described this complex reconstructive technique in children, and the reported results remain variable [4, 10,11,12, 21,22,23,24,25,26,27,28]. The present retrospective study describes the long-term clinical, radiological, and functional outcomes of VFET after paediatric oncological resection. In our series, graft hypertrophy was observed in all patients at one year, and neo-joint remodelling was observed in selected cases. However, growth behaviour was unpredictable, and mechanical complications were frequent. Consistent with previous studies, these patients often required additional surgery, although acceptable limb function could still be achieved in selected anatomical locations [10, 21, 23, 29].
The main published studies related to VFET are summarised in Table 2. Most available reports are small case series or reviews, often focused on a single anatomical site, which reflects the rarity of the technique and explains the absence of clear consensus regarding indications and expected outcomes.
Table 2 Summary of the main published clinical series on vascularized fibular epiphyseal transfer in paediatric oncological reconstructionIn our practice, the choice of reconstruction after paediatric tumour resection depends on patient age, tumour site, expected residual growth, defect size, joint involvement, soft-tissue sacrifice, adjuvant treatment, and expected survival. In older children and adolescents, reconstructive options may include modular or expandable endoprostheses, osteoarticular or intercalary allografts, vascularized fibular diaphyseal grafts, or combined biological reconstructions. However, in very young children, these options may be limited by small bone size, fixation difficulties, implant longevity, risk of mechanical failure, and inability to preserve growth potential. VFET was therefore considered in highly selected cases in which reconstruction required a living biological graft with potential for hypertrophy, growth, and articular remodelling.
Biological reconstructions have several potential advantages in growing children. They use living autologous tissue, may adapt to mechanical loading, may hypertrophy over time, and may provide durable reconstruction in long-term survivors. In the specific setting of VFET, transfer of a vascularized physis may also provide growth potential and, in selected cases, contribute to remodelling of a neo-joint. However, these reconstructions are technically demanding and expose patients to prolonged healing, delayed union, non-union, graft fracture, instability, deformity, and secondary procedures. These disadvantages were evident in our series, in which mechanical complications occurred in eight of nine patients.
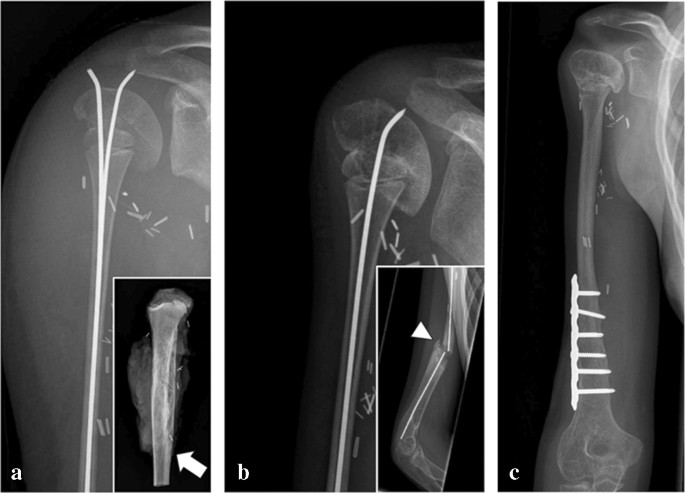
Like all large skeletal reconstructions, VFET is associated with a high rate of complications. Our overall mechanical complication rate was 89%, which is comparable with previous studies reporting complication rates of 40–85% [22, 29]. Fracture and non-union are among the most frequent complications after VFET [21, 29]. In the upper limb, the reported fracture rate varies between 20 and 41%, whereas in the lower limb it is approximately 35% [13, 30]. These values are similar to those reported after intercalary reconstruction with vascularized fibular diaphyseal grafts [13, 30]. Fractures may occur regardless of fixation method, as they have been reported with external fixation, intramedullary nailing, locking plates, or screws alone [14]. The tubular shape of the fibula, the mismatch between graft and recipient bone diameter, fixation constraints in small children, and the prolonged time required for adaptation and hypertrophy may contribute to this risk [22]. Importantly, late fractures may also occur despite apparent union and graft integration [10]. In our series, three late fractures after minor trauma occurred at two years, 8.2 years, and 15.6 years of follow-up despite radiographic bone healing.
Vascularized grafts have variable consolidation rates, with reported union occurring after a mean of 2.4–7.7 months [23, 25, 31]. In children, graft non-union has been considered less frequent than in adults, but it remains a major issue after VFET. In our series, 67% of patients required surgical revision for consolidation defects after a mean of 7.6 months. Several factors may explain this high rate of non-union, including graft length, recipient site, fixation method, vascular pedicle configuration, adjuvant radiotherapy, and the mechanical environment of the reconstruction. Combined allograft or double-barrel graft techniques have been proposed to improve mechanical stability and reduce the risk of secondary procedures [32, 33].
Bone formation and resorption vary according to Wolff’s law [34]. When the fibula is transferred to another anatomical site, the graft and transferred epiphysis must adapt to new mechanical, axial, and joint constraints [13, 14, 21]. Bone and joint remodelling might be expected to be greater in the lower limb because of weight-bearing, but the difference in calibre between the fibula and recipient bone, particularly in the femur, may make uniform transformation difficult [13, 14]. In our series, remodelling was observed in selected cases and could be favoured by surgical adaptation of the graft, such as osteotomy and plate fixation to reproduce proximal femoral anatomy. However, radiological remodelling did not necessarily guarantee better function [4, 10]. In the upper limb, especially around the distal radius or proximal humerus, remodelling may be more favourable and may be associated with better function of the neo-joint [23, 35]. This may be related to anatomical differences between the deep concavity of the acetabulum and the flatter glenoid, as well as to the greater tolerance for motion compensation around the shoulder [14].
Previous reports support the concept that VFET may be useful in skeletally immature patients when residual growth is expected [12]. The reported annual longitudinal growth of the transferred fibular physis varies from 0.54 to 1.72 cm/year [12, 22, 23]. Several factors may influence graft growth, including patient age, recipient bone anatomy, vascular supply, local mechanical constraints, and chemotherapy [23]. It is also important to consider the growth of adjacent bones to avoid progressive deformity, particularly in two-bone segments such as the forearm [14]. In our study, global annual growth of the graft could not be quantified because standardized serial radiographs were not available for all patients. However, growth arrest occurred in three patients, residual limb-length discrepancy persisted in two patients, and two patients developed graft overgrowth in the proximal humerus with instability and dislocation. These findings suggest that transfer of a vascularized physis may preserve growth potential, but does not guarantee predictable or clinically useful growth.
At long-term follow-up, functional outcomes were variable. In the upper limb, our mean MSTS score was comparable to those reported by other authors (69% versus 77–80%) [21, 22, 31]. When the axillary nerve and deltoid muscle are preserved, other reconstructive options such as composite prosthesis, the Capanna technique, or modular endoprosthesis may provide better function. However, in very young children, fibular grafts may be more suitable for small bone dimensions and may offer a biological option when growth potential is important. In the lower limb, VFET may appear attractive because of the possibility of biological reconstruction, but the consequences of complications are greater because of weight-bearing demands, limb-length issues, alignment, and joint stability. Each mechanical complication may negatively affect the final MSTS score, emphasizing the difficulty of achieving an ideal reconstruction in this setting.
The oncological outcomes in this series should be interpreted cautiously. No local recurrence was observed, and the three-year overall survival was 71 ± 18%. However, this small cohort included different tumour diagnoses, anatomical sites, treatments, and follow-up durations. Oncological survival is primarily influenced by tumour biology, systemic treatment response, surgical margins, and metastatic progression, rather than by the reconstructive technique itself. Therefore, the oncological results are reported descriptively and should not be overinterpreted.
This study has several limitations. First, it is retrospective and includes a small number of patients, reflecting the rarity of this reconstruction but limiting statistical interpretation. Second, the cohort was heterogeneous, including different diagnoses, anatomical sites, ages, and reconstructive contexts. Third, there was no comparison group, preventing direct comparison with endoprosthetic reconstruction, allograft reconstruction, vascularized fibular diaphyseal grafting, or other biological techniques. Fourth, standardized long-term radiographs were not available for all patients, so longitudinal graft growth could not be reliably quantified. Fifth, the long inclusion period may have introduced variability in imaging quality, surgical technique, fixation methods, adjuvant treatment, rehabilitation, and follow-up protocols. Therefore, the results should be interpreted as descriptive long-term observations rather than evidence of superiority or reproducibility.
Despite these limitations, this study provides long-term information on a rare reconstructive technique in paediatric musculoskeletal oncology. Its main value lies in describing the long-term biological behaviour of VFET, including graft hypertrophy, selected neo-joint remodelling, growth disturbance, late mechanical complications, and functional variability. These findings may help surgeons counsel families more accurately and reserve VFET for carefully selected patients in whom the potential benefits of biological reconstruction justify the risk of repeated procedures.




Comments (0)