Our study provides a comprehensive analysis of the clinical course of patients with COVID-19-associated SSC, including detailed imaging studies, histopathological assessment, evaluation of potential risk factors for severe disease progression and post-LT outcomes. All patients experienced severe COVID-19 and developed ARDS, with 35 requiring invasive mechanical ventilation, and 11 requiring ECMO. Nearly all underwent prone positioning, and all but one developed acute renal failure. These findings are consistent with previous reports [14, 26], supporting the notion that critical illness represents a prerequisite for this cholangiopathy.
The clinical relevance of COVID-19-associated SSC has evolved alongside the pandemic. Severe COVID-19 requiring ICU-level care, the prerequisite for this complication, has become markedly less common since the introduction of SARS-CoV-2 vaccination and improved antiviral treatment. Current WHO surveillance data indicate that global COVID-19-related hospitalizations and ICU admissions are now a small fraction of early pandemic levels [27]. Vaccination most likely confers indirect protection against SSC-CIP by reducing the risk of severe COVID-19 and, consequently, the risk of developing ARDS requiring prolonged mechanical ventilation. Nevertheless, patients with substantial comorbidities, including immunosuppression, continue to develop severe COVID-19 requiring prolonged intensive care. Furthermore, SSC-CIP is not unique to COVID-19 but occurs in various settings of prolonged critical illness associated with ARDS. Diagnostic approaches and prognostic markers described here may therefore also be relevant to SSC-CIP of non-COVID-19 etiology.
First described in patients with burn injuries, trauma, and sepsis [28], secondary sclerosing cholangitis of the critically ill (SSC-CIP) is a multifactorial condition that likely results from ischemia combined with altered bile composition, because the almost exclusively arterial perfusion of the biliary tree renders intrahepatic bile ducts particularly vulnerable to hypoxia [16, 29, 30]. Various hemodynamic and inflammatory insults may act cumulatively in this setting [29, 31, 32]. Supporting ischemia as a mechanism, COVID-19 patients who developed SSC showed more severe hypoxemia at presentation than those who did not [18]. Direct viral effects may further contribute: hepatocytes and cholangiocytes express angiotensin-converting enzyme 2 (ACE2) and SARS-CoV-2 co-receptor transmembrane protease serine subtype 2 (TMPRSS2) [33], and SARS-CoV-2 replication in cholangiocytes has been demonstrated in organoids [34], whether this translates into direct viral cytotoxicity in vivo remains speculative, and it is similarly unclear whether such cytotoxicity, the systemic immune response (“cytokine storm”), or both underlie the observed biliary damage [12].
It should be emphasized that the term 'COVID-19-associated SSC' as used throughout this manuscript refers to the clinical context, SSC arising during or following critical COVID-19 illness, rather than implying a directly virus-specific pathomechanism. SSC-CIP is well-established in critically ill patients of various etiologies independent of COVID-19 [16, 26,27,28], and the predominant pathogenic drivers in our cohort are most likely those common to SSC-CIP in general, such as prolonged ischemia of the biliary tree, hemodynamic compromise, hypoxemia, and the hepatotoxic effects of ICU-specific medications.
Among the latter, ketamine deserves particular consideration. Used for analgosedation in 71.9% of patients in our cohort for a median of 16 days, ketamine's biliary metabolite norketamine can precipitate in bile and has been directly linked to cholestatic liver injury in a dose- and duration-dependent manner in critically ill COVID-19 patients as demonstrated by Hartl et al. [15] and a study from our center [33]. Leonhardt et al. and Meersseman et al. similarly identified ICU-specific factors, including prolonged ventilation, hemodynamic instability, and sedation, as central mechanisms in SSC-CIP [17, 18]. Our previous study found SSC in 12% of COVID-19 ARDS patients but none in severe influenza A patients [13], suggesting that COVID-19 may represent a particularly high-risk context. However, whether this reflects a direct viral contribution or differences in ICU management, including the more widespread use of ketamine in COVID-19 ARDS, cannot be established from the present series.
SSC was diagnosed after a median of 91 days from diagnosis of COVID-19, similar to Hunyady et al. [26]. An earlier series reported a median of 118 days [14], possibly reflecting increased awareness later in the pandemic. Importantly, 80.6% were diagnosed with SSC post-ICU, stressing the need to consider SSC in both ICU patients and also in formerly critically ill patients recovering from their primary illness with persistent cholestasis. Notably, 14 patients (39%) had normal peak bilirubin values at ICU, while AP levels were significantly elevated in all patients, highlighting that SSC can present without jaundice. MRCP was the main diagnostic tool, showing intrahepatic strictures in all patients, but extrahepatic strictures in only three, consistent with typical feature of SSC-CIP developed from non-COVID-19 etiologies.
Liver biopsy was utilized for initial diagnosis in seven patients and in two further patients SSC was diagnosed using both, liver biopsy and MRCP. In total, 35 tissue samples of 26 patients (including seven follow-up tissue samples) were analyzed, representing the largest biopsy cohort reported in the literature. Findings mirrored SSC-CIP [24] and smaller COVID-19 series [22, 23, 35], ranging from mild to severe biliary injury, reflecting biopsy time and outcome variability. Vascular changes [36], including portal and hepatic artery branch thrombosis, were rare but consistent with previous reports [22, 35]. Crucially, follow-up biopsies allowed us to describe, for the first time on a tissue level, the rapidly progressing fibrosis in SSC-CIP after severe COVID-19, an accelerated fibrotic response also reported in SSC-CIP cases of other etiologies [24], including cases following septic shock [37] and severe trauma [30].
The complementary roles of MRCP and liver biopsy in the diagnostic work-up of COVID-19-associated SSC deserve further consideration. In the ICU setting, AP elevation has multiple potential causes, such as sepsis-associated cholestasis, drug-induced liver injury, total parenteral nutrition, or hemodynamic compromise. Importantly, persistent AP elevation during recovery from critical illness should prompt consideration of SSC even in the absence of hyperbilirubinemia. An MRCP should be considered once these typical causes have been excluded or seem insufficient to explain the degree of cholestasis. When characteristic biliary strictures are identified, the diagnosis can often be established. Liver biopsy may provide additional prognostic information and is warranted when MRCP findings are inconclusive. In patients with a rapidly deteriorating course, early biopsy may help determine the urgency of LT evaluation. A trans-jugular access is preferred given the coagulopathy inherent to critical illness. Although a clear disease-modifying therapy has not yet been established for SSC-CIP, treatment with UDCA can be initiated and endoscopic intervention by ERCP may be performed if indicated, once diagnosis has been made. Earlier diagnosis may additionally facilitate close monitoring, avoidance of further hepatotoxic exposures, and timely referral for LT evaluation in patients at high risk of disease progression.
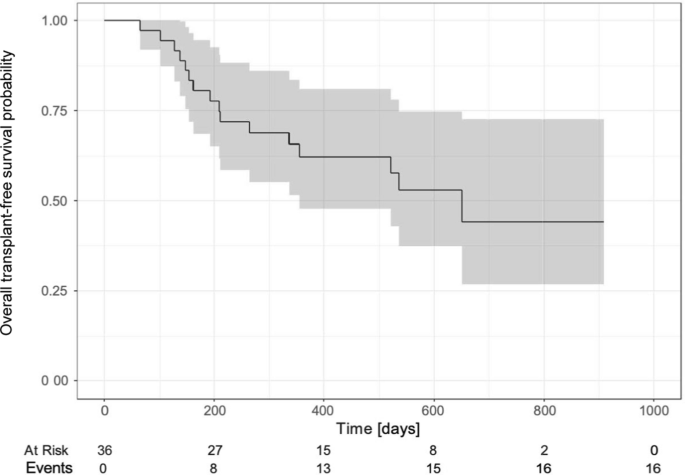
After a median follow-up of 537 days, 12 patients (33.3%) had died, four (11.1%) underwent LT, six (16.6%) developed decompensation, and 14 (38.9%) remained compensated. Median transplant-free survival was 651 days. Leonhardt et al. [18] reported a 12-month survival rate of 40% and Hunyadi et al. [26] described a median transplant-free survival of 22 months in a combined cohort of patients with COVID-19 and non-COVID-19-associated SSC. Together, these data underscore the severity of this entity of sclerosing cholangitis.
Regression analysis identified prognostic factors. Unlike other liver diseases, younger age did not protect against SSC progression [38]. Male sex predominated and was linked to worse outcomes, consistent with broader epidemiological data on COVID-19, which indicate higher mortality rates among male patients [39]. Patients who died or required LT had higher AP, bilirubin and lower albumin levels, reflecting cholestasis, hepatic dysfunction, and impaired synthesis. These markers are critical for assessing liver function and disease severity, highlighting their prognostic value in COVID-19-associated SSC. Elevated bilirubin and jaundice are known ICU mortality predictors [40,41,42], with bilirubin levels > 3 mg/dL associated with poor prognosis in hypoxic hepatitis [43]. High AST levels were particularly pronounced in patients who died, suggesting extensive hepatocellular injury. Significantly elevated d-dimer levels were indicative of coagulation dysfunction and multi-organ failure in the group with worse outcome. The apparent discrepancy between the low rate of histologically detected thrombosis and the markedly elevated d-dimer levels observed in our cohort warrants further consideration. In ICU patients, d-dimer is a highly non-specific marker, reflecting systemic activation of coagulation and fibrinolysis in the context of inflammation and multi-organ failure rather than necessarily indicating active microvascular thrombosis within the hepatobiliary system [19, 44]. Several factors may additionally explain this finding. Biopsies were performed at a median of 104 days after COVID-19 diagnosis likely did not capture peak thrombotic activity. In addition, sampling error limits the detection of focal microvascular lesions, and therapeutic anticoagulation during the ICU course may have reduced the likelihood of histologically detectable thrombi. Ischemic mechanisms including hemodynamic compromise, microvascular dysfunction, and biliary epithelial hypoxia may therefore contribute to biliary injury independently of overt thrombosis.
MRI findings did not identify predictive imaging markers for severe disease progression. However, parenchymal signal changes which were seen in 21 of 33 patients, predominantly affecting peripheral liver regions (12/21), were significantly more frequent in patients who survived without LT (seen in 17 patients, 81%) compared to those who died or were transplanted. This association remained significant in multivariable analysis. Similar T2- and DWI-hyper-intensity changes have been observed in primary sclerosing cholangitis, where they are thought to reflect changes due to inflammation [45]. Although parenchymal MRI signal abnormalities are often regarded as markers of severe liver disease, they may reflect a different biological process in COVID-19-associated SSC. We hypothesize that inflammatory changes involving the small peripheral bile ducts and adjacent parenchyma may represent a potentially reversible stage of injury in the remaining viable liver tissue, whereas extensive ischemic injury affecting the larger or central bile ducts may represent a more advanced stage characterized by irreversible biliary destruction and impaired drainage of larger biliary territories. This hypothesis is consistent with the observation that both parenchymal MRI signal changes and high-florid inflammation on histology were associated with transplant-free survival. However, the correlation between imaging and histopathological findings was limited, likely reflecting variability in biopsy timing. Given these limitations and the small sample size, this hypothesis remains speculative. Since histopathological data were available for 26 patients, we were also able to analyze histological features as potential predictors of clinical outcome. Statistically, portal edema and prominent bile infarcts were correlated with a worse prognosis, whereas septal fibrosis and a high-florid necroinflammatory pattern were linked to a more favorable mid-term outcome. These findings suggest that patients with a severe clinical course exhibit more pronounced signs of larger bile duct obstruction, including portal edema and prominent bile infarcts, and tend to experience rapid decompensation, leading either to LT or death before developing a high-florid cholestatic necroinflammatory pattern and progressive fibrosis. Whether patients with more advanced septal fibrosis and pronounced necroinflammatory activity may progress to cirrhosis and subsequent clinical decompensation later in the disease course remains unclear. However, liver biopsy may provide prognostic information in addition to its diagnostic role. Since the histopathological spectrum of COVID-19-associated SSC was similar to findings in SSC-CIP from other causes, the identified histological features associated with poor or favorable outcome could also be evaluated as predictive markers in non-COVID-19 SSC-CIP cohorts. Given that this is, to our knowledge, the first study to evaluate histological features as prognostic markers in COVID-19-associated SSC, these findings should be regarded as hypothesis-generating and require validation in independent cohorts before they can inform routine clinical decision-making.
No established treatment exists for SSC-CIP. UDCA may improve transplant-free survival in retrospective studies though this has not been confirmed in COVID-19-associated SSC [26]. UDCA has been shown to reduce SARS-CoV-2 susceptibility [46] and severity of COVID-19 in cirrhotic patients [47]. Most patients in our cohort received UDCA, but incomplete follow-up data precluded firm conclusions. Given its safety, UDCA is recommended. ERCP was performed in 13 patients mainly for cholangitis or biliary casts, but its long-term benefits remain unclear.
LT represents the only definitive therapy in advanced disease. Reports describe successful transplantation in COVID-19 cholangiopathy [14, 19, 20, 48], but mid- and long-term outcomes remain scarce. In our study, 17 patients (47.2%) were evaluated for LT, of whom six died during the evaluation and two on the waiting list. Four patients underwent LT and survived after a median follow–up of 530 days. Post-transplant complications included biliary anastomotic strictures (three patients), biliary cast syndrome and portal hypertension (one patient), with biopsy confirming ischemic cholangiopathy. Two grafts were from DCD donors, which may have increased biliary complications [49]. Whether COVID-19 SSC itself contributes to postoperative biliary complications remains unclear. However, increased bile duct injury has not been reported following LT in SSC-CIP of non-COVID-19 origin [50, 51]. One patient developed severe infectious complications but no bacterial cholangitis. Overall, our data demonstrate that LT is feasible with typical post-transplant complications. Larger studies on SSC-CIP of non-COVID-19 origin have reported 5-year survival rates of 76% [51] and 64% [50], comparable to control groups.
Several limitations of our study must be acknowledged. First, the retrospective design and inclusion of cases from a tertiary referral network introduce selection and referral bias, likely resulting in an overrepresentation of patients with more severe disease. Second, denominator data for the total number of severe COVID-19 patients treated at all three centers during the study period are not uniformly available, precluding robust incidence estimates for COVID-19-associated SSC. Third, the absence of a contemporaneous non-COVID-19 ICU control group precludes conclusions regarding causality or COVID-19-specific pathophysiology. The observed biliary pathology may reflect critical illness-associated mechanisms common to SSC-CIP of any etiology rather than effects directly attributable to SARS-CoV-2. Fourth, data collection relied on retrospective chart review, which may have resulted in missing or inconsistently recorded parameters at various time points, limiting the completeness and granularity of the dataset. Fifth, the sample size of 36 patients, while representing one of the largest published cohorts for this rare condition, limits the statistical power of our multivariable analyses and the robustness of derived prognostic models.
In conclusion, COVID-19-associated SSC carries a high risk of death or hepatic decompensation during and after ICU stay. It should be considered in patients with persistent cholestasis even in the absence of hyperbilirubinemia. We identified clinical, laboratory parameters, and for the first time, distinct histopathological features associated with adverse outcomes, whereas further specific histology findings and parenchymal signal changes on MRI were linked to a more favorable prognosis, offering novel insights into risk stratification. These prognostic markers warrant further validation in future studies, including cohorts with non-COVID-19 SSC-CIP. For patients with severe trajectories, early referral to specialized centers is essential as LT remains a potentially curative treatment option.




Comments (0)