MASLD has emerged as the most prevalent liver disease globally [1]. It encompasses a broad pathological spectrum, ranging from simple steatosis to steatohepatitis, liver fibrosis, and cirrhosis [3]. Increasing evidence supports the conceptualization of MASLD as a systemic disease rather than a condition exclusively confined to the liver, which is associated with an elevated risk of CVD and CKD [5, 6]. IR and MetS, the principal underlying pathophysiological features of MASLD, contribute to low-grade systemic inflammation [4]. This inflammatory milieu extends beyond hepatic inflammation and may contribute to endothelial dysfunction and atherosclerosis, thereby exacerbating the risk of both CVD and CKD [4]. This interplay among MetS, MASLD, CVD, and CKD is currently acknowledged as CKLM [9]. Except for systemic inflammation, liver fibrosis appears to play a pivotal role in this continuum, serving as an independent risk factor for cirrhosis, CVD, and CKD [10,11,12]. Consequently, identifying biomarkers that reflect both hepatic injury and the broader multisystem disease burden has become a priority in clinical research [21, 22].
In this study, we examined the association of liver-related non-invasive scores with CVD and a study-specific four-domain CRHM phenotype in individuals with T2DM and MASLD. In addition to routinely used scores such as FIB-4, APRI, and AAR, we assessed the discriminative utility of recently developed composite scores. We included the FNI, which incorporates both liver and metabolic parameters and thus likely reflects the underlying predisposing factors for MASLD better [19]. Furthermore, we applied the CORE model, which has been shown to correlate with the development of liver-related events [20].
In a cohort of 216 participants, approximately one-third had CVD. Individuals with CVD had a longer duration of T2DM and worse glycemic control. They also had higher Hellenic score II values and lower HDL concentrations. Elevated Cr levels were noted, suggesting increased susceptibility to CKD and, consequently, the four-domain CRHM. Patients with CVD exhibited significantly lower LDL cholesterol levels and a longer duration of treatment with GLP-1 analogs or SGLT2 inhibitors compared with those without CVD. However, these findings should be interpreted with caution because both variables are highly susceptible to confounding by indication. Current international guidelines strongly recommend intensive lipid-lowering therapy, predominantly with statins, for patients with established CVD or those considered at high cardiovascular risk [23]. Consequently, lower LDL levels in the CVD group are likely to reflect more aggressive therapeutic intervention rather than an intrinsically lower cardiovascular risk profile. In this context, LDL cholesterol may act as a marker of treatment intensity rather than a true biological determinant of cardiovascular outcomes. A similar consideration applies to treatment with GLP-1 analogs or SGLT2 inhibitors. Evidence from large cardiovascular outcome trials has demonstrated the cardioprotective and renal protective benefits of these agents in patients with T2DM, particularly among those with established atherosclerotic CVD or multiple cardiovascular risk factors [24, 25]. As a result, these medicines are preferentially prescribed to patients with CVD or at higher cardiovascular risk. Therefore, the longer treatment duration of GLP-1 analogs or SGLT-2 inhibitors observed among patients with CVD most likely reflects the implementation of contemporary guideline-directed therapy rather than a causal relationship between treatment exposure and the presence of CVD. Because both LDL levels and the duration of GLP-1 analog or SGLT2 inhibitor therapy are strongly influenced by clinical decision-making and treatment allocation, their inclusion in regression models could introduce substantial bias and obscure the relationship between liver-related biomarkers and cardiovascular outcomes. Given their strong dependence on treatment allocation and clinical indication, these variables were not included in the primary multivariable models; nevertheless, residual treatment-related confounding cannot be excluded. In particular, detailed information regarding statin type, dose, intensity, and duration was not consistently available. Moreover, GLP-1 receptor agonists and SGLT2 inhibitors may influence cardiovascular and renal outcomes themselves, while being preferentially prescribed to patients with established CVD, CKD, or higher cardiorenal risk. Thus, the observed treatment differences may reflect both treatment allocation based on baseline risk and potential treatment effects and should not be interpreted as causal associations with the clinical phenotypes examined.
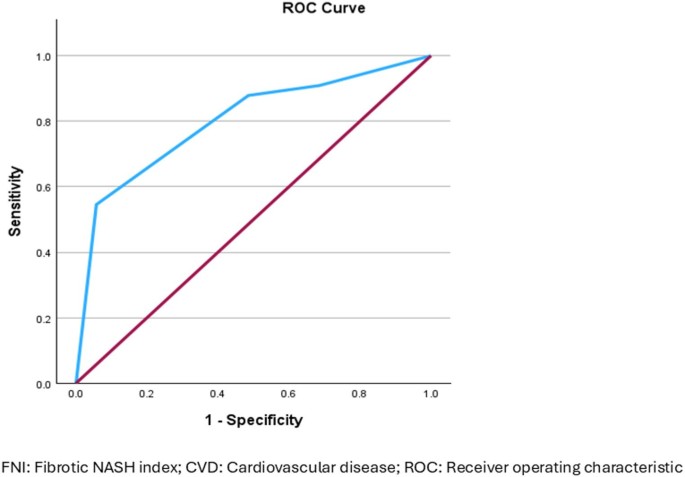
Notably, CVD was significantly associated with the newer composite scores, namely the FNI and the CORE model, but not with traditional markers such as FIB-4, APRI, and AAR. In addition, patients with CVD were more likely to have an FNI ≥ 0.33 than those without CVD, whereas no significant difference was observed in the proportion of patients with FIB-4 ≥ 1.3. In the multivariate analysis, age, Cr, and FNI were the only variables independently associated with CVD. However, the association between FNI and CVD was characterized by a wide confidence interval. This likely reflects the narrow distribution of FNI values within the study population and the relatively small number of patients with high FNI values. Therefore, although FNI remained independently associated with CVD, the magnitude of the observed effect should be interpreted with caution.
The differing compositions of FNI and FIB-4 may partly account for their distinct associations with CVD. FNI incorporates several metabolic variables, including BMI, HDL cholesterol, and HbA1c, which are themselves closely associated with cardiovascular risk. Therefore, the observed association between FNI and CVD may reflect, at least in part, the broader cardiometabolic information incorporated into the score rather than a specific metabolic-inflammatory mechanism. The absence of associations between CVD and FIB-4, APRI, or AAR is noteworthy but does not establish that metabolic, rather than fibrosis-related, pathways underlie the observed findings. Indeed, the present study did not directly assess systemic inflammation, endothelial dysfunction, or liver fibrosis. Therefore, any biological explanation for the differential associations of these scores remains hypothesis-generating.
Interestingly, combining FNI with Hellenic Score II yielded higher discrimination for CVD than either score alone. However, both scores incorporate HDL cholesterol, resulting in partial structural overlap. Although FNI and Hellenic Score II were not significantly correlated in our cohort (rho = 0.083, p = 0.339; data not shown), this does not establish their independence, as the lack of a significant correlation may reflect contributions from other, non-overlapping components apart from HDL. Therefore, the higher discrimination of the combined model should be interpreted cautiously, and its incremental value requires confirmation in an independent cohort. Furthermore, because the cut-offs were derived and their discriminatory performance evaluated in the same cohort, the observed AUROCs are considered exploratory.
Regarding patients with the four-domain CRHM phenotype, the FIB-4 and APRI scores were significantly elevated, and platelet counts were notably lower than in individuals without CRHM. Patients with CRHM also tended to have higher CORE scores than those without CRHM, but the difference did not reach statistical significance (p = 0.062). Additionally, subjects with CRHM had FIB-4 scores ≥ 1.3 more often than those without CRHM. The multivariate analysis confirmed a significant association between FIB-4 and CRHM, with a 5.4-fold increase in the odds of CRHM per 1-unit increase in FIB-4. In contrast, APRI was no longer significantly associated with CRHM after adjustment, suggesting that FIB-4 may provide more robust information regarding the fibrosis-related component of CRHM in this cohort. Interestingly, the addition of the CORE model to FIB-4 resulted in numerically improved discriminative ability for CRHM compared with FIB-4 alone (AUROC 0.81 vs. 0.69, respectively). Bootstrap resampling provided some evidence of internal stability in the observed associations, particularly for FNI, Hellenic Score II, and FIB-4, whereas CORE’s contribution to the combined model was less stable. However, bootstrap assessment of coefficient stability does not establish model calibration or external validity. Accordingly, the observed discriminative performance and derived cut-offs should be considered exploratory and should be validated in independent cohorts.
The association between FIB-4 and the four-domain CRHM phenotype should be interpreted cautiously. Although FIB-4 is widely used for risk stratification of advanced liver fibrosis, it incorporates age, AST, ALT, and platelet count, variables that are not specific to hepatic fibrosis and may themselves be associated with cardiovascular, renal, or systemic disease. Thus, higher FIB-4 values among participants with the four-domain CRHM phenotype may reflect a combination of hepatic and extrahepatic factors rather than liver fibrosis alone. This consideration is particularly relevant because FIB-4, as well as the other non-invasive scores evaluated in the present study, is a surrogate marker rather than a direct measure of liver fibrosis. Since liver elastography, other imaging-based fibrosis assessments, and liver histology were not available in our cohort, we cannot determine whether the observed associations are driven by true differences in fibrosis severity or by contributions from individual score components. Consequently, the biological mechanisms underlying the observed association cannot be established from the present data, and any interpretations should be considered hypothesis-generating rather than conclusive and should be confirmed in future mechanistic and longitudinal studies.
The absence of an association between FIB-4 and CVD in the present study appears inconsistent with our previous findings [21]. However, important methodological differences may explain this discrepancy. In the earlier study, the CVD group also included patients with HF. In contrast, HF was excluded from the current analysis because it is a heterogeneous clinical syndrome not exclusively attributable to atherosclerotic disease. Furthermore, kidney function was not assessed in the previous cohort; therefore, some patients classified as having CVD may also have had concomitant CKD and would potentially have fulfilled the four-domain CRHM phenotype. These differences in definitions and patient characterization may partly explain the differing associations observed between FIB-4 and CVD across the two studies [21].
Our findings highlight the substantial burden of multisystem comorbidity in patients with T2DM and MASLD. In this selected cohort, approximately 17% of evaluable participants exhibited concomitant metabolic, hepatic, renal, and cardiovascular involvement, as defined by our study-specific four-domain CRHM phenotype. Because T2DM and MASLD were inclusion criteria, this phenotype primarily identified patients in whom CKD and established atherosclerotic CVD additionally coexisted. Our study-specific four-domain phenotype should be distinguished from the contemporary CKM and emerging CKLM frameworks, which provide broader, more granular approaches to multidomain risk assessment [9]. In particular, these frameworks incorporate earlier stages of cardiometabolic risk and more comprehensive characterization of renal and hepatic involvement, including albuminuria and non-invasive assessment of liver fibrosis [9]. Our retrospective dataset did not permit complete implementation of such a framework; therefore, the four-domain phenotype used in the present study should be regarded as a simplified exploratory construct rather than an alternative staging system.
An important potential clinical implication of our findings is that liver-related non-invasive scores routinely obtained in patients with T2DM and MASLD may provide information that extends beyond their conventional hepatic applications. These scores are simple and inexpensive to calculate and are based on clinical and laboratory parameters that are readily available in routine practice, without requiring additional specialized investigations. Their potential value in this context would not be to replace direct identification of established CVD or CKD, but rather to provide an additional signal of the broader multisystem disease burden associated with MASLD. In particular, the association of FNI with established CVD and of FIB-4 with concomitant cardiovascular and renal involvement suggests that different scores may capture partly different dimensions of this burden. In clinical settings where patients with T2DM and MASLD are often managed across different specialties, an elevated liver-related score could prompt a more comprehensive assessment of cardiovascular and renal comorbidities rather than being interpreted solely within a hepatic context. Moreover, the higher apparent discrimination observed with combined models suggests that integrating complementary, readily available non-invasive markers may ultimately yield a more informative multidomain assessment than individual scores considered in isolation. However, the present study does not demonstrate that such an approach improves the detection of previously unrecognized disease, clinical decision-making, or patient outcomes, and its potential clinical utility requires prospective validation. Furthermore, these markers were evaluated only in relation to the presence of CVD and CRHM at the time of recruitment, rather than as predictors of future outcomes. Therefore, no conclusions can be drawn about their prognostic value for cardiovascular, renal, or hepatic events. Future longitudinal studies are needed to determine whether these markers can reliably predict disease progression and adverse outcomes across the CRHM spectrum.
Several limitations should be acknowledged. First, liver fibrosis was not assessed with imaging-based methods, such as transient elastography or magnetic resonance elastography, and histological confirmation was unavailable. Consequently, fibrosis risk was evaluated exclusively using serum-based non-invasive scores, and the presence or severity of hepatic fibrosis could not be directly confirmed, as the non-invasive tests used are surrogate markers rather than direct measures of fibrosis. In addition, albuminuria was not systematically available, and renal involvement was therefore defined according to persistent reduction in eGFR. Consequently, our study-specific four-domain phenotype does not capture the full spectrum of renal involvement incorporated into contemporary multidomain CKLM frameworks. Second, the retrospective cross-sectional design precludes causal inference and is susceptible to residual confounding. Furthermore, because liver-related biomarkers and clinical outcomes were assessed at the same point, the possibility of reverse causation cannot be excluded. Therefore, the observed associations should not be interpreted as evidence of a temporal or causal relationship between liver-related scores and CVD or the four-domain CRHM. Third, detailed information regarding statin type, dose, intensity, and treatment duration was not consistently available, preventing adequate adjustment for lipid-lowering therapy. The lower LDL cholesterol levels observed among participants with CVD and the four-domain CRHM phenotype may therefore reflect differences in treatment intensity rather than differences in underlying cardiovascular risk. Similarly, GLP-1 receptor agonists and SGLT2 inhibitors are preferentially prescribed to patients with established or increased cardiovascular and renal risk and may themselves modify cardiorenal outcomes. Consequently, confounding by indication and residual treatment-related confounding cannot be excluded. Fourth, the relatively small number of participants exhibiting the four-domain CRHM phenotype (n = 35) represents an important limitation. This, together with the data-driven selection of candidate variables for multivariable modeling, may have increased the risk of model instability and overfitting. The wide confidence intervals observed for some estimates further indicate substantial imprecision. Therefore, the multivariable findings should be considered exploratory and hypothesis-generating and should be confirmed in larger independent cohorts. Fifth, the discriminatory performance of the individual and combined scores was evaluated in the same cohort from which the cut-offs were derived, using the Youden index; therefore, the reported AUROCs and cut-offs may be considered exploratory. Although bootstrap resampling was performed as an internal assessment of regression-coefficient stability, it does not replace external validation or formal assessment of model calibration. Consequently, the reported cut-offs and discriminatory estimates should not be applied clinically without validation in independent cohorts. Sixth, there is some overlap between the FNI and the Hellenic Score II because both scores incorporate HDL cholesterol. Although these models also contain distinct variables, part of the improved discriminative ability observed for the combined model may reflect information shared by this common component. Finally, our study population comprised patients with established T2DM and MASLD who were evaluated at a tertiary referral center. Consequently, the proportion of participants exhibiting the four-domain CRHM phenotype should not be interpreted as the prevalence of an established syndrome or generalized to broader populations.
In conclusion, this study supports the view that MASLD in patients with T2DM may occur within a broader context of cardiovascular, renal, hepatic, and metabolic comorbidities. Our findings suggest that liver-related non-invasive scores may be differentially associated with aspects of this multisystem disease burden. In particular, FNI was associated with established CVD, whereas FIB-4 was independently associated with the study-specific four-domain CRHM phenotype. Moreover, the higher apparent discrimination observed with combined models suggests that integrating multiple non-invasive markers may improve the assessment of cardiovascular and multidomain disease burden compared with individual scores alone. However, these findings should be considered exploratory and hypothesis-generating, given the cross-sectional design, the limited number of participants with four-domain involvement, the lack of direct evaluation of liver fibrosis, and the absence of external validation. Independent validation in larger prospective cohorts is required before any clinical implications can be drawn.


Comments (0)