Comparative analysis of kidney growth and function in children with different types of unilateral congenital renal anomalies: a 2 year follow-up study
Purpose
Unilateral congenital kidney anomalies (renal agenesis, hypoplasia, ectopia, MCDK) may affect kidney growth, blood pressure, and function over time. Comparative compensatory responses among different anomalies remain poorly defined.
Methods
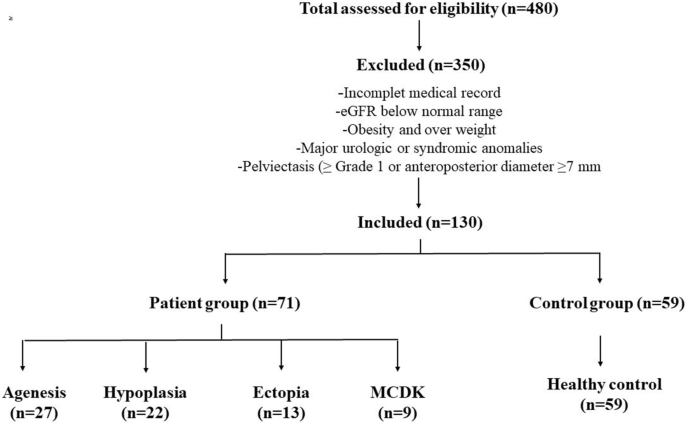
This longitudinal multicenter study included 130 children (71 patients, 59 controls) aged 0–19 years. Kidney volumes were measured by ultrasound at two visits (median interval two years). Age- and Body Surface Area (BSA)-adjusted Z scores for total kidney volume (TKV) were calculated using LMS reference data. Office blood pressure, eGFR, and urinary albumin-to-creatinine ratio (UACR) were assessed at both visits.
Results
Right-sided pathology predominated (~ 60%). At the first visit, the hypoplasia group had higher diastolic blood pressure than controls (p=0.007). Over time, TKV Z scores increased in the control group (both Z-age and Z-BSA +0.09, p=0.001), remained stable in the renal agenesis and MCDK groups (p>0.05), but decreased in hypoplasia (Z-age − 0.49, p=0.023; Z-BSA − 0.47, p=0.028) and ectopia (Z-age − 0.1, p=0.042; Z-BSA − 0.09, p=0.043). eGFR improved in hypoplasia (p=0.004), ectopia (p=0.043), and controls (p=0.003). Diastolic blood pressure increased mildly in the renal agenesis (p=0.048). Albuminuria remained within the normoalbuminuric range in all groups; however, it was higher in renal agenesis group at both visits (p=0.020 and p<0.001, with a significant increase over time (p=0.045).
Conclusion
Different unilateral congenital kidney anomalies exhibit distinct compensatory patterns. Renal agenesis achieves effective hypertrophy, yet accompanied by higher albuminuria and mild increase in diastolic BP, whereas hypoplasia and ectopia show modest Z score declines with preserved function and lower albuminuria. Absence of progressive hypertension suggests nonpharmacological measures may suffice for BP control in early-to-middle childhood. These findings support an optimal window of compensatory growth, which requires further study.





Comments (0)