Subjective quality metrics had ≥ 85% adherence with high inter-reviewer agreement, except for the initial lateral rectal image acquisition not being properly timed to early filling and visualization of the appendix and/or terminal ileum. There was < 85% adherence to two objective quality criteria metrics including study performed without direct exposures (63%) and scout image present (83%). This was unexpected at a tertiary, pediatric hospital staffed exclusively by subspecialist fellowship-trained pediatric radiologists.
Radiology practice requires continuous quality assessment even at large pediatric referral centers, with subspecialist pediatric radiologists. Pediatric radiologists are trained to utilize dose-reduction features such as pulsed fluoroscopy, last-image capture, and to minimize fluoroscopy time and magnification [15, 16]. However, studies should also meet the diagnostic objectives. The objective of a CE in neonatal obstruction is to narrow down the possible causes and identify those etiologies requiring surgery [5]. The principal differential diagnoses identified through CE are Hirschsprung disease, colonic atresia, small left colon syndrome, meconium ileus and small intestinal atresia [5, 6, 17].
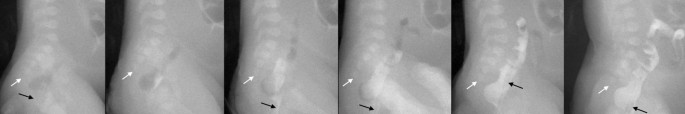
A recent study by Baad et al. [5] summarized and investigated the following features required for distinguishing the main pathologies sought for in neonates with low obstruction: scout view; rectosigmoid index reversal; serrations; transition zone and Microcolon (with abrupt ileal cut off vs. many ileal meconium filling defects). For identifying these important radiologic features, the CE procedure must be performed appropriately and the ACR–SPR practice parameters address these requirements [13]. The scout image is used for (a) identifying calcifications which may indicate meconium peritonitis; (b) pneumatosis, portal venous gas and pneumoperitoneum which would result in the procedure being cancelled/postponed and surgical decision making, and (c) the obstruction pattern (no obstruction, low obstruction, high obstruction) which would confirm whether the contrast enema is the appropriate test. The lateral view is integral to the diagnosis of Hirschsprung disease, and requires the sacrum be included for evaluation of patient positioning. Ensuring the spasmodic abnormal distal portion of the rectum in Hirschsprung disease is not distended out by either a large caliber rectal tube or by overfilling, requires that the rectum be imaged during early filling. These quality components of the study are required for the rectosigmoid ratio to be assessed, which has a high specificity for diagnosing Hirschsprung disease [5].
Getting contrast through the entire colon and into the terminal ileum should be a goal of all neonatal contrast enemas, noting however, that contrast will not pass through a colonic atresia by definition, and that it may not be possible to reflux contrast into the terminal ileum in up to a third of cases due to ‘competency of the ileocecal valve’ [5]. In addition, in instances where a transition zone is identified, further filling of dilated more proximal colon is not recommended, and the caecum will not be demonstrated. However, some of the important diagnoses in the context of neonatal contrast enema rely on showing the whole colon and distal ileum.
Finding a colonic transition zone (if the rectum is deemed normal) has a high sensitivity for diagnosing Hirschsprung disease [all the other features - recto-sigmoid index and serrations are less sensitive and more specific]. In addition, detecting a microcolon for diagnosing meconium ileus and small intestinal atresia is mandatory in neonatal CE since surgical intervention is necessary for some cases of meconium ileus and all cases of atresia [5]. A microcolon by definition is a small caliber colon throughout its length, which requires getting contrast to the caecum, and which in turn is recognized by opacifying and identifying the appendix or terminal ileum. Furthermore, once a microcolon is diagnosed, distinguishing ileal atresia (always requiring surgery) and meconium ileus (often treatable without surgery) depends on contrast be refluxed into the terminal ileum – an abrupt ileal cut off with a small caliber terminal ileum indicates small intestinal atresia while a distended terminal ileum with many meconium filling defects indicates meconium ileus.
The Pause and Pulse campaign (of the Image Gently program), is focused on strategies for optimizing the dosage in pediatric fluoroscopy [18]. Documentation of radiation exposure indices is more relevant than documentation of fluoroscopic time, but the ACR-SPR practice parameter, recommends both that fluoroscopy time be minimized and recorded [13] and where possible that other metrics relative to radiation dosage, such as dose rate, DAP (dose area product), or air kerma be recorded [13]. The radiation dose and fluoroscopy time in our study were documented in 90% (63 CEs). The ACR-SPR, is also clear in recommending the use of ‘digital pulsed fluoroscopy, last image hold, and screen save features help to reduce radiation dose’ when possible [13]. They specifically state that screen saves are ‘preferable to spot images or overhead radiographs’ for minimizing radiation dose. 37% of cases in our study included at least one direct exposure (spot image). We note that exposures may be necessary according to radiologists’ discretion. When utilizing pulsed fluoroscopy and low dose techniques, there may be a tendency to capture spot films to improve visualization of detail. However, neonatal contrast enemas rely largely on identifying caliber differences and filling defects which do not require high detail but do require imaging of the whole colon and even terminal ileum where possible.
Limitations
As this was a single-center retrospective study conducted at a large pediatric tertiary hospital, the observed image quality may not be fully representative of that achievable in smaller pediatric centers or general hospitals.
The current American College of Radiology and Society for Pediatric Radiology [ACR–SPR] practice parameters were revised in 2021 while this examinations for this study were from February 2019 to August 2022 i.e. some predate the revised practice parameters.
Two of the 6 subjective parameters, ‘entirety of the colon visualized through to cecum’ and ‘appendix and/or terminal ileum visualized’ may not be achieved because of practical considerations and are not always quality failure. As mentioned in the manuscript above, contrast will not pass through a colonic atresia by definition, and it may not be possible to reflux contrast into the terminal ileum in up to a third of cases due to ‘competency of the ileocecal valve’ [5]. In addition, in instances where a transition zone is identified, further filling of dilated more proximal colon is not recommended, and the caecum will not be demonstrated.




Comments (0)