The impact of CRP as an objective inflammatory marker is one of the items highlighted on the research agenda of the ASAS-EULAR 2022 management recommendations [3]. The ASAS-EULAR recommendations task force has listed elevated CRP in patients who have ASDAS HDA despite treatment with NSAIDs as the first item that increases the likelihood of response to treatment with b/tsDMARDs, and that, when available, CRP should be considered when starting a b/tsDMARD, irrespective of the presence of radiographic sacroiliitis [3].
Several studies have identified elevated CRP as one of the strongest predictors of response to TNFi therapy in patients with r-axSpA. For example, in 2004, two placebo-controlled, randomized trials conducted in Germany with infliximab (n = 69) and etanercept (n = 30) in patients with r-axSpA reported an elevated CRP level at baseline as one of the valuable predictors of achieving treatment response, assessed by BASDAI50 response [4]. Following this study, a post hoc analysis of infliximab (ASSERT) and golimumab (GO-RAISE) (n = 635) identified elevated baseline CRP levels (> 20 mg/L) as one of the strongest predictors of achieving BASDAI50 at week 12 [5].
Most recently, a retrospective cohort study of 10 randomized clinical trials (2002–2016) conducted on patients with active r-axSpA and receiving treatment with a TNFi (N = 1899) using machine learning identified elevated CRP levels at baseline as the strongest predictor of achieving an ASDAS major response (defined as a decrease of 2.0 points or greater in ASDAS) at week 12, using both logistic regression (LR) and random forest (RF) algorithms. The same study identified lower CRP level at baseline as the strongest predictor in both LR and RF models of failing to achieve ASDAS clinically important improvement (CII, defined as a decrease of 1.1 or greater in ASDAS) by week 12. However, MRI information, which is not always reported in studies, was not considered in these analyses [19].
These findings have been supported through real-world evidence provided by the EuroSpA collaboration, an analysis including 19,422 patients across 15 European registries who had both r-axSpA and non-radiographic axSpA and were receiving treatment with TNFis. The analysis found that among these patients, a high baseline CRP level (> 10 mg/L) was a positive predictor of ASDAS ID, ASDAS CII, and 12-month TNFi retention [20].
Data on the impact of baseline CRP levels on non-TNFi b/tsDMARDs has been building recently and may allow us to consider novel treatment paradigms to achieve personalized medicine goals. This includes a post hoc pooled analysis of the pivotal studies (MEASURE 1 and MEASURE 2), which showed that secukinumab at 150 mg was effective in both patients with normal and elevated CRP levels at week 16 and up to week 156 [12]. Another post hoc study pooled tofacitinib-treated patients with r-axSpA from phase II and phase III clinical trials (N = 372) and investigated the treatment efficacy in patients stratified by CRP level at baseline, using ≥ 5 mg/L and ≥ 10 mg/L as the cutoffs for elevated CRP levels. At week 12, the response rates for tofacitinib were generally higher than PBO, regardless of baseline CRP level for the pooled patient population, and at week 16 for the patients in the phase III trial only [13]. Both studies demonstrated higher efficacy for patients with elevated CRP at baseline, while also showing that patients with a normal CRP level at baseline could show good improvement. This contrasts with what has been previously reported for the efficacy of TNFis.
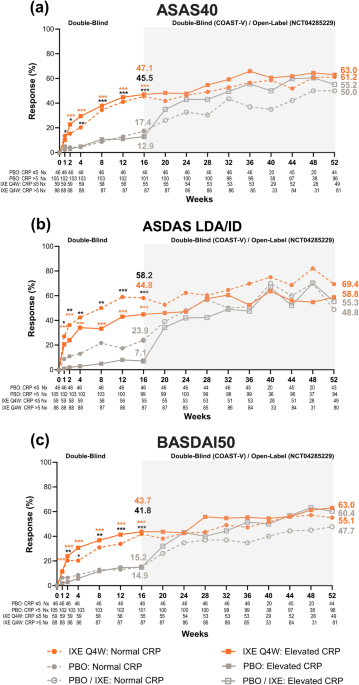
The COAST-V study has, despite the small sample sizes, shown a different response pattern between IXE, ADA, and PBO when patients were stratified by baseline CRP level. The ASAS40 response among patients with normal CRP was 19%, 21%, and 35% for patients treated with PBO, ADA, and IXE, respectively; among patients with elevated CRP, the response was 18%, 46%, and 56% for patients treated with PBO, ADA, and IXE, respectively. Thus, with a normal initial CRP level, the ASAS40 response at week 16 for ADA was similar to PBO (21% and 19%), followed by IXE (35%). A similar pattern was observed across BASDAI50, ASDAS LDA/ID, and the proportion of patients achieving ASDAS major improvement [21]. In a separately published analysis from the COAST-V study, IXE Q4W provided significant improvements in ASAS40 responses at week 16 with both baseline CRP levels of ≤ 10 mg/L or > 10 mg/L [22], and in a combined analysis from COAST-V and COAST-W, a significant improvement was found in this outcome for both ≤ 5 mg/L or > 5 mg/L CRP level at baseline [14]. Notably, the participants of COAST-W were more treatment-refractory, having previously been treated with one or two TNFis. Consistent with the findings reported here, ASAS40 response rates at week 16 were numerically higher with IXE versus PBO in these patients with both normal and elevated CRP levels [14].
In this analysis, with patients pooled from COAST-V and NCT04285229, IXE showed significant improvements over PBO in ASAS40, ASDAS LDA/ID, and BASDAI50 as early as week 2 and maintained efficacy through 52 weeks, irrespective of CRP level at baseline. Improvements in ASAS-HI and SF-36 PCS were similarly observed as early as week 4. This finding was particularly evident in patients with concomitant MRI-detected inflammation of the spine and/or SIJ. Significant improvements were observed as early as week 1 for spinal pain and morning stiffness, and at week 4 for patient global assessment and BASFI regardless of CRP level. Baseline demographics and clinical characteristics were broadly comparable between patients with normal and elevated CRP, except for concomitant oral corticosteroids, ASDAS disease activity category, total MRI-SPARCC spine and SIJ scores, and the percentage of patients with MRI-SPARCC spine score ≥ 2; nevertheless, the proportion of patients with evidence of inflammation on MRI, defined as MRI-SPARCC spine or SIJ score ≥ 2, was similar. The observed differences are partly explained by stratification of the cohort by baseline CRP level. Because CRP is a component of ASDAS-CRP, a higher proportion of patients in HDA/vHDA categories reflects a higher level of systemic inflammation rather than baseline imbalance. Similarly, a higher baseline MRI-SPARCC score in the spine and SIJ among patients with higher CRP is consistent with CRP as a marker of systemic inflammation and is expected to correlate with objective MRI markers of inflammation. Nevertheless, when disease activity was assessed using instruments that do not include CRP (BASDAI, BASFI, morning stiffness), the baseline disease burden was comparable between groups. While a difference in oral corticosteroids was also noted, oral corticosteroids are not a standard treatment approach in the management of axSpA, and additionally, the numbers in our cohort were low, precluding further investigation through subgroup analysis.
These data highlight that the disease burden in patients with r-axSpA is comparable across normal and elevated CRP levels at baseline in the pooled studies. At week 16, patients treated with IXE who had no evidence of MRI inflammation in both spine and SIJ achieved a similar treatment response when assessed by ASAS40, ASDAS LDA/ID, and BASDAI50 with normal CRP (33.3%, 46.7%, and 40.0%, respectively) or elevated CRP level (33.3%, 26.7%, and 40.0%, respectively). Yet, the number of patients with normal CRP was low, and PBO response rates at week 16 for ASAS40 and ASDAS LDA/ID were high, both factors that preclude definite conclusions in this subgroup of patients (no MRI inflammation, normal CRP). A similar pattern was observed at week 16 for patients who presented with evidence of MRI inflammation in either the spine or SIJ at baseline, and the magnitude of response observed at week 16 was maintained through week 52 across the groups above. Although this demonstrates that patients with normal and elevated CRP behave similarly when corrected for the absence or presence of MRI inflammation, and that the impact of the treatment response by week 16 is not significantly changed, this analysis should be approached with caution due to the small sample sizes and imbalance in some of the arms.
A strength of this study is the inclusion of MRI data, which enabled the assessment of treatment efficacy within subgroups stratified by measures of MRI-detected inflammation, as well as by CRP level at baseline. This provides a nuanced understanding of treatment response across broad patient profiles. The limitations of this study include the sample sizes available within specific subgroups, particularly when stratified by both CRP levels and MRI findings, which reduced the statistical power to reliably generalize findings across the broader r-axSpA population. Additionally, as a post hoc analysis, the study was subject to inherent constraints, including potential selection biases and limited ability to control for confounding variables.





Comments (0)