Various authors have proposed techniques combining synthetic mesh with autologous tissue, categorized under terms such as “bridge repair,” “mesh sandwich,” or “peritoneal flap hernioplasty.” However, with the exception of Malik et al. [9], few have adhered to the foundational principles of the Lázaro da Silva procedure, particularly regarding the initial surgical approach and tissue preservation.
A significant precursor in the Brazilian literature is the 1995 study by Pitrez [5], which proposed an “autoplasty with the hernial sac combined with anterior relaxing incisions and polypropylene mesh reinforcement” for defects exceeding 10 cm. Pitrez’s method involved a longitudinal opening of the hernial sac to create two flaps, bilateral relaxing incisions in the anterior rectus sheath, and the use of the sac flaps to line the defect without primary approximation. This was followed by an onlay polypropylene mesh reinforcement. In his series of 28 patients, Pitrez demonstrated that avoiding the approximation of the rectus muscles protected patients from the systemic consequences of IAH, while the doubly lined hernial sac provided a stable “containing diastasis” without recurrence during follow-up.
A key anatomical distinction separates the mALS from the peritoneal flap hernioplasty (PFH) as described by Malik et al. [9] and subsequently by Nielsen et al. [10]. In the PFH, the peritoneal flaps are created primarily from the parietal peritoneum and used to cover a large retromuscular mesh extending from linea semilunaris to linea semilunaris. In the mALS, by contrast, the flaps are derived from the hernial sac itself (peritoneofibrous tissue), and the mesh, sized to bridge the parietal defect rather than to span the full retromuscular space, occupies an asymmetric position: retromuscular/retrorectally on the side of the posterior relaxing incision and anteromuscular/antero-rectally on the contralateral side. This configuration may reduce the extent of dissection required and may preserve the retromuscular space for future access, while still providing mesh isolation from both the viscera and the subcutaneous tissue. Additionally, the mALS derives its conceptual framework from the three-plane reconstruction of the original Lázaro da Silva procedure, which is not replicated in standard PFH techniques.
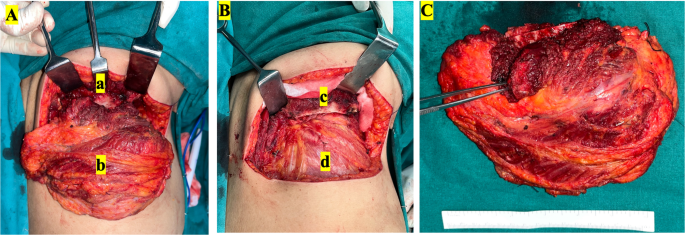
Similarly, our proposed technique combines the Lázaro da Silva procedure with synthetic prosthesis coverage. In the case presented, the dissection of the hernial sac flaps was fully executed; however, primary reconstruction was deemed unwise due to the imminent risk of IAH and abdominal compartment syndrome. By replacing the intermediate (second) suture plane with a bridge mesh, we maintained a planned separation of the rectus muscles, effectively expanding the abdominal cavity.
A critical advantage of this modification is that the mesh remains encapsulated by the connective-mesothelial sheets of the hernial sac. This “envelope” protects the viscera and subcutaneous tissue from mesh-related complications—such as adhesions, erosions, or infections—while inducing a robust cicatricial response that contributes to long-term parietal stability [9]. Furthermore, this approach allows for concomitant dermolipectomy without compromising the repair.
It is imperative to highlight that the decision to implement this modification was made intraoperatively. It represents a circumstantial adaptation necessitated by the disproportion between the visceral volume and the original abdominal capacity. Even when preoperative measures like PPP or BTA are attempted, they may prove insufficient [11,12,13]. Emerging adjuncts such IFT devices (still not available in some countries), which applies progressive lateral traction to facilitate midline approximation without increasing intra-abdominal pressure, may further expand the preoperative armamentarium and reduce the need for bail-out maneuvers [14]. The experienced surgeon must recognize the risk of a sudden rise in intra-abdominal pressure during parietal synthesis. Consequently, continuous monitoring of cardioventilatory parameters and intra-abdominal pressure by the anesthesia team is mandatory.
In the original Lázaro da Silva procedure, the second suture plane reconstitutes the linea alba. In our variant, this plane is replaced by a planned, mesh-reinforced diastasis. This tactical alternative is supported by the favorable outcomes seen in Pitrez’s series and our own preliminary results. While no single technique is universally applicable, this modification offers a “bail-out” strategy for complex cases, allowing for a stable repair in a normotensive cavity. We hope this report encourages further evaluation of this variant by surgeons managing complex abdominal wall hernias.







Comments (0)