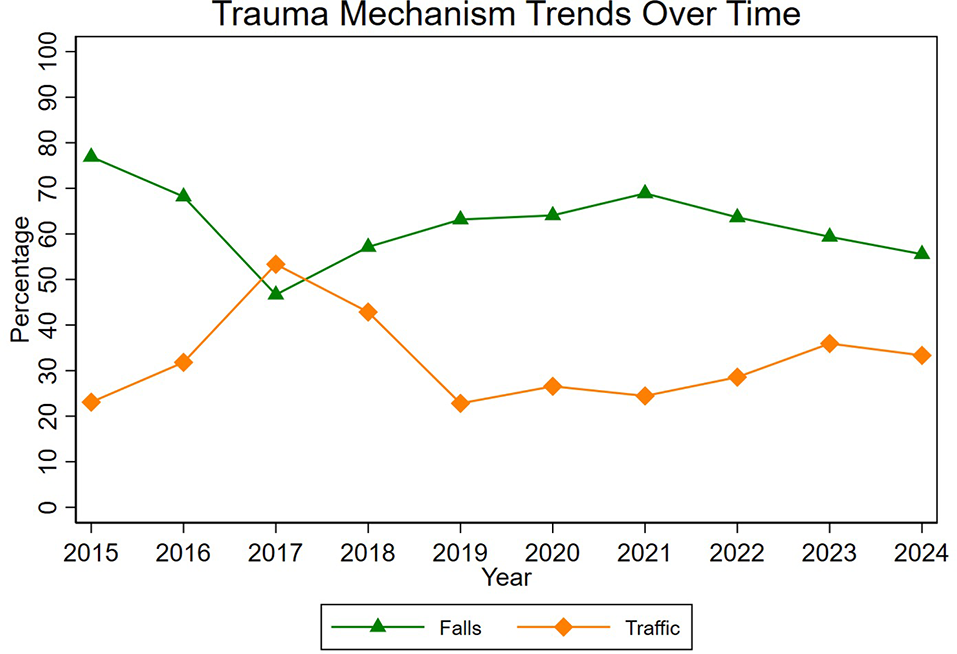
We assessed national demographics of SCI in the context of severe trauma in Switzerland from 2015 to 2024. Our study shows that 1.6% (n = 383) of all severely injured patients in Switzerland sustain concomitant SCIs, with an overall estimated incidence of 0.44 cases per 100’000 inhabitants. Over the past decade, there has been a significant increase in male patients who comprise 73.6% of our study population. Falls (63.1%) and road traffic accidents (29.6%) remain the two leading trauma mechanisms with their proportions remaining relatively stable over the past decade. The majority of SCI cases (67.3%) occur in patients with multiple injuries rather than as isolated spinal injuries. Additionally, one in four patients sustained injuries in more than one spinal region (i.e., cervical, thoracic, lumbar, or sacral) while the cervical spinal cord was the most commonly affected injury level (61.3%) followed by the thoracic spinal cord (28.3%).
Our findings on SCI rates in severely injured patients align with those of Burney et al., who reported 2.6% of patients in the United States Major Trauma Outcome Study (MTOS) were diagnosed with a SCI [4]. Despite limited research on this patient population since the early 1990s, interest in this topic has recently grown within the EANS and the WSES who established consensus-based recommendations [13]. Although the incidence remains low, the consequences of sustaining a SCI can be devastating, particularly in the setting of severe trauma, as the prioritization of other organ systems in accordance with the established ATLS protocols may inevitably lead to delays in targeted SCI care [12]. Currently available guidelines primarily focus on early surgical decompression within 24 h of injury and blood pressure augmentation, aiming for mean arterial pressure (MAP)-targeted management to optimize spinal cord perfusion to improve neurologic outcomes [10, 17]. However, in patients with associated polytrauma, timely decisions regarding early surgery or MAP-targeted therapy remain particularly challenging. This is due to competing priorities, such as the need to manage life-threatening hemorrhages or uncontrolled bleeding, where lower MAP values may need to be tolerated as part of damage control resuscitation [18]. Furthermore, the accurate recognition of SCI can be hindered by concurrent injuries that complicate neurologic assessment, such as altered consciousness due to TBI, intubation or injuries of the extremities. Our study demonstrates, that 17.4% of patients have associated moderate to severe TBI and 67.3% present with multisystem injuries. A better understanding of the demographics of SCI patients in the context of severe trauma will aid in identifying key factors that require special attention during acute management and help optimize resource allocation.
While the distribution of injury levels aligns with previous reports on SCI in polytrauma patients [4], underlying injury patterns significantly differed between cervical and thoracic SCIs (p < 0.001) and cervical and lumbar SCIs (p = 0.005). Notably, cervical SCIs were more frequently associated with neither fractures nor dislocation-type injuries. While this has not been reported before in the context of polytrauma, it is consistent with observations in the overall SCI population [19,20,21]. Age-related degenerative changes of the cervical spine resulting in spinal stenosis are becoming increasingly prevalent, which are known to predispose to SCIs in the setting of trauma. Although the mean age of our patient cohort did not significantly increase over the past decade, it remains higher than in previously published studies [2, 4, 9], which may be a reflection of the age demographics of Switzerland [16]. As a result of the ageing demographic, traumatic SCIs without evidence of spinal column injuries, have become a focus of ongoing research, as SCIs in the elderly population have emerged as a growing global health concern [3, 22].
Despite the challenges in acute care of severely injured patients with SCIs, the majority of patients (78.4%) still received surgery within 24 h of injury. This is in contrast with previous studies, which report early surgery rates within 24 h ranging between 12.1% and 59% in their cohorts [15, 21,22,23,24]. Only one study reports comparable early surgery rates of 85.4% in their cohort of 96 motor complete SCI patients [25]. The reasons for the high rate of early surgery in our cohort need to be determined. However, Switzerland’s nationwide network of twelve level I trauma centers ensures rapid access to acute medical care with short transport distances between the trauma scene and the treating hospital. This is further supported by a well-established helicopter medical service which can significantly shorten rescue times and improve outcomes of severely injured patients [26]. Nevertheless, achieving early surgery remains a global challenge, particularly in LMICs, where logistic barriers - such as limited economic resources, medical equipment, operating room access and trained personnel - pose significant challenges [11, 27, 28].
Late surgery was more common in patients with moderate to severe TBI. A recent study of 14’964 patients with surgically managed traumatic SCIs, including 4’610 with concomitant TBI, found that TBI was independently associated with surgical delays in traumatic SCI patients (OR 1.3, 95% CI 1.1–1.6). Whether these delays are solely due to prioritization of acute TBI care or partially result from missed diagnoses due to altered consciousness remains to be investigated.
Timely recognition and referral of patients to spine surgeons remain challenging, particularly in mild forms of SCI, or in patients without radiographic evidence of fractures or dislocations [21]. Our findings indicate that patients who underwent late surgery were more likely to have incomplete SCIs and more likely to show no fractures or dislocations on initial polytrauma CT, despite similar ISS and number of affected systems across groups. This raises concerns about delayed diagnosis in patients with mild SCI and no signs of injury on imaging, a challenge further exacerbated by the complexities of managing multisystem trauma. These findings underscore the need for stronger evidence to educate clinicians and facilitate effective knowledge transfer regarding the role and timing of surgery. Given the importance of adequately assessing neurological impairment and the limitations of the ASIA scoring system in mild SCI, the ongoing AO Spine-sponsored IN-TWIN-study (Traumatic Incomplete Tetraplegia without Instability, NCT 05653206) aims to evaluate the feasibility of implementing additional and complementary outcome measures for cervical SCI patients with incomplete tetraplegia and no spinal instability [29].
The overall acute care hospital mortality rate in our study population was 4.8%, aligning with previous studies that report mortality rates ranging from 2 to 6.6% [2, 30]. Interestingly, Burney et al., whose study cohort also included SCI patients in the setting of severe trauma, reported a significantly higher mortality rate of 17% [4]. The substantially lower mortality in our cohort may reflect continued advancements in prehospital care and trauma center management for patients with acute SCI over the past 30 years.
Overall, complications occurred in 55.5% of patients, with pneumonia being the most common (14.7%). When further stratified by timing of surgery and adjusted for confounding variables, patients in the late surgery group had significantly higher rates of two and more complications and significantly higher rates of UTIs and multiorgan failure. Previous studies examining the impact of timing of early vs. late surgery using a 24-hour threshold have reported complications inconsistently and often without clear specification [15]. However, there is general consensus that early surgical stabilization improves non-neurological outcomes, such as hospital LOS, ICU duration, and rates of pneumonia and other complications, likely by promoting early mobilization and reducing immobility-associated risks [5, 31,32,33]. While establishing causality is challenging due to the observational nature of our analysis, our findings align with previous studies demonstrating that early surgery is associated with significantly shorter hospital stay, reinforcing the role of early surgery to improve non-neurological outcomes.
Strengths and limitations
The strength of the study lies in its minimal missing data burden. In accordance with Swiss law, the STR has been mandatory since January 1st, 2015 across all twelve hospitals authorized to treat patients with severe injuries. This comprehensive nationwide implementation enables an accurate representation of the demographic data for the SCI population among severely injured patients.
Due to the observational nature of this study, establishing causal relationships remains challenging because of the inherent limitations of a non-randomized study design and the potential of introducing a systematic bias for more severe injuries to undergo late surgery. On the other hand, the registry-based approach allows for the inclusion of patients in a consecutive manner and, therefore, more closely reflects real-world conditions whereas an RCT may need to rely on narrow inclusion criteria and a controlled setting. Furthermore, patients with isolated SCIs, such as cord contusions without associated spinal column damage, may not meet the inclusion criteria of the STR. As a result, the dataset captures individuals with SCIs occurring in the context of severe trauma, defined by an ISS ≥ 16 and/or an AIS head score ≥ 3, and therefore does not represent the full spectrum of SCI cases. This focus on severely injured patients may partially account for the rapid assessment and treatment observed in the cohort. Finally, we were unable to address specific questions regarding neurologic outcomes in this study because the data source provided no data in this regard. Given that a large proportion of patients with SCIs are referred to one of the four nationwide paraplegia rehabilitation centers, future research could combine data from the STR with outcome registries such as the European Multicenter Study about Spinal Cord Injury (EMSCI) to explore the impact of acute SCI care on long-term neurological outcomes.

Comments (0)