
Remember me
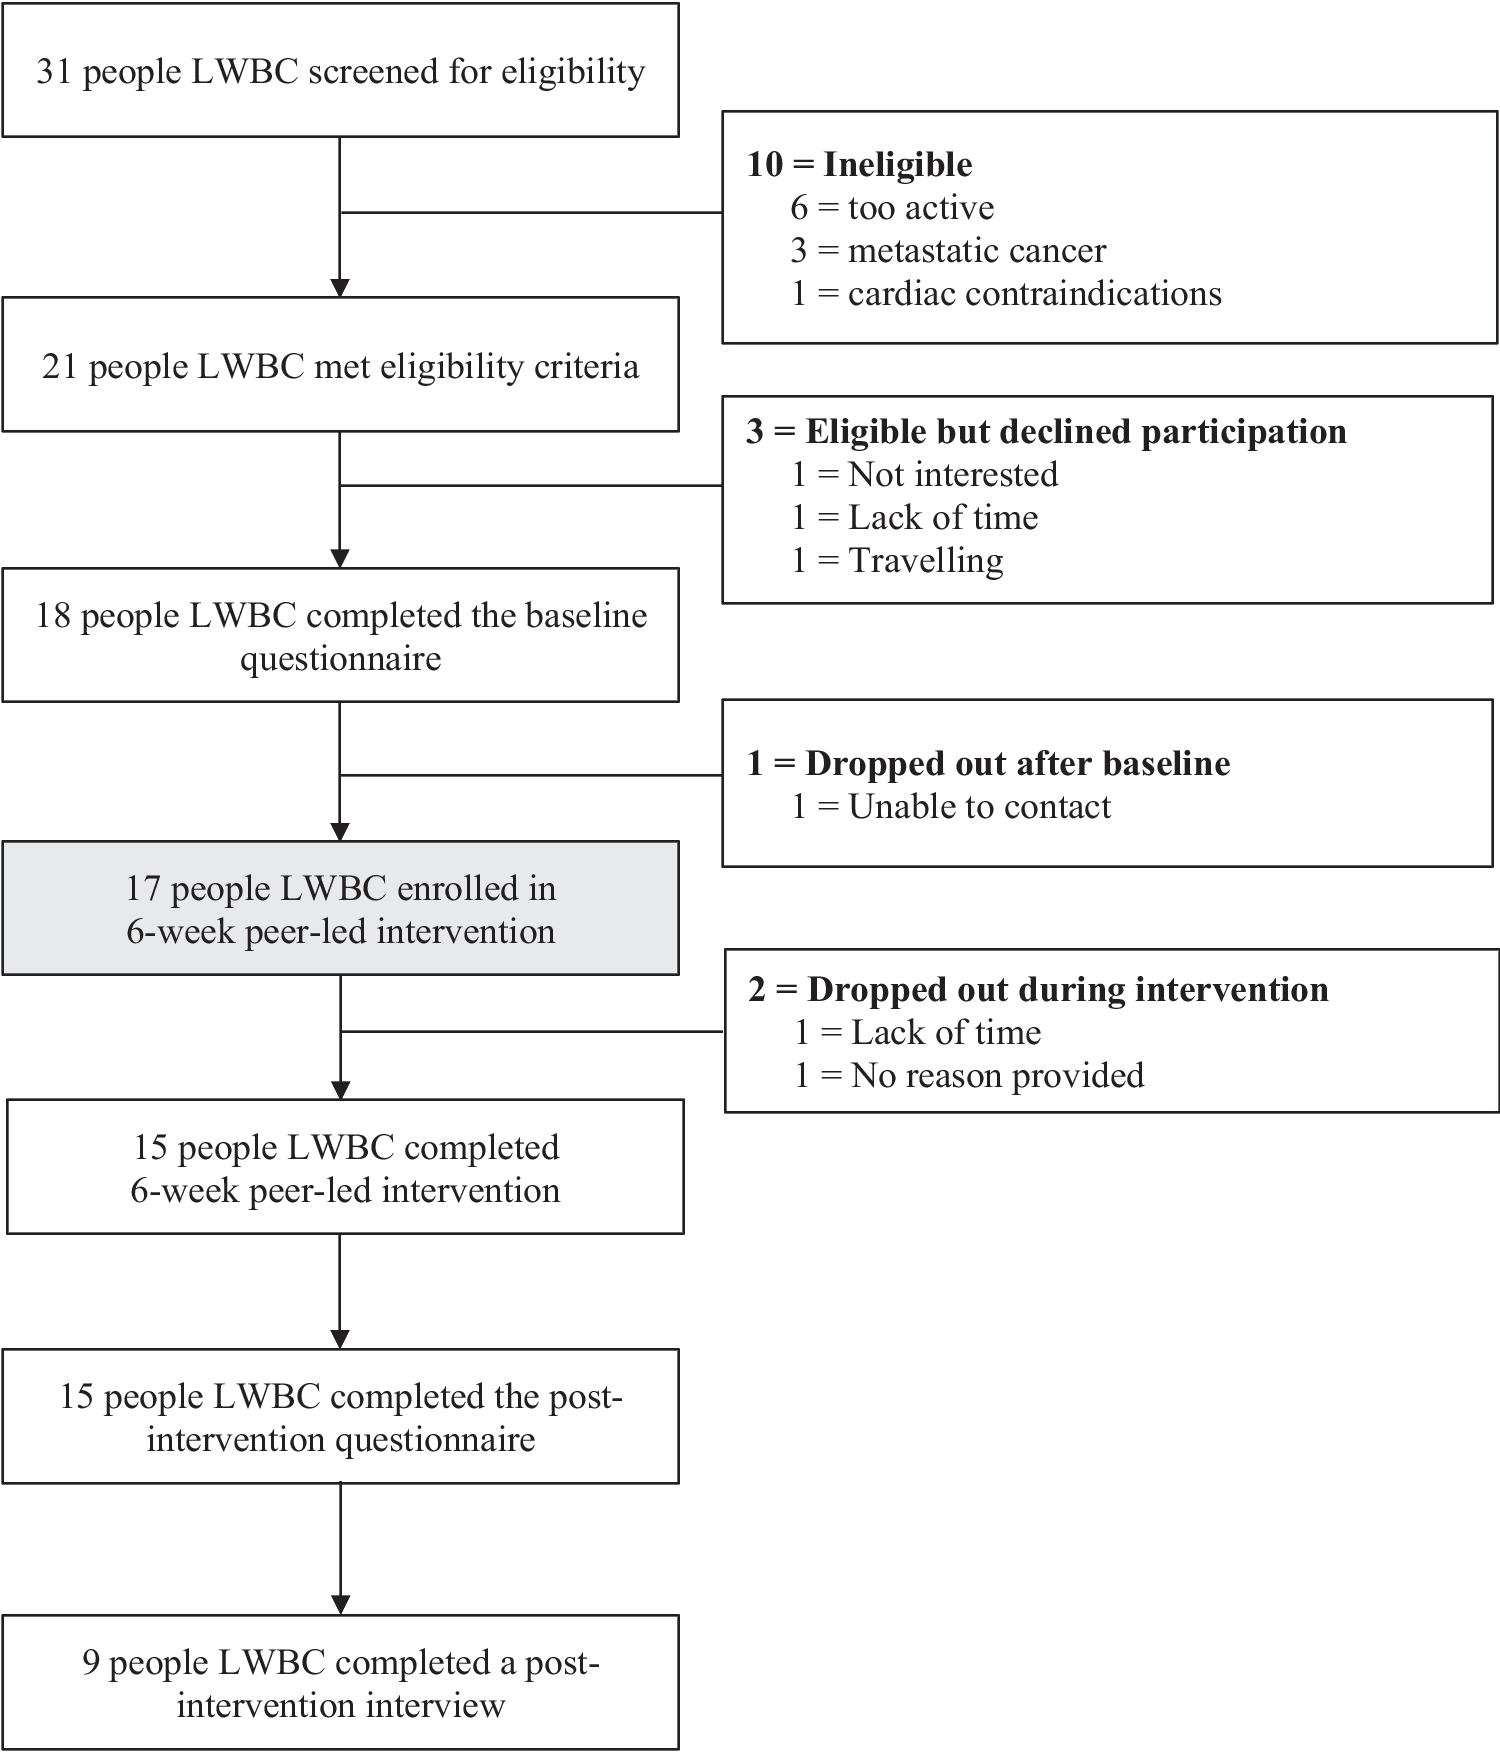
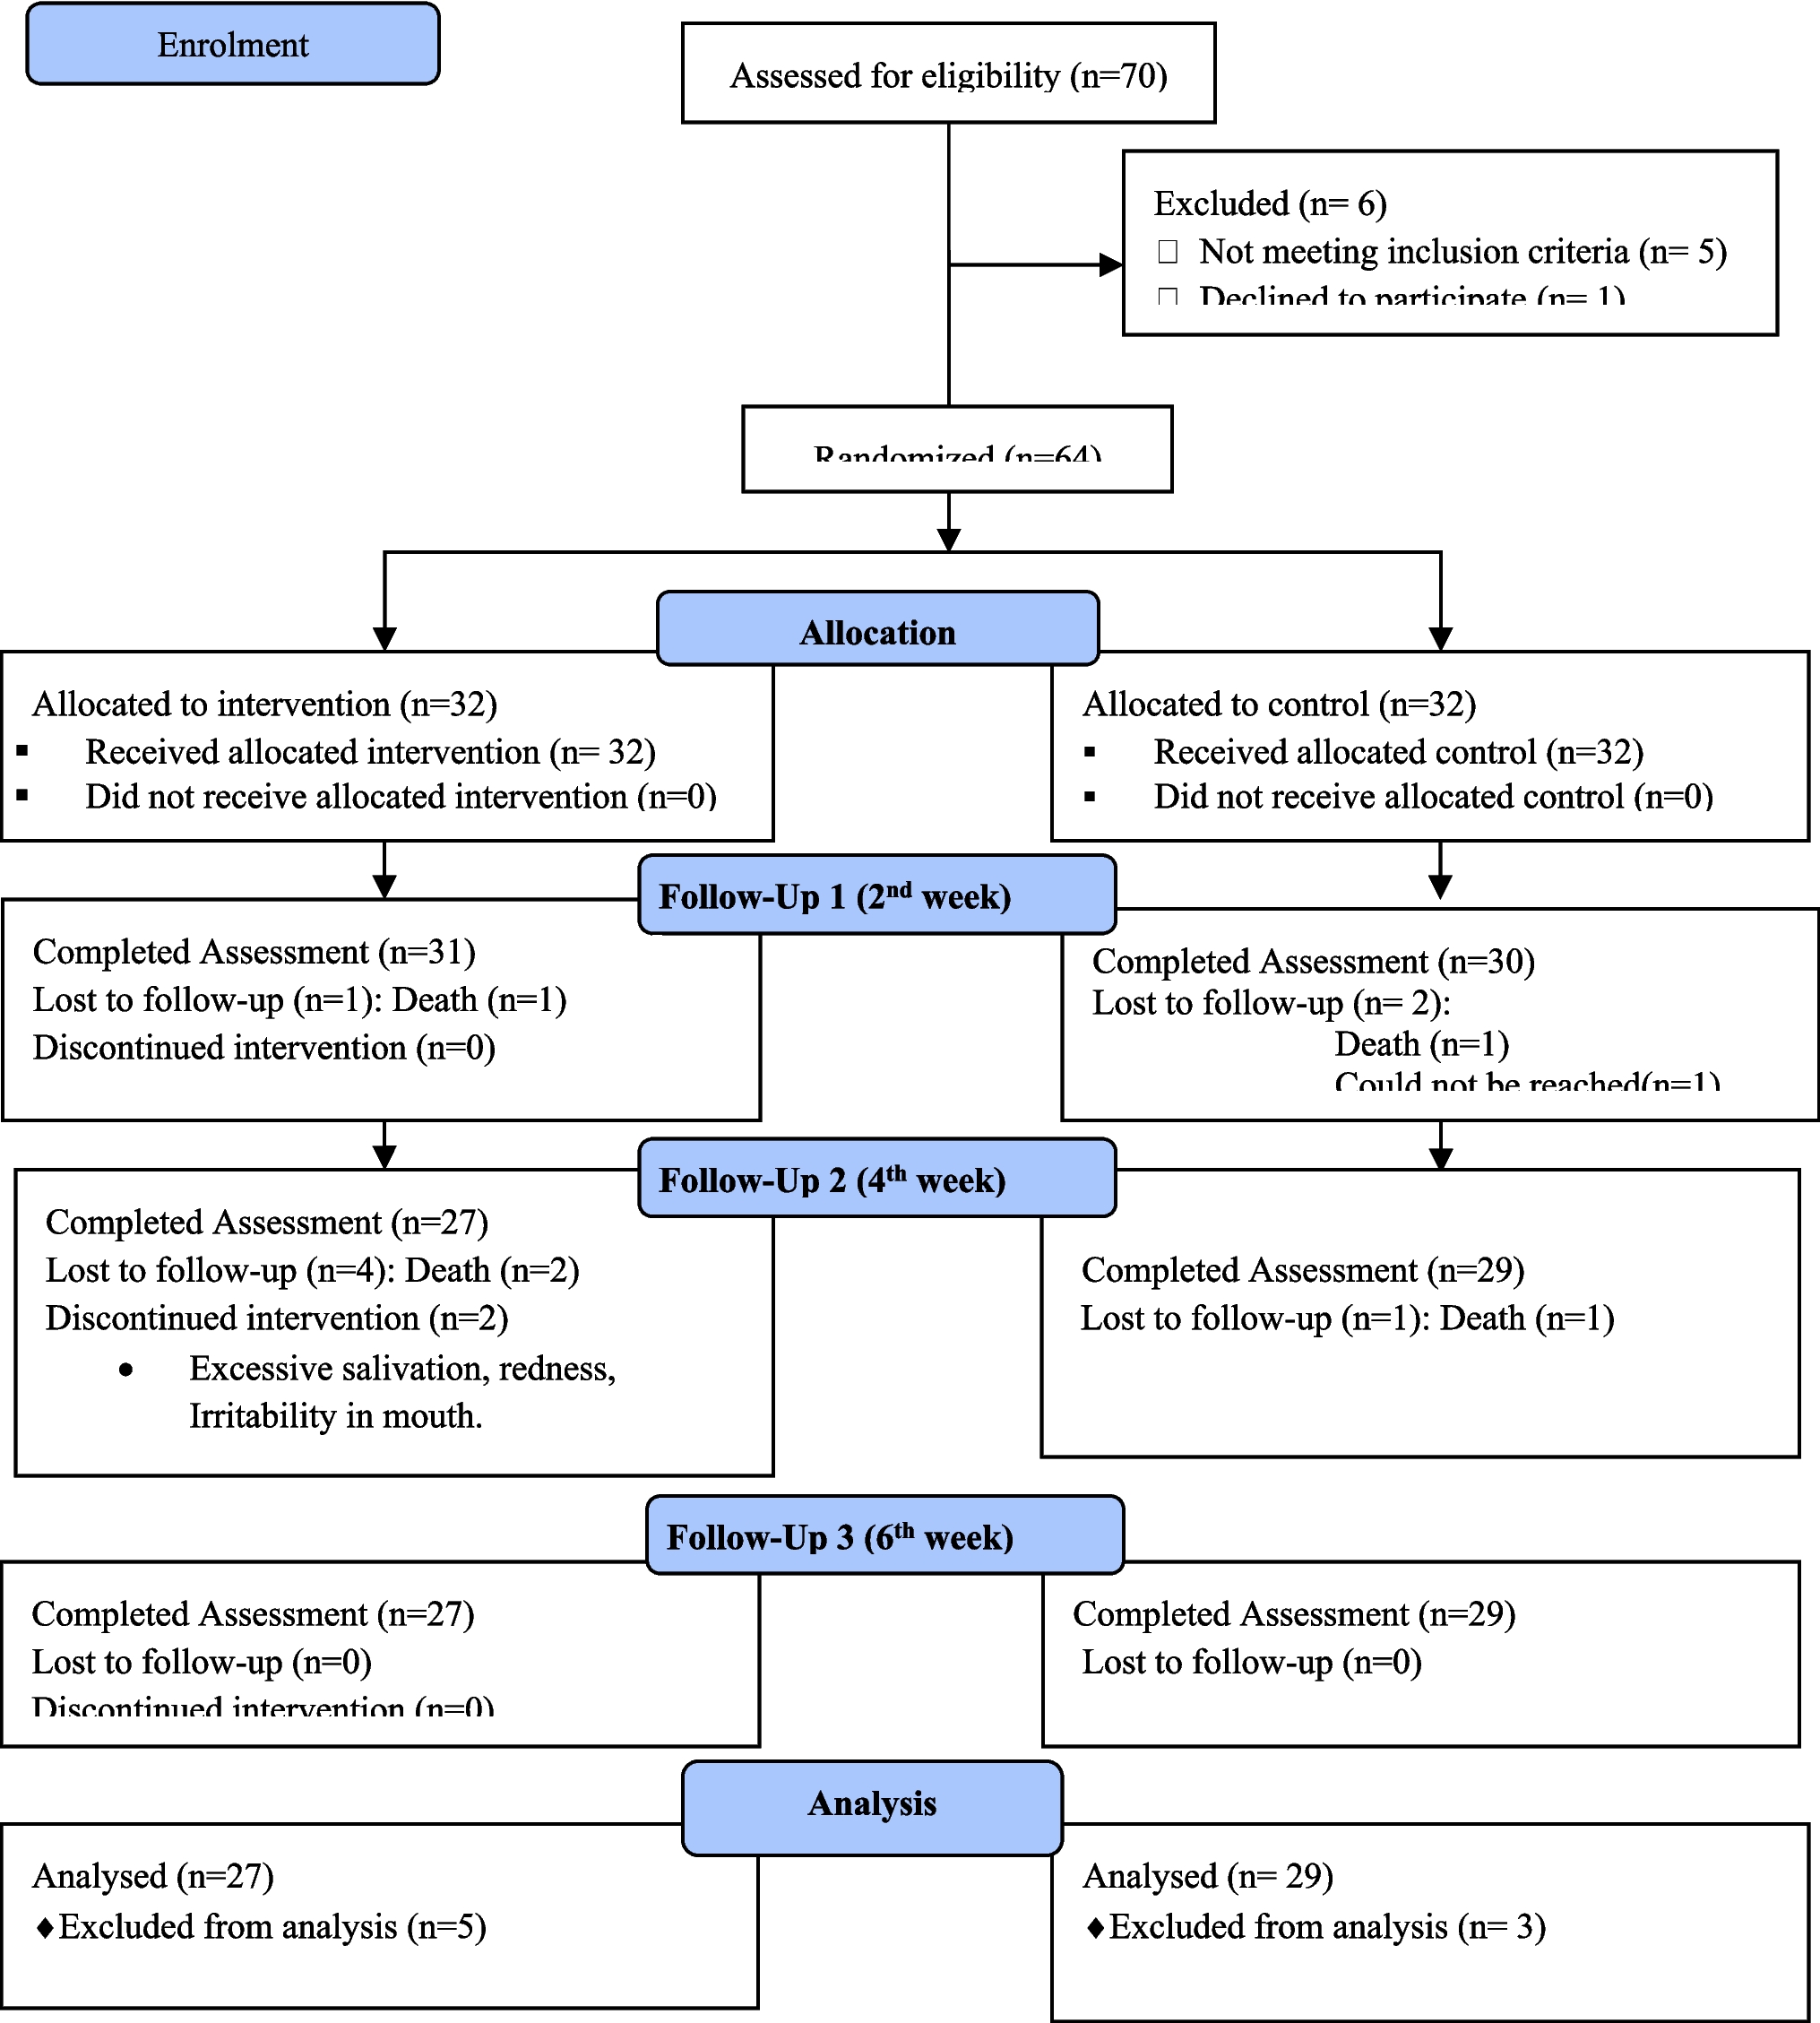

The process of study retrieval is reported in the PRISMA 2020 flow diagram (Fig. 2) [29]. 816 studies were identified, 394 abstracts were screened, and 49 papers retrieved for full text screening. Of those full text papers, nine studies were eligible for the review of which eight were undertaken in the UK [23, 36,37,38,39,40,41,42] and one study was undertaken in Australia [43]. Four tools to address HNAs in cancer were identified [23, 36,37,38,39,40,41,42,43] of which one study was specifically aimed for brain tumour patients [40]. Characteristics of the included studies are presented in Table 2 comprising an overview of the following: identified HNAs; study design location and aims; cancer types and participants; HNA format and purpose.
Fig. 2 Table 2 Study and HNA characteristicsQuality of studies
Quality assessment was conducted on all studies using the Specialist Unit for Review Evidence (SURE) [34] critical appraisal checklist (see Table 3) with varying quality. One study reported on a randomised controlled trial focusing on specific cancers across two clinics within a specialist cancer centre and two clinics located in general hospitals [23]. The remaining studies comprised a range of study designs. Three studies were cross-sectional in design [38, 40, 42], all of which did not meet all quality requirements. Three studies adopted a qualitative approach through semi-structured interviews of which two met the requirements to be classified as high quality [36, 37] and the third which was a sub-study from an interrupted time series study, comprising audio-taped consultations, did not meet the requirements of being of high quality [43]. The other studies were based on a controlled observational retrospective cohort study [41], and a quality improvement project focused on the implementation of the HNA using the Adversity, Restoration, Compatibility (ARC) framework rather than the HNA tool itself [39]; neither study met full requirements to being of high quality.
Table 3 Quality assessment of the included studiesTools to identify HNAs in cancerTable 4 outlines the results of the study outcomes relating to the implementation of the HNA tools.
Table 4 Study outcomes relating to implementationTwo studies used the Liverpool PCI, which provides patients the opportunity to complete a tick list of potential needs and areas that patients would like to discuss and/or be referred to including physical and functional well-being, treatment, social care and social well-being, psychological, emotional, and spiritual well-being [38, 40]. One of these studies included patients with head and neck cancer [38]. The other study included patients with brain cancer [40].
Five studies [23, 36, 37, 39, 41] used Macmillan’s HNA which provides a checklist that patients can identify any physical, practical, emotional, family or relationship, spiritual, and information or support needs along with any questions they may want to be addressed by their relevant clinician. Two studies [38, 39] used the eHNA in women with breast cancer. Snowden et al. [41] used the paper version of the HNA Concerns Checklist in patients with head and neck, skin, or colorectal cancer. Another study [41] also reported on the use of the HNA and the NCCN DT and Care Planning tools as part of the Improving Cancer Journeys (ICJ) services in patients with bowel, breast, lung, prostate, and ‘other’ cancer. In addition to this, the Macmillan HNA was used to underpin the implemented ARC clinic, as part of a quality improvement project for patients with treatable but not curable cancer (metastatic breast, lung, colorectal myeloma); patients 6–24 months postdiagnosis were eligible [39].
One study used a one-page Palliative Care Needs Assessment Tool (PC-NAT) in patients with advanced cancer (including breast, bowel, myeloma, lymphoma, melanoma, leukaemia, gynaecological, prostate, stomach and bladder cancers) [45]. One study used the SPARC questionnaire in patients with thoracic cancer [42].
Table 4 provides details on the outcomes focusing on implementation of the HNAs, patients’ needs and concerns, and patient participation and shared decision-making.
Implementation and impact of HNAs in cancerAcceptabilityAcceptability was the most common implementation outcome category used in the included studies [36,37,38,39,40, 42]. The range of outcomes relating to the acceptability of the HNA tools varied, including patient and staff satisfaction [36, 39, 40], participation and completion of the tool [39, 41, 42] as well as the acceptability of the format [38].
FeasibilityFive studies reported on assessing the feasibility of the HNAs [23, 38, 39, 41, 43]. One study looked at the number of new onward referrals from using the PCI and reported there to be no change [38]. Another study reported an increase in completion of the care plans from 13 to 90% after use of the ARC HNA [39]. Two studies [41, 43] reported on the length of the consultations; one study reported no significant difference in the mean length of the PC-NAT consultations (18.1 min) and the baseline consultations (19.5 min) [41], whereas another study reported an increase in the duration of the consultations using the HNA; consultation times were on average nearly 2 min longer for the intervention group (17 min 25 s) than control group (15 min 39 s) [23].
One study reporting on the use of healthcare services including calls to NHS24 (Scotland’s national telehealth and telecare service, providing a telephone advice and triage service), access to the Accident and Emergency (A&E) department, attendance to hospital, unscheduled care pathways and prescriptions for psychotropic drugs for both the Improving Cancer Journeys (ICJ) group [41]. Overall, it reported an increase from baseline through the study period for all groups; however, there was a greater use of the healthcare services by participants in the ICJ group [41]. There was a statistically significant increase in the number of NHS24 calls when comparing it with the Glasgow group d = 0.39, p = 0.0016) and a non-statistically significant increase when comparing with the Rest of Scotland (d = 0.01, p = 0.84) [41]. There was a statistically significant increase in attendance to A&E when comparing to the Glasgow (d = 0.19, p < 0.0001) and Rest of Scotland groups (d = 0.11, p = 0.0013) [41]. There was also a statistically significant increase in the number of hours spent in A&E when comparing to the Glasgow (d = 1.38, p < 0.0001) and Rest of Scotland groups (d = 1.28, p = < 0.0001) [41]. There was a statistically significant increase in the number of admissions to, and days spent in the hospital when comparing with the Glasgow (admissions: d = 1.66, p < 0.0001; days in hospital: d = 3.68, p < 0.0001) and the Rest of Scotland groups (admissions: d = 3.68, p < 0.0001; days in hospital: d = 3.41, p < 0.0001) [41]. There was a statistically significant increase in the number and complexity of care pathways (number of steps) when comparing with the Glasgow (number of pathways: d = 0.38, p < 0.0001; complexity of care pathway: d = 0.9, p < 0.0001) and the Rest of Scotland groups (number of pathways: d = 0.19, p = 0.041; complexity of care pathways: d = 0.65, p < 0.0001) [43]. There was a non-statistically significant increase in the number of psychotropic drug prescriptions and cost of prescriptions when comparing with the Glasgow group (number of prescriptions: d = 0.32, p = 0.21; cost of prescriptions: d = −0.061, p = 0.99) [43]. There was a statistically significant increase when comparing this with the Rest of Scotland group (d = 0.67, p = 0.0075) and a non-statistically significant increase in cost of prescriptions (d = −0.061, p = 0.99) [43].
Fidelity and adoptionOther outcomes reported on included fidelity [37, 43] and adoption [37]. Fidelity can be defined as ‘the degree to which an intervention was implemented as it was prescribed in the original protocol or as was intended by programme developers’ [13]. One study reported on the mode of the PC-NAT administration; oncologists most often administered the PC-NAT in the final third of the consultation, integrating it into the discussion with little preamble regarding its purpose or significance [43]. Analysis of the consultations revealed that most interactions between the clinician and patient related to medical and treatment issues, regardless of whether the PC-NAT was used or not; there was little to no discussion of broader psychosocial concerns [43]. There was no significant difference in the mean length of the PC-NAT consultations (18.1 min, range = 3.5–53.51) and the baseline consultations (19.5 min, range = 9.5–24.1) [43].
One study found that many staff indicated uncertainty around the ‘correct’ way to conduct an eHNA or how to address concerns when no clear solution was available [37]. Views varied toward the benefits and burdens of the assessment and its implementation, but the existence of target eHNA completion metrics presented pressure and ‘feelings of obligation’, which affected quality of assessments for some staff [37]. Lastly, organisational hierarchy or culture within staff structures appeared to influence how successfully the eHNA was implemented, with some staff being resistant to change [37]. Participants’ perceptions of the eHNA appeared contingent on the organisational structure and processes within which it was situated [37]. How the organisation approached eHNA implementation seemed connected to staff views toward it. This included whether an emphasis was placed on achieving targets around eHNA completion and the engagement and support from senior leadership [37].
Identified needs/concernsSeven studies reported needs and concerns identified by patients and/or carers [38,39,40,41,
Comments (0)