Characteristics of total cohort
Detailed characteristics of the patient cohort and the various subgroups—liver transplant, kidney transplant, heart transplant, and lung transplant recipients—are shown in Table 1.
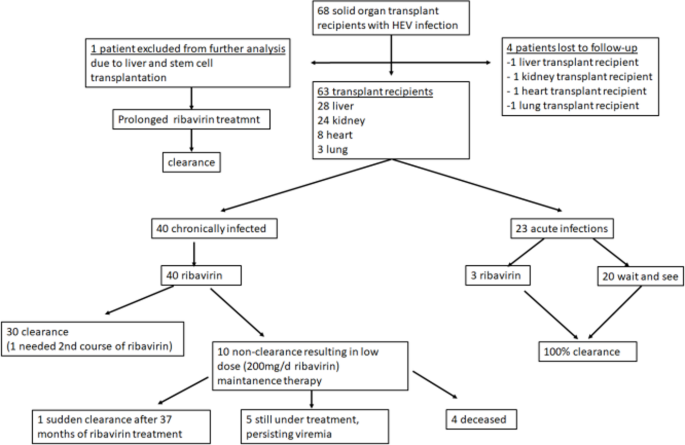
Between June 2011 and June 2025, a total of 68 solid organ transplant (SOT) recipients were diagnosed with hepatitis E virus (HEV) infection. Five patients were excluded from further analysis: one liver transplant recipient had previously undergone stem cell transplantation and therefore had a significant different level of immunosuppression compared to the rest of the liver transplant group. Four additional patients were lost to follow-up. These individuals were from other cities—or, in one case, another country—and no follow-up data were available after their initial HEV diagnosis.
A total of 63 SOT recipients (67% male; average age 53 years, range 20–83) with PCR-confirmed HEV infection were included in the analysis. Of these, 40 patients (63%) met the criteria for chronic HEV infection.
Excluding the liver and stem cell transplant recipients and the four patients lost to follow-up, 52 of 63 patients (83%) cleared the infection either spontaneously or after uncomplicated ribavirin therapy. This included 47 of 52 abdominal organ transplant recipients (90%) and 6 of 11 thoracic organ transplant recipients (55%) (p = 0.02).
Additionally, one heart transplant recipient achieved viral clearance after a second course of ribavirin, and 10 patients could not clear the infection despite extended ribavirin therapy. These patients were treated with low-dose maintenance ribavirin therapy (200 mg daily). Among them, one kidney transplant recipient cleared the infection while on maintenance therapy. Four patients died during treatment, and the remaining five are still receiving 200 mg of ribavirin daily at the time of analysis.
The proportion of patients with chronic infection was lower among recipients of abdominal organs (liver or kidney) at 58% (30/52) compared to thoracic organ recipients (heart or lung) at 91% (10/11). However, this difference was only borderline statistically significant (p = 0.047, Chi-square test). In contrast, the rate of sustained virological response (SVR) was significantly higher in abdominal organ recipients (90%, 47/52) than in thoracic organ recipients (55%, 6/11; p = 0.02). Neither viral load in blood or stool nor ALT levels differed significantly between abdominal and thoracic organ recipients (Mann–Whitney test).
Characteristics of HEV infected transplant recipients in comparison to the total cohort of transplant recipients at our center
To compare the distribution of sex and transplanted organs in the HEV-infected group with that of the overall transplant population at the University Medical Center Hamburg-Eppendorf, all solid organ transplant recipients from the past 10 years were included as controls (n = 1,855). There were no significant differences between the HEV-infected group (n = 67) and the total transplant group (n = 1,855) in terms of sex distribution (67% male [45/67] vs. 60% male [1,109/1,855], p = not significant) or the distribution of transplanted organs: liver (43% [29/67] vs. 41% [752/1,855]), kidney (37% [25/67] vs. 43% [793/1,855]), heart (13% [9/67] vs. 11% [200/1,855]), and lung (6% [4/67] vs. 6% [110/1,855]) (all p = not significant).
Evidence of extrahepatic manifestations of HEV in transplant recipients?
In four patients, evidence of extrahepatic manifestations could be observed (Table 1). Three patients suffered from arthralgia, and one patient (a 51-year-old heart transplant recipient) developed neuralgic amyotrophy, a well-known neurological manifestation of HEV infections. Interestingly, this episode occurred despite ongoing ribavirin therapy. This patient has been described previously in a publication [26]. At the time of his neurological symptoms, he had no detectable viral load in his blood but still had a detectable viral load in his ejaculate. Low HEV positivity (< 24 IU/ml) was detected in his cerebrospinal fluid.
Serological status
A total of 59 patients were tested for anti-HEV IgG and IgM antibodies. Of these, 36 (61%) tested positive for both anti-HEV IgG and IgM. No patients tested positive for only IgG or only IgM. Among the 36 seropositive patients, 72% were male (26/36).
Regarding infection status, 67% of seropositive patients (n = 24) had a chronic HEV infection, 28% (n = 10) had an acute infection, and 6% (n = 2) were lost to follow-up. Among seropositive individuals, 72% (n = 26) achieved sustained virological response (SVR), 22% (n = 8) remained chronically infected, and 6% (n = 2) were lost to follow-up. Notably, all three deaths in the cohort occurred among seropositive patients.
The average age of seropositive patients was 54 years (range 20–82, SD 16). The average viral load was 15,825,860 IU/ml (range 72–240,000,000 IU/ml, SD 45,879,188), and the average ALT level was 351 U/ml (range 15–3,032 U/ml, SD 531).
There were no significant differences between seropositive and seronegative patients in terms of sex distribution or infection chronicity (Chi-square test, p = not significant). Surprisingly, seropositive patients achieved SVR significantly less often than seronegative patients (26/36 vs. 22/22, p < 0.001). No significant differences were observed between the groups regarding age (p = 0.09), viral load (p = 0.39), or ALT levels (p = 0.14).
Ribavirin treatment
Ribavirin therapy was initiated in 43 patients (64%). Of these, 40 had chronic HEV infection, while in three patients, ribavirin was started before their viremia lasted more than three months, based on their doctors’ decisions. Consequently, these three patients did not meet the criteria for a chronic infection and were excluded from further analysis related to ribavirin treatment.
Of the 40 patients with chronic infection who received ribavirin, 31 (78%) cleared the virus, while HEV persisted in nine patients (22%). Patient details for the chronically infected individuals treated with ribavirin are listed in Table 2. All nine patients who did not achieve viral clearance despite re-treatment and/or extended low-dose ribavirin therapy (200 mg daily) remained clinically stable, and none died from direct complications of cirrhosis. However, two of the patients who died had cirrhosis, and the connection between their deaths and cirrhosis remains uncertain; cirrhosis may have contributed to worsening their conditions.
Interestingly, among patients with chronic infection who achieved sustained virological response (SVR) without requiring maintenance ribavirin therapy (n = 30), 52% tested positive for both anti-HEV IgG and IgM at diagnosis. Conversely, among patients who did not clear the infection despite 6 months of ribavirin treatment (n = 10), all 9 available serum samples tested positive for both anti-HEV IgG and IgM (p = 0.01, Table 2).
In 22 out of 40 chronically HEV-infected transplant recipients (55%), the ribavirin dose was reduced. Specifically, this included 4 out of 13 liver transplant patients (31%), 11 out of 17 kidney transplant patients (65%), 5 out of 7 heart transplant patients (71%), and 2 out of 3 lung transplant patients (67%). Consequently, ribavirin dose reduction was needed in 15 of 30 abdominal organ recipients (50%) and in 7 of 10 thoracic organ recipients (70%) (p = ns).
Role of immunosuppression in HEV infection progression
In the cohort of analyzed transplant recipients (n = 63), 8 received mono-immunosuppression (13%), 30 dual immunosuppression (47%), and 25 triple immunosuppression (39%). Forty-one patients received tacrolimus (62%), 12 cyclosporine A (19%), 34 mycophenolate mofetil (or enteric-coated mycophenolate mofetil) (53%), 25 everolimus (39%), 3 azathioprine (5%), and 30 received steroids (47%). In 13 patients (20%), immunosuppression was reduced after HEV infection was detected; 12 of these developed chronic HEV infection, while 1 cleared the infection spontaneously without ribavirin. However, an analysis of the relationship between final HEV clearance and reduction of immunosuppression showed that 8 out of 12 (67%) patients with reduced immunosuppression ultimately cleared the virus, compared to 36 out of 41 (86%) in the group without reduction (p = 0.027). When analyzing only the subgroup of 40 patients who received ribavirin, it appears that 6 out of 11 (55%) in the reduced immunosuppression group cleared the infection, whereas 25 out of 29 (86%) in the group without immunosuppression reduction did so (p = 0.047). Reduction of immunosuppression was observed in 5 out of 13 liver transplant recipients (38%), 2 out of 17 kidney recipients (12%), 2 out of 7 heart transplant recipients (29%), and 2 out of 3 lung transplant recipients (67%) among the 40 patients with chronic HEV infection.
Neither the use of tacrolimus, cyclosporine A, mycophenolate mofetil, azathioprine, nor steroids was associated with a significantly increased likelihood of developing chronic infection or achieving final clearance. However, 4/25 (16%) of patients receiving everolimus cleared the infection spontaneously, compared to 20/39 (51%) of patients on regimens without everolimus (p = 0.007). Despite this, there was no significant association between everolimus use and final clearance of infection. Additionally, the SVR rate at the end of our observational study did not differ significantly (p = 0.137) between everolimus-treated patients (19/25; 76%) and those not treated with everolimus (36/39; 92%).
Deceased patients
Four patients (6%) died while still HEV viremic. All had chronic hepatitis E and did not clear the virus after five months of ribavirin therapy. Even with subsequent low-dose maintenance therapy of 200 mg ribavirin daily, the infection persisted in these patients.
The first deceased patient was a 58-year-old male kidney transplant recipient with pneumonia and sepsis. He had undergone transplantation due to polycystic organ degeneration, and his entire liver was cystic, with no signs of cirrhosis.
The second deceased patient was also a kidney transplant recipient who had liver cirrhosis (FibroScan 45 kPa, esophageal varices, and a history of ascites decompensation). The 55-year-old man had no identifiable cause for the cirrhosis other than chronic hepatitis E. He developed a severe COVID-19 infection followed by pneumonia and sepsis, which ultimately led to his death.
The third patient was a 58-year-old heart transplant recipient with cirrhosis caused solely by chronic HEV infection. Retrospective testing of stored serum samples showed that he had received plasma transfusions along with rituximab during an acute rejection episode about one year before being diagnosed with HEV infection (almost three years after his transplant). These plasma transfusions were given through plasmapheresis before routine HEV screening of blood products began in Germany in January 2020. Unfortunately, he developed bronchial carcinoma, which recurred after surgery, and he died from the cancer. The fourth patient, who had died, was stabilized on ribavirin maintenance therapy for her chronic hepatitis E but died due to prolonged failure of her lung transplant.



Comments (0)