
Remember me

Before investigating the ADN, we first confirmed that the injection of LPS successfully induced a state of systemic inflammation. The successful LPS-induction of systemic inflammation was evidenced by the significant and time-dependent change of key plasma biomarkers and physiological parameters. In detail, levels of pro-inflammatory cytokines TNF, IL-6, and IL-1β, and the anti-inflammatory cytokine IL-10, exhibited characteristic temporal profiles following LPS injection (Fig. 2A-D). During the established phase of the inflammatory response (60, 90, and 120 min post-LPS), the intra-group coefficient of variation for plasma cytokine levels ranged from 25 to 41%, which represents a level of relative variability consistent with this experimental model [6, 30]. Additionally, a significant increase in plasma nitrite/nitrate levels, which indicates elevated nitric oxide production, was observed at the later time point (Fig. 2E). This inflammatory model also produced the expected pathophysiological hallmarks in the animals. These included the development of fever (Fig. 2F), a sustained drop in arterial pressure (hypotension, Fig. 2G-I), an increased heart rate (tachycardia, Fig. 2J), and a progressive impairment of baroreflex sensitivity (Fig. 2K, L). Thus, a comparable systemic inflammatory response was established in all animals, as evidenced by the consistent changes across key immunological and physiological parameters following the LPS challenge, confirming the efficacy of the induced inflammatory state. Detailed descriptions for each parameter can be found in the supplementary information (Supplementary Results, S1).
Fig. 2
Biochemical and pathophysiological parameters analysis confirmed the LPS-induced systemic inflammation. Temporal evaluation of plasma cytokines (A-D), nitric oxide (E), body temperature (F), and hemodynamic parameters (G-L) in all groups. TNF-ɑ: Tumour Necrosis Factor-alpha (A); IL-6: Interleukin 6 (B); IL-1β: Interleukin 1β (C); IL-10: Interleukin 10 (D); MAP: mean arterial pressure (G); SAP: systolic arterial pressure (H); DAP: diastolic arterial pressure (I); HR: heart rate (J); baroreflex gain (K); BEI: baroreflex effectiveness index (L). Data are presented as mean ± standard deviation. The number of animals per group ranged as follows: Basal (n = 11–15), Saline 30 min (n = 7–14), LPS 30 min (n = 12–18), LPS 60 min (n = 9–18), LPS 90 min (n = 12–14), and LPS 120 min (n = 13–18). Please refer to Supplementary Tables S2 and S3 for detailed statistical analyses and the exact number of animals for each specific parameter. *p < 0.05 vs. Basal; #p < 0.05 vs. Saline 30 min; $p < 0.05 vs. LPS 30 min; &p < 0.05 vs. LPS 60 min; %p < 0.05 vs. LPS 90 min
Furthermore, the analysis of ADN electrical activity (Fig. 3) revealed a significant, time-dependent increase at 90 and 120 min following LPS administration when compared to the control group (Fig. 3C). Notably, this increase in nerve firing occurred while the animals were experiencing systemic hypotension (Fig. 3A, B). Note that diastolic pressure is lower 120 min after LPS, yet the diastolic ADN activity is higher (Fig. 3A, B), indicating that this response is not from the mechanosensory reflex. Additionally, this rise occurred with every pressure pulse (“phasic” activity, Fig. 3D), but even more relevant during diastole, indicating a “tonic” component (Fig. 3E). Specifically, the increase during the phasic component (systolic-phase) was evident at the 60 and 90 min time points following LPS administration, but was not observed at the 120 min time point post-LPS (Fig. 3D). On the other hand, the tonic component (diastolic-phase) exhibited an elevation at the 60, 90, and 120 min time points after LPS administration relative to the control group and the 30 min post-LPS group (Fig. 3E).
Fig. 3
Aortic depressor nerve activity increased after systemic inflammation induction. Representative traces of aortic depressor nerve (ADN) recording from a rat from Basal group (A), and from LPS 120 min group (B) – pulsatile arterial pressure (PAP, upper), nerve activity recording (middle; scale bar corresponds to 100 ms), integrated nerve activity (lower); and insets from each recording showing a single pulse of PAP (red) and the integrated ADN activity (blue) superimposed (bottom). Vertical, round dotted line indicates the end of the systolic period, delimitating the pulse in systolic (Syst) and diastolic (Diast) phases. Note that diastolic pressure is lower 120 min after LPS (highlighted by the arrows), yet the diastolic ADN activity is higher (highlighted by the green horizontal, dashed line). The black horizontal dashed line emphasizes how baseline ADN discharge increased after LPS. Quantification of the total (C), phasic (D), and tonic (E) ADN activity in all groups. The phasic component was assessed by the systolic period, while the tonic component was evaluated by the diastolic period. Data are presented as mean ± standard deviation. The number of animals per group ranged as follows: Basal (n = 8–10), Saline 30 min (n = 7–9), LPS 30 min (n = 11–17), LPS 60 min (n = 7–14), LPS 90 min (n = 9–11), and LPS 120 min (n = 10–13). Please refer to Supplementary Table S4 for detailed statistical analyses and the exact number of animals for each specific parameter. *p < 0.05 vs. Basal; #p < 0.05 vs. Saline 30 min; $p < 0.05 vs. LPS 30 min
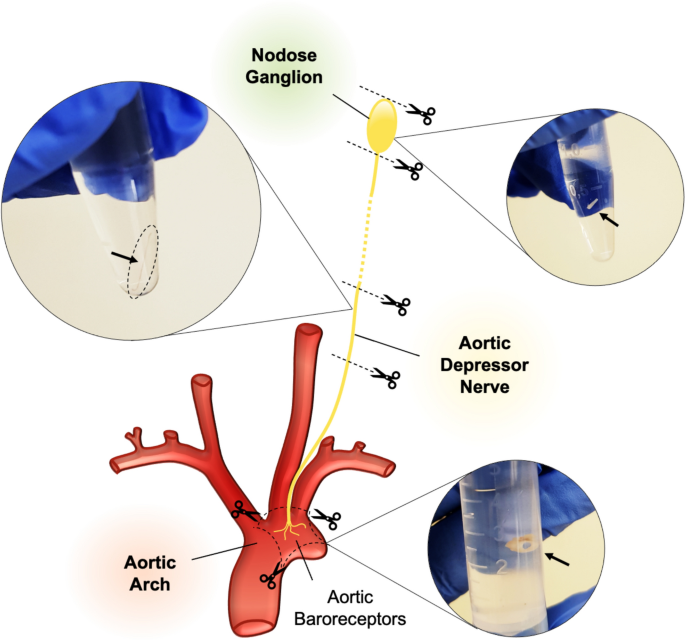
Receptors and mediators of the inflammatory response are expressed in the aortic depressor nerveTo investigate whether the arterial baroreceptors indeed possess receptors for cytokines or pathogen-associated molecules and produce inflammatory mediators, the expression of several receptors and mediators typically associated with the immune system was investigated in ADN. Remarkably, gene expression analysis revealed that the ADN expresses all evaluated immune markers: TLR4, NF-κB, MyD88, IL-6R, IL-6, IL-1R1, IL-1β, TNFR1, TNFR2, and TNF-ɑ (Fig. 4). Moreover, these findings were found even under basal conditions. Western blot analysis also detected protein expression of TLR4, IL-6, p38 MAPK, and phosphorylated NF-κB in the ADN under basal (Supplementary, Fig. S1). The basal expression of key components of the innate immune signalling pathway, including the receptor TLR4, the adaptor protein MyD88, p38 MAPK, and the transcription factor NF-κB, suggests that the ADN could participate as an immune sensor. This nerve could transduce early signs of systemic inflammation into neural signals, contributing significantly to a faster and effective response to systemic inflammatory challenges.
Fig. 4
RT-qPCR showing gene expression of inflammatory response markers in the aortic depressor nerve before and after LPS administration. Gene expression of TLR4 (A), NF-κB (B), MyD88 (C), IL-6R (D), IL-6 (E), IL-1R1 (F), IL-1β (G), TNFR1 (H), TNFR2 (I), and TNF-ɑ (J) in the aortic depressor nerve. Data are presented as mean ± standard deviation. The number of biological samples (pools—each pool consists of 4 nerves collected from 2 rats) per group ranged as follows: Basal (n = 3–6), LPS 60 min (n = 3–6), LPS 90 min (n = 5–7), and LPS 120 min (n = 4–6). Please refer to Supplementary Table S5 for detailed statistical analyses and the exact number of biological samples for each specific parameter. Red symbols indicate parameters with nominal significance (p < 0.05) that did not reach the FDR threshold but exhibited large biological effect sizes, representing relevant biological trends. *p < 0.05 vs. Basal; &p < 0.05 vs. LPS 60 min; %p < 0.05 vs. LPS 90 min
Furthermore, gene expression of NF-κB (Fig. 4B), IL-6 (Fig. 4E), IL-1R1 (Fig. 4F), and TNFR2 (Fig. 4I) increased 120 min after induction of the systemic inflammatory process with LPS administration (biological trends). Although these parameters did not reach the strict FDR threshold, they exhibited large biological effect sizes, suggesting the activation of a canonical innate immune signalling pathway within the baroreceptor afferences itself. The ADN changes from a sensor to an inflammatory tissue actively contributing to and amplifying the host immune response. Supporting these results, immunofluorescence imaging provided visual and quantitative confirmation of the constitutive expression of all evaluated immune mediators and receptors (TLR4, NF-κB, IL-6R, IL-6, IL-1R1, IL-1β, TNFR1, TNFR2, and TNF-α) in the ADN (Fig. 5 and Supplementary Fig. S6A). Moreover, 120 min after LPS administration, the immunoreactivity of IL-6R increased in the ADN compared to the Basal group, with a strong biological trend toward IL-1R1 upregulation (Supplementary Fig. S6A).
Fig. 5
Immunoreactivity to cytokines, their receptors, and the NF-κB in the aortic depressor nerve. Representative images showing the immunoreactivity of interleukin-1β (IL-1β; A), interleukin-1β receptor (IL-1R1; B), interleukin-6 (IL-6; C), interleukin-6 receptor (IL-6R; D), tumour necrosis factor receptor type 1 (TNFR1; E) and type 2 (TNFR2; F); toll-like receptor 4 (TLR4; G); tumour necrosis factor (TNF; H); nuclear factor kappa B (NF-κB; I); and the neuronal marker PGP9.5 (J) in transversal sections of the aortic depressor nerve before (Basal, upper panels) and 120 min after LPS treatment (lower panels). In the images, it is possible to see the entire circumference of the nerve, visualizing all the regions where the expression of the targets is. The expression of cytokines and their receptors in baroreceptor afferents was evidenced by immunoreactivity. Scale bars correspond to 10 μm. Magnification: 40 × with 2 × zoom. Quantitative analysis of the immunoreactivity is provided in Supplementary Fig. S6A
Inflammatory markers expression in the nodose ganglionGiven that the nodose ganglion contains the somas of the ADN's primary afferent neurons, we investigated its capacity to respond to inflammatory stimuli by assessing the expression of key immune mediators. Our initial RT-qPCR analysis confirmed that, under basal conditions, the ganglion expresses the complete molecular machinery required for an innate immune response, including the sensor TLR4, the adaptor protein MyD88, the transcription factor NF-κB, and several pro-inflammatory cytokines and their receptors (Fig. 6A-J).
Fig. 6
RT-qPCR showing gene expression of inflammatory mediators in the nodose ganglion (left, A-J) and in the aortic arch (right, K-T) before and after LPS administration. Gene expression of TLR4 (A), NF-κB (B), MyD88 (C), IL-6R (D), IL-6 (E), IL-1R1 (F), IL-1β (G), TNFR1 (H), TNFR2 (I), and TNF-ɑ (J) in the nodose ganglion. For the nodose ganglion, the number of biological samples (pools—each pool consists of 4 ganglia collected from 2 rats) per group ranged as follows: Basal (n = 6), LPS 60 min (n = 5–6), LPS 90 min (n = 5–6), and LPS 120 min (n = 5–6). Gene expression of TLR4 (K), NF-κB (L), MyD88 (M), IL-6R (N), IL-6 (O), IL-1R1 (P), IL-1β (Q), TNFR1 (R), TNFR2 (S), and TNF-ɑ (T) in the aortic arch. For the aortic arch, the number of animals per group ranged as follows: Basal (n = 6), LPS 60 min (n = 5–6), LPS 90 min (n = 4–6), and LPS 120 min (n = 5–6). Data are presented as mean ± standard deviation. Please refer to Supplementary Tables S6 and S7 for detailed statistical analyses and the exact number of biological samples or animals for each specific parameter. *p < 0.05 vs. Basal; &p < 0.05 vs. LPS 60 min; %p < 0.05 vs. LPS 90 min
Following systemic LPS administration, the ganglion exhibited a dynamic and time-dependent inflammatory response. A rapid activation of the intracellular signalling cascade was evidenced by the early (60 min) and sustained (90 min) upregulation of NF-κB gene expression, which was preceded by a transient increase in MyD88 (Fig. 6B, C, respectively). This swift activation translated into an immediate pro-inflammatory output, characterized by a sustained rise in IL-1β and TNF-ɑ gene expression starting at 60 min (Fig. 6G, J, respectively). To amplify its sensitivity to this inflammatory environment, the ganglion also upregulated the IL-1R1 and the TNFR2 (Fig. 6F, I, respectively).
Furthermore, the results suggest a secondary phase of inflammation, since an increase in IL-6 expression 90 and 120 min after LPS was observed (Fig. 6E). This upregulation occurred without a simultaneous change in the expression of its receptor, IL-6R, which remained unchanged across all groups (Fig. 6D). This indicates that the nodose ganglion maintains a constitutively sufficient level of IL-6R, and its response to the cytokine is therefore primarily controlled by the availability of the ligand rather than by the transcriptional modulation of its receptor. This later induction of IL-6, a pleiotropic cytokine, may indicate a role for the ganglion not only in propagating the acute inflammatory alarm but also in modulating the transition towards the systemic acute phase response or even its eventual resolution.
Additionally, we observed evidence of sophisticated regulatory mechanisms. While most of pro-inflammatory targets were upregulated, TLR4 gene expression progressively decreased following the LPS challenge (Fig. 6A), suggesting a potential negative feedback mechanism to prevent excessive stimulation. Similarly, the differential regulation of TNF receptors, with a late decrease in the pro-inflammatory TNFR1 (Fig. 6H) alongside a sustained increase in the pro-survival TNFR2 (Fig. 6I), suggests an intrinsic capacity of the ganglion to fine-tune its response to TNF-ɑ.
Immunofluorescence imaging revealed the constitutive expression of all evaluated markers (TLR4, NF-κB, IL-6R, IL-6, IL-1R1, IL-1β, TNFR1, TNFR2, and TNF-α) in the nodose ganglion (Fig. 7). Quantitative analysis demonstrated that immunoreactivity for TLR4, NF-κB, and IL-6 increased at 120 min post-LPS compared to the Basal group, alongside a biological trend for TNF-α (Supplementary Fig. S6B). Furthermore, the protein analysis by Western Blot confirmed that the components of the signalling pathway, including TLR4, MyD88, IκBɑ, p65 NF-κB, and p38 MAPK, together with several cytokines and their receptors, were constitutively present in the ganglion both with and without the LPS challenge (Supplementary, Fig. S3), establishing the nodose ganglion as a dynamic and self-regulating centre in the neuroimmune network.
Fig. 7
Immunoreactivity of inflammatory mediators in the nodose ganglion. Representative images showing the immunoreactivity of interleukin-1β (IL-1β; A), interleukin-1β receptor (IL-1R1; B), interleukin-6 (IL-6; C), interleukin-6 receptor (IL-6R; D), tumour necrosis factor receptor type 1 (TNFR1; E) and type 2 (TNFR2; F); toll-like receptor 4 (TLR4; G); tumour necrosis factor (TNF; H); nuclear factor kappa B (NF-κB; I); and the neuronal marker PGP9.5 (J) in transversal sections of the nodose ganglion (Basal, upper panels) and 120 min after LPS treatment (lower panels). Scale bars correspond to 20 μm. Magnification: 40 × . Quantitative analysis of the immunoreactivity is provided in Supplementary Fig. S6B
The aortic arch expresses inflammatory markersConsidering the aortic arch is the anatomical location of the sensory nerve endings for the ADN, we sought to determine if this region also functions as a direct immune-sensing site. Our analysis confirmed that the aortic arch constitutively provides the molecular machinery for an innate immune response, with basal gene expression detected for all evaluated inflammatory markers (Fig. 6K-T). Following systemic LPS administration, the aortic arch activated a powerful and temporally orchestrated inflammatory response. The first sign of this response was the upregulation of TNF-ɑ gene expression, which was significantly elevated at 90 min post-injection (Fig. 6T). This signal coincided with the transcriptional activation of the master inflammatory regulator, NF-κB, at 90 and 120 min (Fig. 6L). This, in turn, appeared to drive a major, coordinated wave of pro-inflammatory gene expression at the 120-min peak, including the signalling adaptor MyD88, the cytokines IL-6 and IL-1β, and the receptors IL-1R1 and TNFR1 (Fig. 6M, O, Q, P, R, respectively).
This pro-inflammatory cascade was also accompanied by evidence of sophisticated self-regulation. Similar to the ganglion, the primary LPS sensor TLR4 was progressively downregulated at the gene level, likely representing a negative feedback mechanism to prevent an excessive local inflammatory reaction (Fig. 6K). Furthermore, the expression of IL-6R and TNFR2 remained unchanged (Fig. 6N, S, respectively), suggesting a differential regulatory strategy where the tissue selectively modulates its sensitivity to certain cytokines (like IL-1β and TNF-α via TNFR1) while maintaining a stable capacity to respond to others.
Finally, immunofluorescence analysis provided visual and quantitative evidence of these findings (Fig. 8 and Supplementary Fig. S6C). Quantitative analysis of the immunoreactivity demonstrated that LPS administration increased the expression of key markers in the aortic arch, including TLR4 and IL-1R1 (Supplementary Fig. S6C). Interestingly, prominent TNFR2 protein labelling was also detected, despite its stable gene expression, pointing towards post-transcriptional or post-translational regulatory mechanisms. The constitutive presence of the entire protein set was also confirmed in our analysis (Supplementary, Fig. S4 and S5), solidifying that the aortic arch is also an active and dynamic immune-sensing region where the initial interactions between systemic inflammation and the nervous system could occur.
Fig. 8
Immunoreactivity of inflammatory mediators in the aortic arch. Representative images showing the immunoreactivity of interleukin-1β (IL-1β; A), interleukin-1β receptor (IL-1R1; B), interleukin-6 (IL-6; C), interleukin-6 receptor (IL-6R; D), tumour necrosis factor receptor type 1 (TNFR1; E) and type 2 (TNFR2; F); toll-like receptor 4 (TLR4; G); and nuclear factor kappa B (NF-κB; H) in transversal sections of the aortic arch before (Basal, upper panels) and 120 min after LPS treatment (lower panels). Scale bars correspond to 20 μm. Magnification: 40 × . Quantitative analysis of the immunoreactivity is provided in Supplementary Fig. S6C
To summarize, the gene expression profile across the aortic baroreceptor afferent pathway is presented in Supplementary Table S1. Our analysis revealed that all evaluated targets were expressed at the transcript level in the ADN, nodose ganglion, and aortic arch under basal conditions. After LPS injection, a coordinated increase in the expression of several genes was observed, particularly at 120 min. Notably, key inflammatory genes that were upregulated in the ADN, such as IL-6 and IL-1R1, showed a synchronized increase across the nodose ganglion and the aortic arch as well at this later stage of inflammation (120 min post-LPS), suggesting a common activation pathway shared by these tissues.
Comments (0)