In this large observational cohort study based on UK primary care-data, use of diclofenac, ibuprofen, or naproxen was not associated with an increased risk of diagnosed neutropenia or agranulocytosis compared to paracetamol after adjustment for confounders. Reduced risks observed in secondary outcomes (HES inpatient data and laboratory values) may reflect measurement bias or residual confounding, although an increased risk of neutropenia and/or agranulocytosis in association with paracetamol cannot be ruled out.
Whether NSAIDs and/or paracetamol increase the risk of drug-induced neutropenia has been debated for decades. The International Agranulocytosis and Aplastic Anaemia Study (IAAAS), a large population-based, multiregional case control study, observed no increased risk of agranulocytosis (odds ratio (OR) 0.9, 95% CI 0.3–3.1) in association with NOAD use overall (including diclofenac, ibuprofen, naproxen, and other NSAIDs) and paracetamol use specifically (OR 1.0, 95% CI 0.5–1.9). They identified cases of agranulocytosis, based on symptoms and neutrophil count (< 0.5 × 10⁹/L) that resulted in hospital admission and compared them to other hospital admitted patients of the same sex and similar age. Medical history and potential confounding factors were obtained by structured questionnaires [24].
In contrast, other observational (mainly case-control) studies reported variable associations, with effect estimates ranging from null to several-fold increased risks. A nested case-control study using the General Practice Research Database (GPRD, now CPRD) reported approximately twofold increased risks of neutropenia (defined as Read code diagnosis of neutropenia) for NSAIDs and NOADs overall (adjusted odds ratio (aOR) 2.1 (1.8–2.4) and 1.7 (1.5–2.0)), and an almost threefold increased risk of neutropenia in association with certain doses of ibuprofen (aOR up to 2.9), although without consistent dose-response patterns and a null result for the most commonly used dosage in their dataset (i.e., 1,200 mg/day) [5]. Similar results were observed in a Dutch study with an aOR of agranulocytosis of 2.4 and 2.5 for NSAIDs and paracetamol when comparing hospital-based patients with agranulocytosis to a sample of controls from community pharmacies (PHARMO RLS database) [7]. A US claims-based study reported higher estimates of neutropenia in association with NSAIDs overall (aOR 3.6, 90% CI 1.9–7.1) [6]. Other analyses found no association for several NSAIDs but elevated risks for specific agents such as diclofenac or paracetamol (ORs up to ~4–5), often with wide confidence intervals [8, 9].
Taken together, existing evidence is inconsistent, and methodological limitations may partly explain these discrepancies. All mentioned studies compared drug exposure (i.e., NOAD exposure) to non-use, which increases susceptibility to confounding by indication [25]. Some studies matched on age, sex, and setting [5, 6, 8], but residual confounding is likely, because confounders such as patient frailty, co-morbidities, underlying infections (and their severity) were incompletely captured—but likely present—given the non-user comparator. Confounding by indication is particularly relevant, because NOADs are frequently prescribed to treat fever or pain, possibly originating from an infection, which itself increases the risk of neutropenia [18]. Moreover, protopathic bias may be present if the infection was an early symptom of a yet undiagnosed neutropenia. In addition, exposure assessment based on questionnaires was done in three studies and may have introduced recall bias [8, 9, 24].
In our cohort study, we addressed several of these limitations by comparing individual NSAIDs to an active comparator group (i.e., paracetamol) using weighting on fine strata of the PS, thereby improving baseline covariate balance between comparison groups. In clinical practice the relevant question is usually not whether to prescribe a NOAD, but which NOAD to choose. Thus, our active comparator approach not only minimizes confounding by indication but also answers a clinically meaningful question regarding the comparative safety of commonly used NOADs.
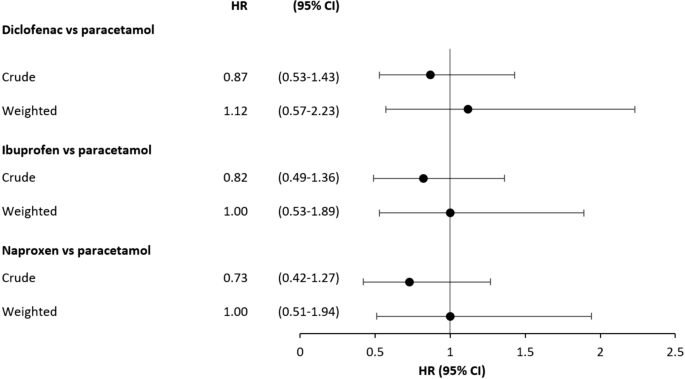
Across all three primary comparisons (diclofenac, ibuprofen, and naproxen vs. paracetamol) results were null when evaluating the primary outcome based on recorded Read code diagnoses for neutropenia or agranulocytosis. Sensitivity and additional analyses were all either a null result or revealed slightly lower HRs when comparing NSAIDs versus paracetamol (e.g., subgroups by sex, age, GP-visits and the as-started analyses). When evaluating our secondary outcome (additionally including HES-recorded diagnoses of agranulocytosis) and our tertiary outcome (additionally including laboratory values indicating neutropenia), HRs were consistently lower (between 0.53 and 0.67) except for naproxen versus paracetamol when analysing the tertiary outcome (null result). The restriction of the secondary and tertiary outcome to agranulocytosis yielded even lower risk estimates, although based on smaller numbers of outcomes. These discrepancies suggest that some measurement bias is present in at least one of our outcome definitions.
A key limitation of our study is the lack of formal outcome validation. Within CPRD, options for validation are limited. Linkage to inpatient HES data allows confirmation of hospital-recorded agranulocytosis in those patients who have HES-linkage (approximately 50% of the CPRD GOLD population) but does not capture milder neutropenia. Given that agranulocytosis is rare, sample size of recorded agranulocytosis diagnoses in HES data is small. Alternatively, GP questionnaires can assess recorded diagnoses but cannot identify missed cases (false negatives), as laboratory values cannot be measured in hindsight. Indeed, our data indicate that most cases of neutropenia identified through laboratory values (tertiary outcome definition) do not receive a formal Read code diagnosis of neutropenia. Furthermore, there is concern that differential testing between exposure groups and paracetamol users may have introduced detection bias. Before weighting, paracetamol users were older, and had more co-medications and more co-morbidities compared to NSAID users and to non-users. Despite balancing different risk factors and confounders by PS-fine stratification, unmeasured confounding by frailty may still be present in paracetamol users. Thus, paracetamol users may be more likely to have neutropenia detected by routine laboratory testing. Interestingly, HRs were lowest when comparing the risk of severe neutropenia (agranulocytosis) between NSAIDs versus paracetamol, which is where we expect the least measurement bias because agranulocytosis requires medical attention. However, residual confounding by frailty may still play a role. Moreover, we excluded all recorded cancer patients from our study, but it has been shown repeatedly that cancer recording is not complete (vs. cancer registry data) in CPRD GOLD. Cancer and chemotherapy are strong risk factors of agranulocytosis [26,27,28,29]. Paracetamol (but not NSAIDs) can be part of pre-medication for chemotherapy, and we can therefore not rule out residual confounding by under-recording of cancer in CPRD GOLD [30, 31].
Overall, our results do not suggest a systematically increased risk of neutropenia with NSAIDs compared to paracetamol. If anything, an increased risk among paracetamol users cannot be ruled out, especially with regard to agranulocytosis, though this is likely at least partly explained by residual confounding or bias as PS-fine stratification does not account for unmeasured confounding by frailty or cancer.
Other limitations should be considered. First, most of the investigated NOADs can be purchased OTC and we may thus have misclassified some NOAD users as non-users, which may bias results of non-user comparisons towards null. Second, our calculated IRs of Read-code recorded neutropenia largely underestimate the absolute risk of neutropenia in this population, given that most patients with a laboratory value indicating neutropenia did not receive a Read-code for neutropenia. Third, the median follow-up in our three primary comparisons was between 34 and 42 days. We therefore cannot address the long-term association between NOAD use and the risk of neutropenia, but given that drug-induced neutropenia typically occurs within the first 60 days after treatment initiation, this does not meaningfully limit interpretation of our results.




Comments (0)