
Remember me

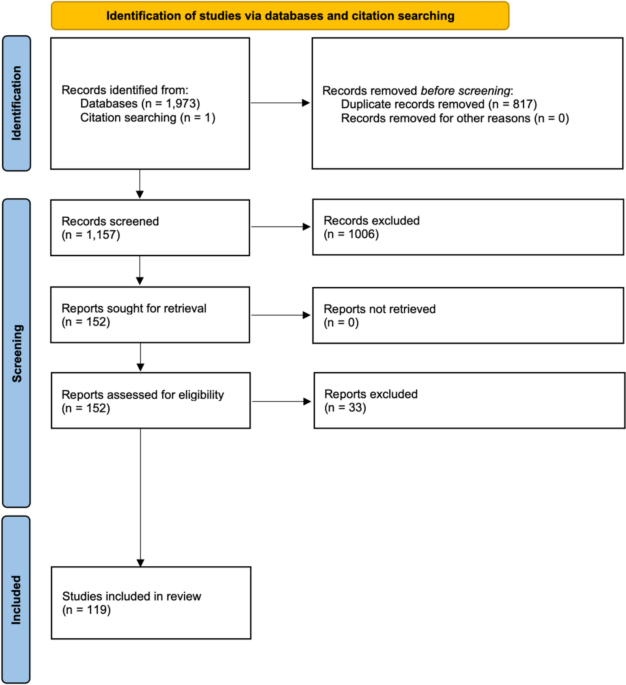


Between February 2020 and December 2023, a total of 15,250 de-duplicated ICSRs related to the study drugs were retrieved from VigiBase (Fig. 1), accounting for a total of 42,799 ADRs. Among 15,250 de-duplicated ICSRs, casirivimab/imdevimab accounted for the highest proportion of reports (33.5%), followed by bamlanivimab in monotherapy (26.0%). The remaining proportion concerned all the other anti-spike mAbs, each accounting for lower percentages.
Fig. 1
Flowchart of the selection process of ICSRs of approved mAbs for COVID-19 treatment and comparator in Vigibase in the study period. ICSRs individual case safety reports, mAbs monoclonal antibodies
Table 1 shows the main characteristics of ICSRs included in the study, stratified by single drug. Overall, most concerned female patients—except for bamlanivimab, which showed a lower female/male ratio (0.9)—and most involved adults aged between 45 and 64 years, across all study drugs. Individual case safety reports mainly originated from the Americas (55.0–98.3%) except for regdanvimab, for which 99.2% were reported from Asia. Pharmacists were the main reporters for bamlanivimab, bamlanivimab/etesevimab, and casirivimab/imdevimab (~ 47%), while physicians reported most for regdanvimab (97.9%) and tixagevimab/cilgavimab (39.5%). Reports from consumers were mostly related to sotrovimab (33.5%). The distribution of reporting lag in days ranged from a median of 59 days for bamlanivimab to 608 days for regdanvimab (Supplementary Fig. 1).
Table 1 Characteristics of reports of mAbs used in the early treatment of COVID-19, and the whole database (excluding vaccines) in VigiBase®, between 1st February 2020 and 31st December 2023Figure 2 shows the temporal distribution of ADRs possibly related to study drugs in relation to the circulation of VoC, stratified by seriousness. Overall, ADR reports were especially collected during periods when each anti-spike mAb was more commonly administered. While in some cases ADRs occurred during periods when the respective drug was still effective against the circulating variant, in other cases, such as for bamlanivimab and, to a lesser extent, casirivimab/imdevimab and bamlanivimab/etesevimab, ADRs were reported during phases when the predominant variants (e.g., Delta or Omicron) were partially or completely resistant to this mAb [20, 21]. The proportion of serious ADRs remained consistently low for all study drugs, following temporal trends similar to those of non-serious ADRs.
Fig. 2

Distribution of adverse drug reactions over the study period, stratified by single drug and seriousness
3.2 Disproportionality AnalysisAfter excluding disease-related ADRs, PTs related to lack of efficacy, and/or those not drug-related, a total of 33,948 (79.3%) drug-suspected adverse reaction pairs were identified. Among these, only 3047 (9.0%) were included in the IME list. The selection process for drug-adverse reaction pairs is shown in Supplementary Table 3 (drug-adverse reaction pairs with a significant ROR: N = 1676, 55.0%). Of 83 unique drug-adverse reaction pairs with a statistically significant value of ROR, 56 (67.5%) were not listed in the SmPCs.
Significant RORs for the study drugs are shown in Fig. 3 and listed in Supplementary Table 4. For bamlanivimab, the notoriety assessment identified a total of 19 drug-adverse reaction pairs. Of these, 5 PTs belong to the system organ class (SOC) “Cardiac disorders”: acute myocardial infarction (N = 23, ROR, 18.5; 95% CI 12.3–27.9), myocardial ischemia (N = 5, ROR, 13.1; 95% CI 5.4–31.6), cardio-respiratory arrest (N = 12, ROR, 5.6; 95% CI 3.2–9.9), myocarditis (N = 5, ROR, 4.1; 95% CI 1.7–9.9), and cardiac arrest (N = 17, ROR, 3.0; 95% CI 1.8–4.8); and 7 PTs to the SOC “Nervous system disorders”, including: encephalopathy (N = 18, ROR, 9.6; 95% CI 6.0–15.3) and facial paralysis (N = 7, ROR, 7.5; 95% CI 3.6–15.9)—both AESIs—as well as syncope (N = 49, ROR, 5.1; 95% CI 3.8–6.7), transient ischemic attack (N = 6, ROR, 3.2; 95% CI 1.4–7.1), depressed level of consciousness (N = 9, ROR, 2.6; 95% CI 1.4–5.1), loss of consciousness (N = 26, ROR, 2.6; 95% CI 1.7–3.8), and cerebrovascular accident (N = 25, ROR, 2.1; 95% CI 1.4–3.1). Regarding bamlanivimab/etesevimab, cardiac adverse reactions such as bradycardia and atrial fibrillation, were already reported in the SmPC, while other ADRs, such as cardio-respiratory arrest (N = 6, ROR, 5.5; 95% CI 2.5–12.2) and angina pectoris (N = 6, ROR, 6.4; 95% CI 2.9–14.2), were not listed. Cardiac arrest (N = 6, ROR, 2.3; 95% CI 1.1–5.1) and atrial fibrillation (N = 15, ROR, 3.8; 95% CI 2.3–6.4) were also reported for sotrovimab. Regarding casirivimab/ imdevimab, 5 out of 15 PTs were classified as AESI: seizure-like phenomena (N = 8, ROR, 44.2; 95% CI 21.9–89.1), Guillain-Barré syndrome (N = 6, ROR 13.4, 95% CI 6.0–30.0), encephalopathy (N = 13, ROR 5.4, 95% CI 3.1–9.3), generalized tonic-clonic seizure (N = 9, ROR 5.0, 95% CI 2.6–9.7), and seizure (N = 57, ROR 3.1, 95% CI 2.4–4.0). For tixagevimab/cilgavimab, only “anaphylactic reaction” was already described in the SmPC. The majority were related to cardiac disorders, including acute myocardial infarction (N = 6, ROR 12.7, 95% CI 5.7–28.4), atrial fibrillation (N = 29, ROR 9.0, 95% CI 6.2–13.0), angina pectoris (N = 5, ROR 7.2, 95% CI 3.0–17.4), cardiac arrest (N = 13, ROR 6.0, 95% CI 3.5–10.4), myocardial infarction (N = 15, ROR 4.8, 95% CI 2.9–8.1), bradycardia (N = 9, ROR 3.2, 95% CI 1.7–6.1), and arrhythmia (N = 7, ROR 2.8, 95% CI 1.3–5.9). For regdanvimab, only two PTs were not listed in the SmPC: hypokalemia (N = 13, ROR 5.8, 95% CI 3.4–10.1) and neutropenia (N = 13, ROR 2.4, 95% CI 1.4–4.2).
Fig. 3
Forest plot of disproportionality analysis of unlabeled ADRs (at PT MedDRA level), stratified by single drug. Only PTs with statistically significant RORs are shown. ADR adverse drug reaction, MedDRA Medical Dictionary for Regulatory Activities, N number of reports, PT preferred term, ROR reporting odds ratio
Results from the sensitivity analysis were consistent with the primary analysis, with overlapping CIs across all drug-ADR pairs (Supplementary Fig. 2)
Comments (0)