Institutional Takeaways
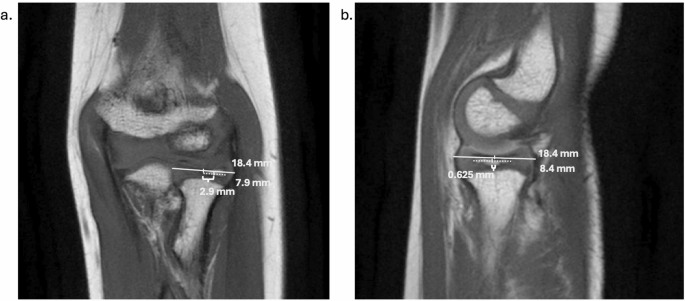
The observed eccentric radial head ossification patterns contrast with those of the capitellum, where eccentricity is more pronounced (10–18% offsets) and typically occurs in an anterior-medial direction, decreasing with age in both sexes. In capitellar studies, such as those by Fader et al., offsets centralize progressively, aligning with overall elbow ossification timelines where the capitellum ossifies earliest (around age 1) and fuses by 10–14 years [13, 14]. Radial head patterns, however, show smaller offsets (< 3% on average), with a posterior-radial predominance, and sex-specific temporal changes (centralization in males only), with no overall age correlation.
Radiocapitellar offset in the coronal plane averaged 18% for both males and females. This is consistent with Fader et al. 2016’s findings, which demonstrated that the radiocapitellar offset, when present, exclusively deviates laterally [13]. Fader et al. attributed this to the medial pattern of capitellar ossification. In the context with our study results, however, lateral radiocapitellar offset appears to be due to eccentric ossification of both the radial head and the capitellum. Clinically, lateral radiography may be more helpful in confirming radiocapitellar alignment and a degree of offset can be expected on the anterior-posterior view.
Our findings support eccentric radial head ossification as a physiologic variation rather than a pathologic marker. The lack of correlation with age, symptoms, or injuries, coupled with persistence into adolescence, mirrors capitellar eccentricity, and could explain limited reliability of the RCL in young children. The high prevalence of eccentricity in both sagittal and coronal planes, the small magnitude of offset, and the lack of consistent correlation with age collectively suggest that mild asymmetry in ossification should be anticipated during development. Importantly, eccentricity persisted into later adolescence, particularly in the coronal plane, reinforcing that incomplete centralization should not be assumed to represent abnormal alignment. These observations may have several practical implications for imaging interpretation and clinical management.
Distinguishing Physiologic Eccentricity from Pathology
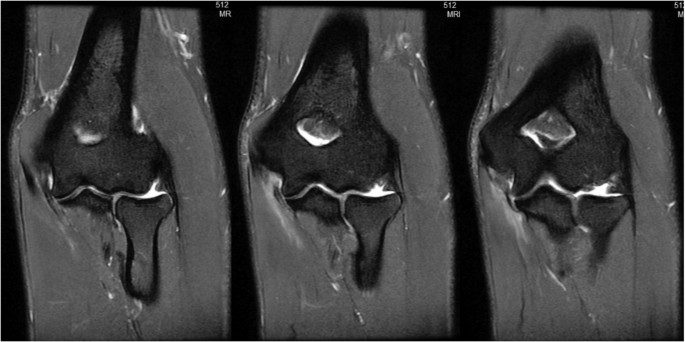
Accurate differentiation between physiologic eccentric ossification and true pathology is critical in pediatric elbow evaluation. In normal eccentric ossification, the cartilaginous anlage remains smooth and continuous, without focal disruption, collapse, or marrow edema. Although the ossified nucleus may appear offset within the cartilaginous epiphysis, overall articular congruity is preserved. In contrast, fractures typically demonstrate cortical discontinuity, marrow edema, or periosteal reaction on MRI, findings that are absent in isolated developmental asymmetry. Extrapolating from our institutional data, the magnitude of offset in the sagittal plane was small compared with that observed in the coronal plane. These findings suggest that the radiocapitellar line remains a useful measure for alignment on the lateral view, although it should be interpreted with greater caution on the anteroposterior view, where a degree of lateral offset may be physiologic.
In our cohort, average offsets were less than 3% in both sagittal and coronal planes, supporting the interpretation that small degrees of asymmetry likely fall within physiologic developmental variation. Larger deviations, particularly when accompanied by cortical irregularity, edema, or persistent clinical symptoms, may warrant further evaluation. These distinctions are especially important in younger children, in whom incomplete ossification already complicates radiographic interpretation. Recognition of physiologic eccentricity may add to existing body of work describing variability in the radiocapitellar line in young children.
Implications for Trauma Evaluation and Surgical Decision-Making
Understanding normal radial head ossification patterns has direct implications for fracture assessment. Radial neck fractures, Monteggia equivalents, and lateral condyle injuries frequently rely on radiocapitellar alignment for diagnosis and classification. When the ossified radial head is eccentrically positioned within the cartilage, apparent displacement on radiographs may not necessarily reflect true articular incongruity. In such cases, MRI can help determine whether perceived malalignment represents true radiocapitellar instability or physiologic developmental asymmetry.
Although our data does not establish a causal relationship between eccentric ossification and fracture patterns, they suggest that reliance on ossified landmarks alone may be insufficient in skeletally immature patients. Similarly, surgical planning based solely on apparent radiographic incongruity should consider developmental variation. Mild offset in the absence of cartilage disruption or instability may not in itself justify operative intervention,
Reporting Considerations
Radiology reports may benefit from explicitly acknowledging normal developmental variability. When eccentric ossification is present without edema, displacement, or cortical disruption, describing the finding as a “developmental variant” or “physiologic asymmetry” may reduce diagnostic ambiguity and limit unnecessary immobilization or additional imaging. Orthopaedic documentation should likewise incorporate age- and sex-specific developmental expectations.
Given the persistence of coronal plane radiocapitellar offset without clear age correlation in our cohort, minor deviations should not automatically be interpreted as malalignment. The radiocapitellar line remains a useful screening tool for gross dislocation, but its limitations in young children and in the setting of eccentric ossification must be recognized. Careful assessment of the lateral view is particularly important, as even small sagittal offsets may influence radiographic interpretation.
Future Directions
Our institutional data is limited by its retrospective, cross-sectional design. Although offsets were quantified across a range of ages, longitudinal imaging of individual patients would better clarify whether true centralization occurs over time and whether patterns differ by sex. Prospective cohort studies tracking radial head ossification from early childhood through skeletal maturity may better provide insight into temporal evolution. Advanced imaging techniques, including three-dimensional MRI reconstruction and emerging sequences capable of depicting cortical bone signal (such as ultrashort or zero-echo-time imaging), may further refine understanding of spatial relationships between cartilage and ossification centers. Additionally, correlating ossification patterns with biomechanical modeling approaches could help determine whether eccentricity has functional consequences. Finally, multicenter studies across diverse populations may clarify potential ethnic or demographic differences in ossification patterns, as suggested in prior studies on elbow development.




Comments (0)