Global burden and future trends
Using the GBD 2021 data, this study demonstrated that T2DM-associated CKD remains a substantial and growing global health challenge. Although the age-standardized prevalence rate declined modestly, the incidence, mortality, and disability burden generally increased between 1990 and 2021, and projection analyses indicated that incident cases will continue to rise through 2040. These findings are consistent with previous studies showing that population growth, population aging, and the increasing global prevalence of diabetes continue to drive the burden of CKD worldwide [16,17,18,19,20]. By integrating burden estimation, demographic decomposition, regional risk factor comparison, and medium-term forecasting, this study extends previous GBD-based analyses that have largely focused on individual analytical dimensions.
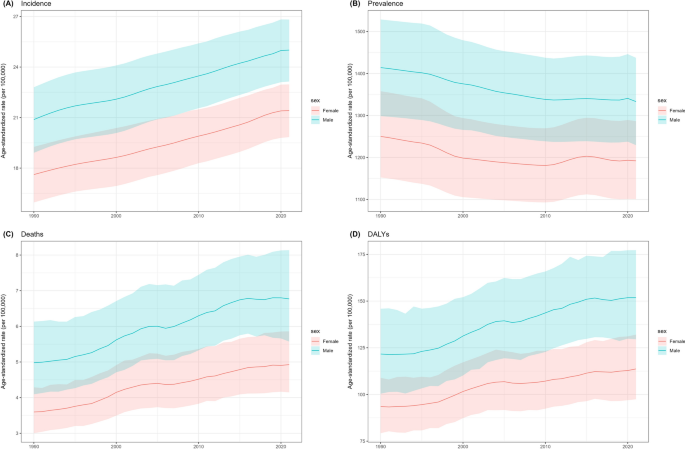
The coexistence of increasing age-standardized incidence and declining age-standardized prevalence warrants careful interpretation of these findings. This pattern likely reflects a combination of increasing diabetes exposure, earlier recognition of CKD, high mortality, competing cardiovascular risks, and the influence of age standardization rather than a contradiction between these epidemiological indicators. A similar pattern was observed in future projections, suggesting that new cases will continue to increase despite a relatively stable or declining age-standardized prevalence.
Decomposition analysis identified population growth and aging as the principal drivers of the increasing disease burden. These findings are particularly relevant because older adults represent the population with the highest burden in the present study. Previous studies have shown that older patients with CKD frequently experience multimorbidity, polypharmacy, and increased susceptibility to medication-related problems [7,8, 15, 24,25]. As populations continue to age, healthcare systems are likely to face an increasing demand for the long-term management of T2DM-associated CKD.
Regional disparities and risk factors
Substantial geographic and socioeconomic disparities were observed across the SDI categories and GBD regions. High-SDI regions consistently exhibited the highest incidence rates, whereas low- and low-middle-SDI regions experienced disproportionately high mortality and DALY burdens. Similar findings have been reported in previous global CKD studies and likely reflect differences in disease detection, healthcare access, treatment availability, and long-term disease management capacity [21, 26,27].
The higher incidence observed in high-SDI regions may reflect more extensive screening, earlier diagnosis, longer survival with diabetes, and more complete ascertainment of CKD attributable to T2DM in these regions. Conversely, the combination of lower reported incidence and higher mortality and disability burden in lower-SDI settings is compatible with delayed diagnosis, limited access to renoprotective therapies, inadequate long-term follow-up, and reduced availability of kidney replacement therapy in these settings. These findings highlight the persistent global inequalities in CKD prevention and management.
Males consistently exhibited higher incidence, mortality, and DALY rates than females. This disparity may reflect differences in cardiometabolic risk exposure, body fat distribution, blood pressure control, smoking, healthcare-seeking behavior, and long-term treatment adherence. These observations suggest that prevention and management strategies may benefit from greater consideration of sex-specific risk profiles.
Risk factor analyses further demonstrated substantial regional heterogeneity. High fasting plasma glucose and elevated body mass index remained the dominant modifiable contributors worldwide, whereas low physical activity contributed more prominently in East Asia and Oceania than in other regions. In contrast, the consumption of highly processed meat was a relatively greater contributor in High-income North America. These findings suggest that prevention strategies should combine globally recognized risk factor control with interventions tailored to regional risk profiles.
Clinical implications
Major advances in pharmacotherapy, including SGLT2 inhibitors, GLP-1 receptor agonists, and non-steroidal mineralocorticoid receptor antagonists such as finerenone, have substantially improved the management of T2DM-associated CKD and are now recommended in international diabetes and kidney disease guidelines [9,10,11,12,13,14]. Nevertheless, the projected increase in disease incidence suggests that the wider implementation of evidence-based renoprotective therapies, together with the earlier identification of high-risk individuals, will be necessary to reduce the future burden of disease and support long-term healthcare planning.
Strengths and limitations
This study provides a comprehensive assessment of the burden of T2DM-associated CKD in 204 countries and territories using GBD 2021 data. Its major strengths include the use of the most recent GBD dataset, simultaneous comparisons across SDI categories and GBD regions, and the integration of burden estimation, demographic decomposition, regional risk factor comparison, and projection analysis within a single analytical framework. Together, these analyses provide a comprehensive overview of the global epidemiology and future trends of T2DM-associated CKD.
This study has several limitations. First, all estimates were derived from the GBD database and therefore depended on the quality, completeness, and modelling assumptions of the underlying data sources. Estimates for some regions may have been affected by the limited surveillance data. Second, the ecological design precluded the assessment of patient-level treatment patterns, medication adherence, and clinical outcomes, and causal relationships between risk factors and disease burden could not be established. Third, stage-specific CKD analyses were not available in the present study design. Fourth, although NORDPRED provides a structured approach to medium-term forecasting, projected estimates should be interpreted cautiously because formal external validation was not performed. Finally, temporal changes in population-attributable fractions were not evaluated and warrant further investigation in future studies.



Comments (0)