The prevalence of HPV OPSCC patients has risen gradually in recent years [25, 26]. HPV-related OPSCC is a distinct tumor entity with clinical, epidemiologic, genetic, histologic, prognostic, and treatment differences from smoking and alcohol related OPSCC [27]. The evaluation of epidemiological data showed that there were regional differences in the incidence rate of HPV-related OPSCC. In North America and North Europe, HPV positivity rates are notably higher (exceeding 60%), while in Southern Europe, these rates are significantly lower (below 20%) [28,29,30]. A meta-analysis incorporating data from 28 studies involving a total of 2,896 patients with head and neck tumors across China revealed that HPV16 prevalence among head and neck cancer cases was 24.7% (20.2–29.3%) in China [31]. The results of the RTOG 0129 study demonstrate that HPV + OPSCC exhibits heightened sensitivity to chemoradiotherapy, superior treatment responsiveness, and improved survival rates and quality of life compared to HPV- OPSCC patients [32]. Consequently, these findings suggest a potential for de-escalation therapeutic strategies in HPV-related OPSCC patients. The HPV status plays a pivotal role in the diagnosis, staging, and guiding clinical management strategies for OPSCC. The current gold standard for HPV infection detection involves the use of PCR or in situ hybridization methods to identify HPV DNA or mRNA within tumors, but with certain technical prerequisites. Integration of HPV into host DNA can lead to overexpression of p16 protein; hence, p16 serves as a surrogate marker for HPV identification in oropharyngeal cancers. Given the practicality and ease of clinical application and dissemination of p16 IHC assays, it has been chosen as the primary recommended method by the AJCC. A recent multicenter, multinational retrospective study on a Western population revealed that 9.2% of patients exhibit inconsistent expression patterns between HPV and p16. Among the 3,805 p16 + patients, 415 (10.9%) were HPV-. This study further disclosed that the rates of p16 and HPV discordance vary across different geographical regions, with such discrepancies significantly influencing disease free survival and overall prognosis in these patients [33]. Presently, the bulk of evidence regarding HPV/p16 inconsistent and its impact on prognosis predominantly pertains to Western populations. Given that the prevalence of HPV + is lower in Chinese populations with head and neck tumors compared to those in European and North American countries, the implications of HPV/p16 inconsistent expression on outcomes in this context remain uncertain and warrant further investigation [30]. To our knowledge, there have been no prior studies analyzing this issue specifically in a Chinese population; thus, the present study aims to address this gap by conducting a relevant analysis.
In this study, we employed a highly recognized and accurate HPV DNA PCR method for HPV detection and genotyping. The observed HPV + rate (28.5%, 37/130) was consistent with previous statistical analyses [31]. Notably, among these, p16- was found in only four cases that were non-HPV16 types, which could potentially be attributed to technical limitations or the presence of mutations or deletions within the patient’s p16 gene, thereby inhibiting p16 protein expression [34]. Due to the high cost of HPV DNA testing, limitations in hospital resources and technical capacities, its application in clinical practice is constrained. Consequently, p16 IHC has been embraced as a pragmatic alternative. However, it must be noted that p16 expression lacks specificity for HPV presence; hence, p16 IHC detection does not fully equate with HPV testing. This inherent characteristic opens up the possibility for discrepancies between p16 expression levels and HPV specific test results. The frequent presence of p16 overexpression in OPSCC reflects dual mechanisms: HPV-driven pathogenesis involves E6/E7 oncoproteins that disrupt tumor suppressor pathways (e.g., p53 and Rb), with HPV E7 specifically inducing histone H3 lysine 27 acetylation (H3K27ac) at oncogene enhancers such as MYC to promote tumor growth [35]; conversely, HPV-independent p16 overexpression may arise from alternative molecular pathways, including Rb gene mutations/deletions, CDKN2A mutations, KMT2D-mediated chromatin remodeling, or p16 gene amplification [34,35,36]. In this study, the p16 + rate was 41.5% (54/130), yet only 61.1% (33/54) of these cases were HPV-positive, significantly lower than the 89.1% positive predictive value reported in Western populations [33], likely attributable to the lower prevalence of HPV-related OPSCC in Chinese cohorts. While the AJCC TNM 8th edition incorporates p16 as a surrogate for HPV status, our findings highlight its potential inadequacy in low-HPV-prevalence regions like China. Specifically, HPV-/p16 + patients, whose prognosis aligns more closely with HPV-/p16- cases, may be misclassified as HPV-driven under the current TNM system, risking inappropriate de-escalation therapy. Recent studies emphasize that dual HPV/p16 testing is critical to avoid such misclassification, as HPV-/p16 + tumors often exhibit distinct molecular profiles (e.g., TP53 mutations) associated with poorer treatment responses [33, 37]. These data challenge the universal application of TNM staging criteria optimized for Western HPV-high-prevalence cohorts and advocate for region-specific adaptations integrating HPV genotyping. Notably, HPV-negative p16-overexpressing tumors are associated with aggressive phenotypes and therapy resistance, underscoring the prognostic importance of dual HPV/p16 testing to optimize treatment strategies. These findings suggest that p16 serves as a reliable surrogate marker for HPV-driven OPSCC in regions with high HPV attribution (e.g., Europe and North America), whereas its biological and clinical interpretation requires caution in low-HPV-prevalence settings.
Our study findings demonstrated significant differences among the three distinct subgroups in patient age, smoking status, alcohol consumption, TNM staging, tumor differentiation, and treatment modalities. However, a notable distinction from Western populations is that our study reveals that the demographic and clinical characteristics in the inconsistent expression subgroup more closely resemble those of HPV-/p16- patients [14, 33]. In our cohort, HPV+/p16 + patients had a median age of 61 years (mean 57.9 ± 8.4), which is slightly higher than the median age of 55–58 years reported in Western studies [33, 38]. This discrepancy may reflect variations in individual lifestyle factors across populations. However, direct comparative data between Asian and Western HPV+/p16 + cohorts remain limited, warranting further multinational studies. The double positive subgroup exhibited lower rates of smoking and alcohol use suggesting that HPV infection plays a predominant etiological role in these patients. This observation underscores the importance of routine HPV testing for oropharyngeal lesions. In the present study, patients with HPV+/p16 + were more likely to have advanced TNM stages of tumors. This is mainly attributed to the characteristic presentation of HPV + OPSCC tumors, often characterized by small primary lesions with extensive metastatic spread, where the primary tumor mass is relatively small, predominantly exophytic, and has superficial infiltration. Notably, early and significant lymph node metastasis frequently occurs alongside cystic changes in these patients. In our study cohort, patients exhibiting higher proportions of p16 positive cells or more intense p16 staining demonstrated a superior prognosis. We speculate there exists a positive correlation between patient outcomes and both the ratio of p16 positive cells and the intensity of p16 staining; however, this hypothesis necessitates further validation through analysis with larger datasets in subsequent research endeavors. Consequently, some studies propose that when encountering cases of cervical lymph node metastasis from an unknown primary squamous cell carcinoma, if p16 + is detected, it suggests an association with HPV infection, necessitating a high degree of suspicion for a possible oropharyngeal origin, particularly in the tonsil and base of tongue regions [35, 39].
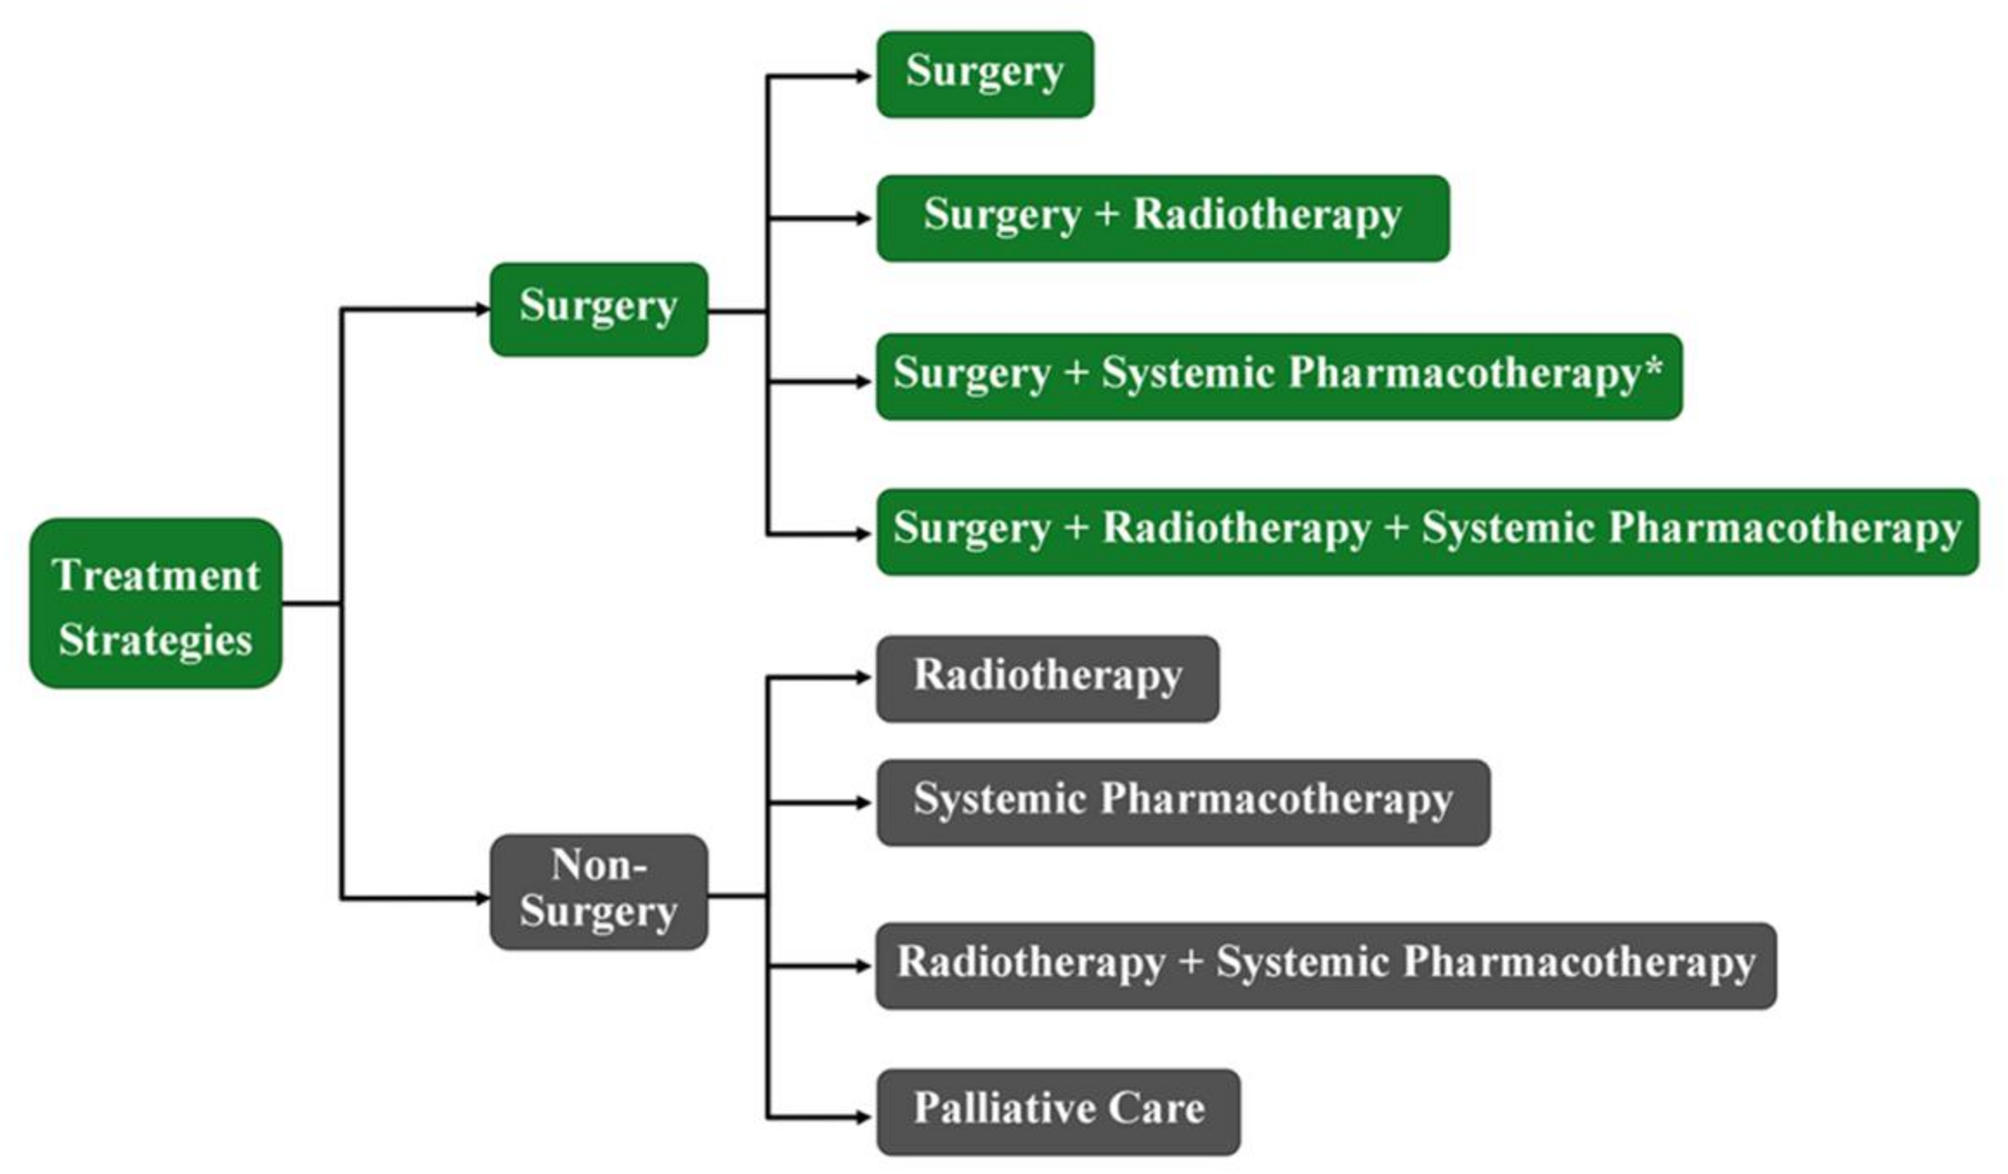
The inconsistent of HPV/p16 is instructive significance for clinical treatment strategy. Currently, surgery remains the primary treatment modality for OPSCC [40]. However, HPV positivity serves as a standard for de-escalation therapy in HPV-related OPSCC patients, which can avoid excessive surgical treatment for patients and significantly improve the prognosis survival rate and quality of life of patients [41, 42]. The recognition of HPV status plays a pivotal role in tailoring treatment intensity and thus optimizing patient outcomes. In our study, the group of patients with inconsistency between p16 and HPV DNA status represents a somewhat heterogeneous cohort, characterized by features that align more closely with HPV-/p16- than HPV+/p16 + patients. Their PFS and OS rates fall between those observed for either HPV+/p16 + or HPV-/p16- patients, as evidenced by their position intermediate along Kaplan-Meier curves. While HPV+/p16 + patients exhibit significantly higher survival rates compared to both HPV-/p16- and inconsistent patients, we found no statistically significant difference in survival rates between inconsistent patients and HPV-/p16- patients. In contrast to Western populations, the prognosis of inconsistent patients in our study is more akin to that of HPV-/p16- OPSCC patients. In the era where HPV-related and HPV-unrelated OPSCC exhibit distinct prognoses, it is of paramount importance to elucidate the differential impact of p16 and HPV biomarkers on prognosis in patients with OPSCC. In China, where HPV prevalence in OPSCC is low (28.5%), our findings highlight the critical need for dual HPV/p16 testing to avoid misclassification of HPV-/p16 + tumors as HPV-driven, which could lead to inappropriate de-escalation therapy [30]. Molecular profiling of key genes (e.g., TP53, EGFR, and CDKN2A) in HPV/p16-discordant cases reveals distinct biological pathways, such as TP53 mutations associated with radiotherapy resistance and EGFR amplifications linked to poor prognosis [30, 33, 36]. Integrating these biomarkers into clinical practice could improve diagnostic accuracy, thereby facilitating appropriate patient selection for either the de-escalation or escalation of treatment strategies.
Our study has several limitations. First, the modest sample size (n = 130) may limit the statistical power to detect subtle differences between subgroups, particularly for rare categories such as HPV+/p16- cases (n = 4). Second, the hospital-based recruitment at a single institution could introduce selection bias, as tertiary care centers often manage advanced-stage tumors, potentially overestimating HPV prevalence compared to population-based cohorts. Future multi-center studies with larger, geographically diverse cohorts are needed to validate these findings and improve generalizability.


Comments (0)