
Remember me
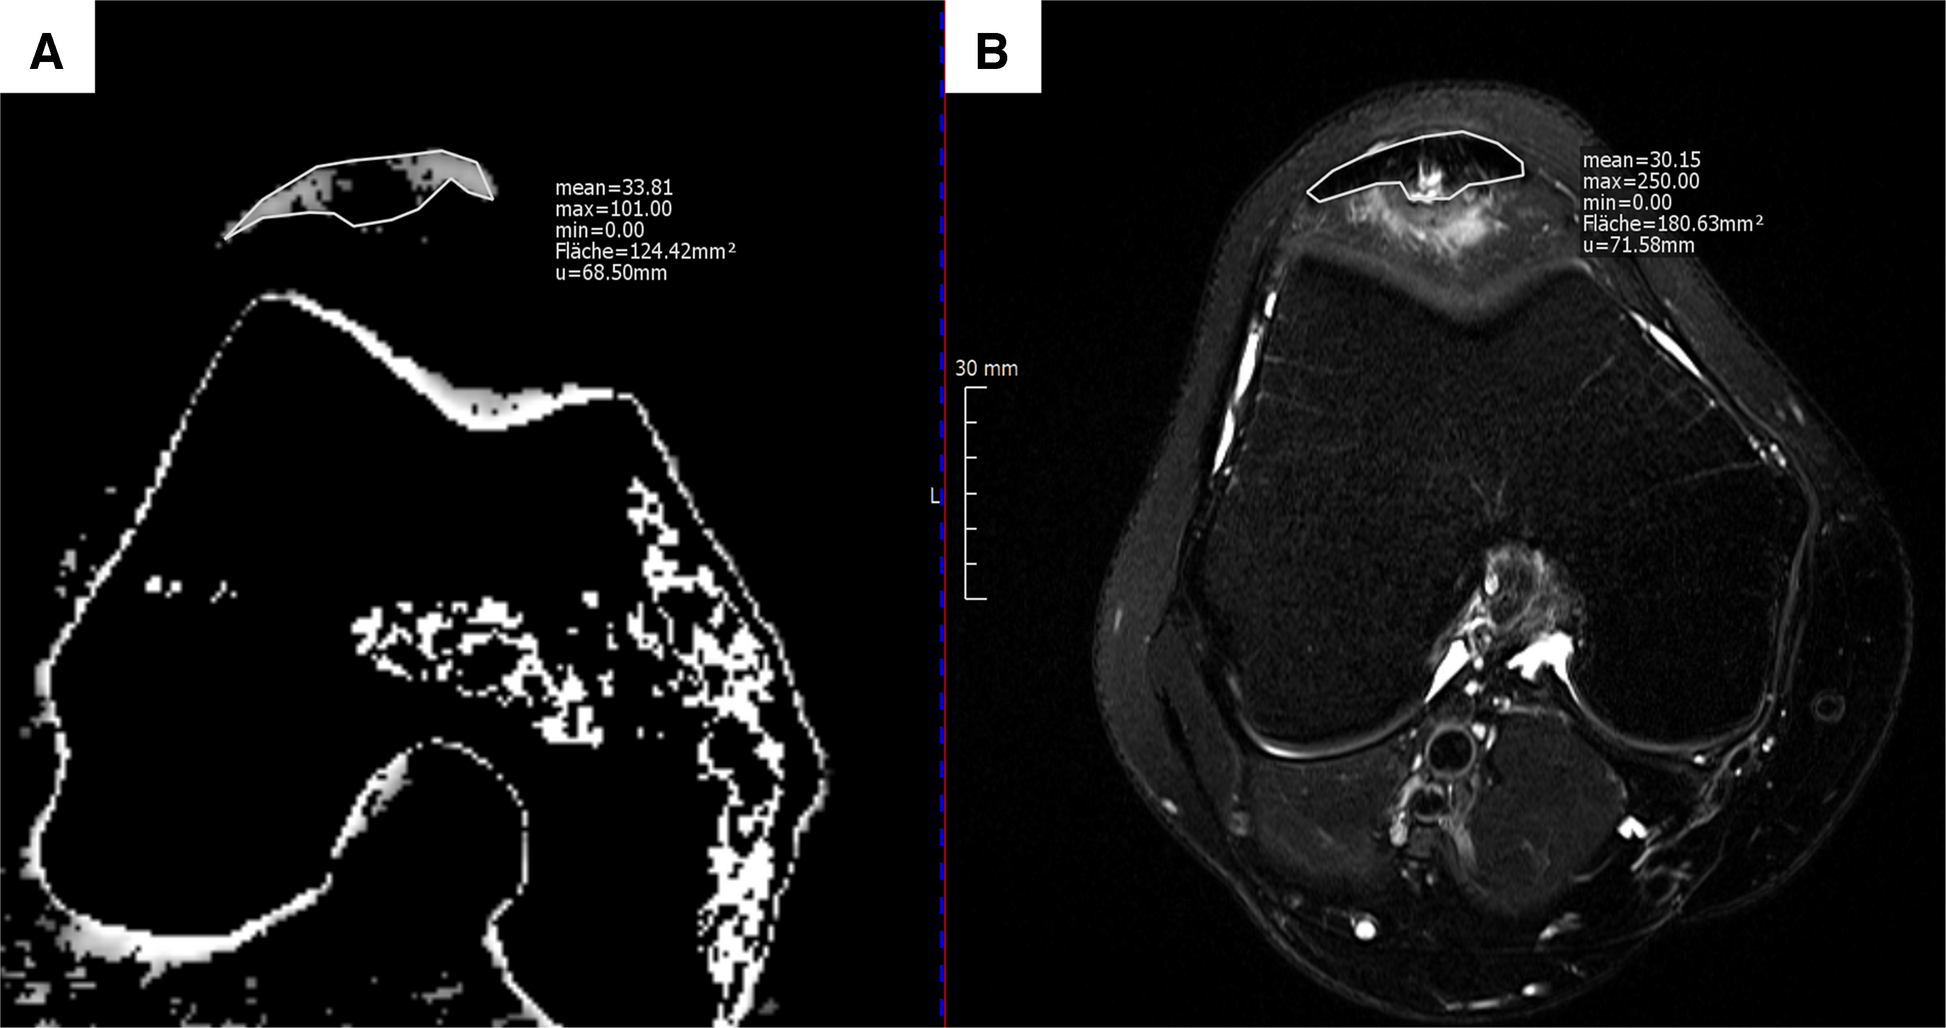
The results of our study suggest that the depth of the bicipital groove is dependent on the integrity of the LHBT. Patients with a complete LHBT tear were found to have a shallower groove when compared to those without a tear (Fig. 3). Longitudinal imaging in those with complete LHBT tear revealed groove shallowing over time. These findings suggest that the depth of the bicipital groove can be used to determine the chronicity of complete LHBT tear: a deep groove indicating a recent tear and a shallow groove indicating the tear is more likely chronic.
Fig. 3
Axial MR images of normal LHBT and chronically torn LHBT. A A 53-year-old woman with an intact long head biceps tendon in the bicipital groove, with groove depth measuring 5.0 mm. B A 59-year-old woman with a complete tear of the long head biceps tendon, with shallowing of the bicipital groove, demonstrating a groove depth of 3.1 mm
Shallowing of the bicipital groove following a complete LHBT tear may reflect adaptive osseous changes secondary to altered biomechanical loading. With an intact tendon, the LHBT exerts mechanical forces on the bicipital groove as it transmits loads during shoulder motion. These compressive and tensile forces contribute to the maintenance of cortical bone along the groove. Following a complete LHBT tear, this mechanical stimulus is lost, leading to osseous remodeling through osteoclast and osteoblast activity. Over time, this results in measurable groove shallowing in response to the decreased force, consistent with Wolff’s law that bone tissue forms and is remodeled in response to the mechanical forces it experiences [12].
This process may also involve histological changes at the bone-tendon interface, dependent on the presence of a tendon in the groove. Previous studies have demonstrated that fibrocartilage is present within the bicipital groove, which may function as an adaptation to the compressive loading [13, 14]. In the setting of complete LHBT tear, this fibrocartilaginous lining has been shown to regress and be replaced by loose connective tissue that resembles synovium, which further supports the concept of structural remodeling in response to loss of mechanical load [14].
Multiple prior studies have debated the interdependence of the biceps groove and LHBT tendinopathy. Pfahler et al. were among the first to report a significant correlation between biceps groove morphology and LHBT pathology. With ultrasonographic examination of the biceps tendon, they observed that a flattened bicipital groove was associated with LHBT pathological changes measured on a 0–10 point scale [15]. In a prospective study of 75 consecutive patients, Abboud et al. utilized direct arthroscopic visualization to classify LHBT pathology into normal, inflamed, partially torn, or ruptured. They then measured bicipital groove morphology on MRI and demonstrated no significant correlation of LHBT pathology with bicipital groove total opening angle, medial wall angle, or depth [10]. However, only 13 patients with ruptured LHBT were included in the study of 75 total patients, limiting the power of evaluating the correlation between biceps groove depth and complete LHBT tears. Shah et al. evaluated the arthroscopic findings following patients with subscapularis tendon tears with and without associated biceps tendon pathology. In their study, five patients had complete tears and 44 patients had incomplete lesions. They observed a decreased depth of the bicipital groove in patients with subscapularis tendon tears and biceps tendon pathology [16]. Most recently, Cardoso et al. published a series of papers which examined bicipital groove depth, width, and cross-sectional area (CSA) on both radiographs and ultrasound. They correlated these measurements to LHBT pathology examined during arthroscopy. LHBT pathology was classified as tendinopathy, partial disruption, and complete tear. When comparing patients with normal and abnormal LHBT, they found no difference in bicipital groove width, depth, or CSA [17]. Their study categorized all forms of LHBT pathology—including tendinopathy, partial-thickness tears (< 50% and > 50%), and complete tears—under a single “abnormal LHBT” group. Notably, only four cases in their cohort represented complete LHBT tears. This approach may have limited their ability to detect morphological changes specific to complete tendon rupture. The present study supports the correlation between decreased depth of the bicipital groove and biceps tendon tears, as well as demonstrates the use of MRI to determine chronicity of a LHBT tear based on groove characteristics. Notably, the present study includes only patients with a complete tear to the LHBT in the abnormal group. This suggests that changes to the biceps groove occur when the LHBT is absent (Fig. 4).
Fig. 4
Shallowing of the bicipital groove after complete tear of the long head biceps tendon. A A 57-year-old man with a complete tear of the long head biceps tendon with groove depth measuring 5.1 mm. B Follow-up examination 14 months later demonstrates shallowing of the groove, with groove depth measuring 3.4 mm
Previous authors have hypothesized anatomic morphology of the bicipital groove and proximal humerus may predispose patients to LHBT tears, with anatomically shallow and/or narrow grooves leading to tendon damage [15,16,17,18,19]. However, a temporal relationship in which LHBT pathology leads to changes in bicipital groove morphology had not been previously established. Here, we report on this temporal relationship and demonstrate that complete tear of the LHBT leads to a shallowing of the groove over time. Our findings suggest that a shallow groove is more likely a sequela of injury, not a predisposing factor to injury.
The clinical implications of the shallowing of the groove to the surrounding structures remain unknown. In patients who present with acute (< 12 week) rupture of the LHBT, the incidence of supraspinatus or subscapularis tendon tearing is significantly increased (incidence, 85–93%) [20, 21]. Rupture of the LHBT may lead to morphological changes to the proximal humerus, which result in biomechanical changes that compromise the rotator cuff structure. Alternatively, a compromised rotator cuff may increase stress on the LHBT and lead to its failure. Additional research is warranted to investigate if the morphological changes to the bicipital groove observed in this study play a role in the interdependence of the LHBT and the rotator cuff.
To date, there are no reliable imaging methods to evaluate the chronicity of a LHBT tear. The progressive shallowing of the biceps groove in response to a complete LHBT tear is a potential opportunity to assess the chronicity of an LHBT tear. In this study, even the shortest interval between initial and follow-up MRI of 14 months displayed a measurable decrease in bicipital groove depth (5 to 3 mm). Further evidence is required to evaluate the temporal progression of this response and determine its utility in determining the chronicity of an LHBT tear. Furthermore, ultrasound has been previously demonstrated to be an accurate and reliable method for the measurement of the bicipital groove depth [17, 22]. Ultrasound could serve as a less costly option in determining the chronicity of a tear in patients who present with suspected biceps pathology.
LimitationsThis study has several limitations that should be considered when interpreting the findings. The retrospective design limits control over imaging follow-up intervals and introduces variability with the timing of post-tear assessments. A prospective study with standardized imaging intervals would allow for more precise evaluation of temporal changes in bicipital groove morphology. The relatively small sample size of the longitudinal cohort with complete LHBT tears and follow-up imaging represents an additional limitation. While the observed trend toward groove shallowing was consistent across cases, the small number of patients limits the generalizability of the findings and restricts the ability to perform subgroup analyses. While a standardized measurement technique was employed, reviewers were not blinded to the presence of a biceps tendon tear, which may introduce measurement bias. Technical factors pose additional limitations. Variability in the exact location of groove depth measurement and differences in patient positioning during MRI acquisition may affect the accuracy and reproducibility of measurements. Slice thickness of 4 mm results in variation of where the measurement is performed on an axial sequence. Additionally, the use of proton density (PD)–weighted images rather than T1-weighted sequences reduces the reliability of cortical bone delineation, potentially impacting measurement precision. Imaging performed across multiple sites within the same institution contributes to variability in image quality and acquisition parameters. The absence of clinical data, such as surgical correlation of symptom duration, also limits the ability to correlate imaging findings with clinical severity or chronicity. Rotator cuff tears may independently influence the morphology of the bicipital groove and confound the observed association with LHBT tears, specifically with tearing of the subscapularis tendon. An additional limitation is the absence of longitudinal imaging in patients with initially intact LHBT who subsequently sustained a complete tear. Pre- and post-tear comparison within the same individuals would provide additional evidence to support the hypothesis that a complete LHBT tear leads to progressive shallowing of the bicipital groove. This represents a potential avenue for future investigation. Overall, larger prospective studies are needed to validate these observations and further characterize the temporal progression of osseous remodeling. Despite these limitations, the study provides evidence of a measurable association between complete LHBT tears and progressive shallowing of the bicipital groove, which may have diagnostic implications in assessing chronicity.
Comments (0)