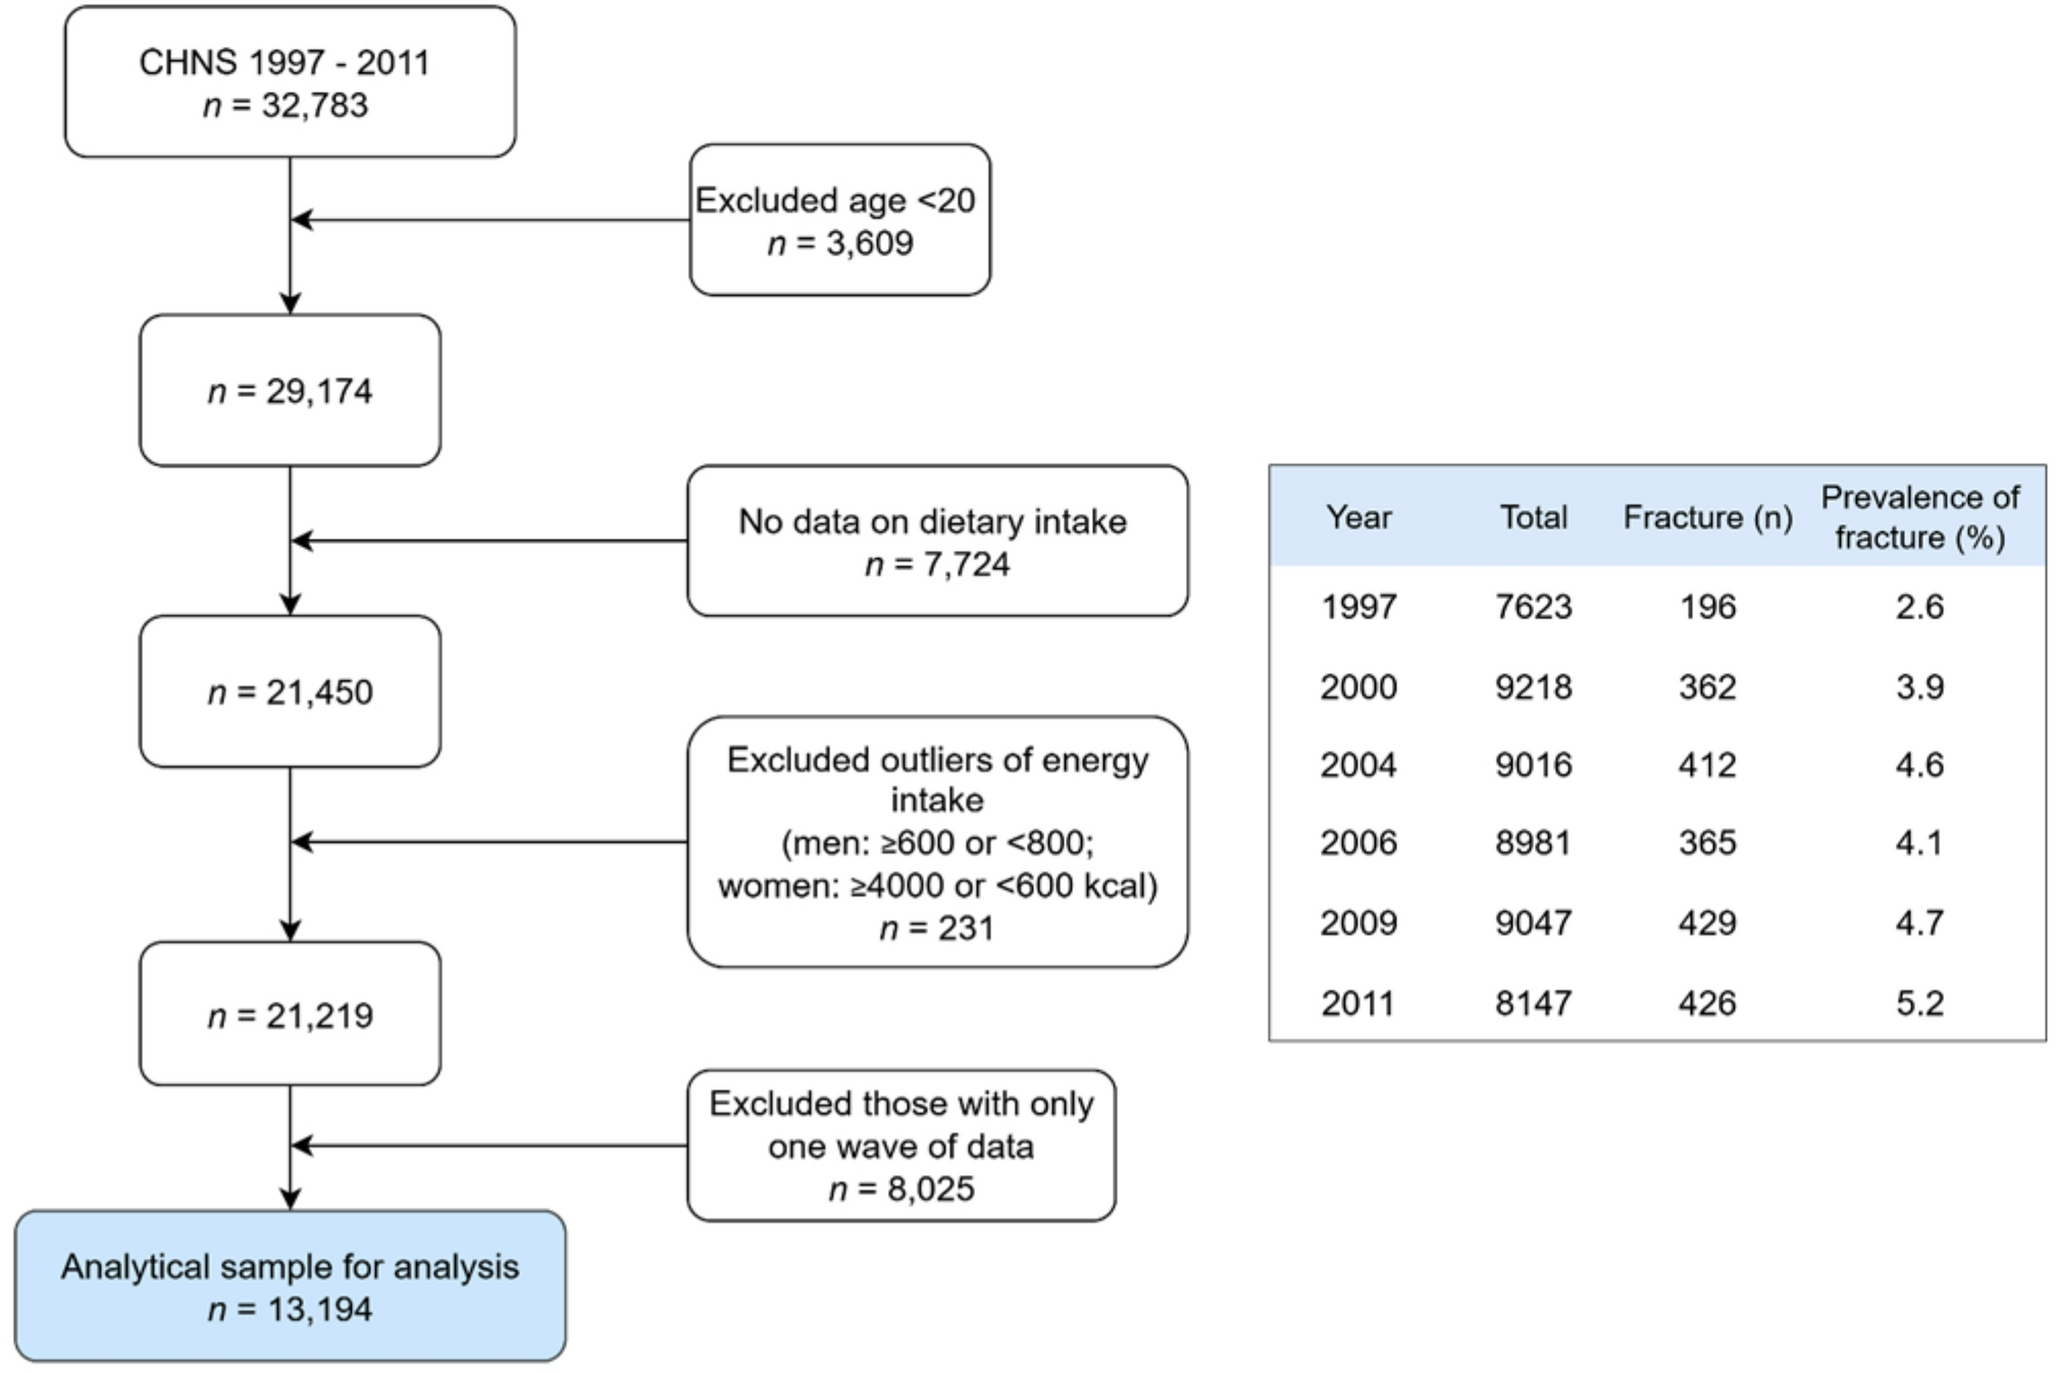
The study demonstrated a dose-responsive association between increased UPF consumption and higher odds of fracture among Chinese adults (aged ≥ 20 years) attending CHNS during 1997–2011. Specifically, adults consuming 1–49 g/day, 50–99 g/day, and ≥ 100 g/day of UPF had 46%, 64%, and 69% higher odds of fracture, compared to non-consumers, respectively. The association was independent of socio-demographic, dietary calcium and/or phosphorus, dietary pattern, and behavioral factors, and health risk such as overweight/obesity, diabetes, and hypertension. In addition, the effect size varied by residential location, with adults in rural areas experiencing more than twice the odds of fracture at UPF intake ≥ 100 g/day, while no significant association was observed among their urban counterparts.
Half of the self-reported fracture occurred in adults aged ≥ 35 years, and over a quarter occurred among those aged ≥ 50 years among the Chinese adults. These findings highlight the need to develop effective strategies to prevent fractures in older adults in facing with China’s rapidly aging population [3, 5]. To start, evidence of the burden of fracture, lifestyle, health and environmental factors is required to identify the high-risk population. The China National Fracture Study, a nationally representative population-based study of more than half a million people, reported the highest incidence in women aged 55–64 years of 7.04 (6.06–8.01) per 1000 people in 2014, with over half (58%) being fragility fractures caused by low-energy trauma (slips, trips, and falls from standing height) [30]. Further, the China Osteoporosis Prevalence Study, which included 20,416 nationally representative participants in 2017–2018, reported that among adults aged > 40 years, the prevalence of osteoporosis was 5.0% in men and 20.6% in women, assessed using x-ray absorptiometry image, and the prevalence of clinical fracture in the past 5 years was approximately 4% [31]. These estimates are broadly consistent with our estimate of 3.2% among adults aged over 18 years. Fracture history, low socioeconomic status, alcohol consumption, and average sleep time less than 7 h were independent risk factors for traumatic fracture in adults in addition to older age [30].
Adding to the other studies, we found higher consumption of UPF associated with increased likelihood of fracture in a dose-responsive manner. Although no prior studies have examined this relationship among Chinese population, cross-sectional evidence from US, Korea consistently indicated similar positive associations with fracture and/or bone health [20, 22, 32]. For example, higher UPF intake was linked to 52% increased odds of osteoporosis [22], and a 1.9% increase in self-reported fracture for each 1% increase in UPF consumption [22]. In addition, higher UPF intake was associated with 58% greater odds of low bone mineral density in Americans [20] and lower femoral neck and total femur bone mass in Koreans [32]. Consistently, a prospective cohort study from UK Biobank data revealed a 9% higher risk of osteoporosis associated with high UPF intake after a median follow up of 13.3 years of 141,577 adults [21]. Although the strength of the association from the current study is not comparable with others due to the differences in study type, the measurement of UPF intake and study outcomes, and statistical analysis, the direction of the associations are universal. A recent scope review summarized broadly the deleterious role of UPF on bone health with majority studies reporting osteoporosis or bone mineral density or joint health among not only in adults but also among children, adolescents and young adults, more high-quality research is needed to fill the knowledge gap [19]. Given the widespread availability, aggressive marketing, and affordability of UPFs have led to their increasing consumption across all age groups, including children, adolescents, and older adults, who are particularly vulnerable to bone fragility and joint diseases, and the potential public health burden of UPF consumption on bone health, the need for dietary interventions and policy changes should be reinforced [33].
This study also revealed that adults residing in rural areas were more likely to have fractures associated with increased UPF consumption comparing to “0” consumption (1.52 for 1–49 g/day, 1.91 for 50–99 g/day, and 2.19 for ≥ 100 g/day), while this trend was not observed in urban adults. This could be due to the insufficient sample of fracture in urban areas, requiring further exploration using other national data. Also, it could suggest affordability and easy access to UPF, more fractures cases of combine traumatic injury and osteopenia fracture in rural areas that could not be differentiated in this study.
Potential mechanisms
The underly mechanism of UPF consumption on increased risk of fracture has not been fully explicated, calling for more studies to elucidate the causal relationship between UPF consumption and fracture and/or bone health. Several mechanisms may explain the association, including direct bone mineral density reduction, increased systemic inflammation, and potential disruption of mineral metabolism through phosphate additives. A recent animal experiment highlighted the severe impact of consuming UPF on the growing skeleton, showing that young rats fed UPF rich in fat and sugar suffer from growth retardation due to lesions in their tibial growth plates. The bone mineral density decreases significantly, and the structural parameters of the bone deteriorate, presenting a sieve-like appearance in the cortices and poor trabecular parameters in long bones and vertebrae. This results in inferior mechanical performance of the entire bone with a high fracture risk [34]. Another laboratory study also suggests that 6-week regular UPF diet composing of bread roll, hamburger, tomatoes, lettuce, ketchup (excluding onion and pickles) and chips, alters the gut microbiome and has negative outcomes on bone parameters and bone marrow adiposity in rats after birth [35]. On the other hand, the supplementation with multi-vitamins-minerals positive effect has improved bone growth and quality that was followed by damage to the rats’ kidneys with modifications in inflammation and vitamin-D metabolism induced by UPF feeding [36]. Furthermore, this intervention study also demonstrated that a nutritional rescue approach partially improved the structural and mechanical parameters of bone [36]. Inflammatory markers such as C-reactive protein (CRP), neutrophil-to-lymphocyte ratio (NLR), and systemic inflammation index (SII) mediate UPF and osteoporosis pathway, accounting for 2.76–3.30% of this association [21], while epidemiological studies have linked UPF consumption to low-grade inflammation [21, 37] as summarized in a recent review [38]. Emerging studies have suggested that UPFs can negatively impact the gut microbiome, reducing the abundance of beneficial bacteria like Acetatifactor that produce short-chain fatty acids, which can play a role in bone health by promoting bone formation and inhibiting bone resorption [39, 40]. Others potential explanations could include deficiencies in essential bone-building nutrients like calcium, phosphorus, and vitamin A, C, and D, which are crucial for bone density and strength, especially during and after menopause due to high UPF consumption. In addition, UPFs can contribute to metabolic dysregulation, including compromised glycemic homeostasis and increased risk of metabolic syndrome, which indirectly impacts bone health. However, our study showed the association was independent of dietary intake of calcium and the metabolic risks such as diabetes, and hypertension, suggesting involvement of multiple mechanisms not solely due to dietary nutrient profile deterioration. For example, excessive phosphate-based food additives in UPFs may disrupt bone and mineral metabolism in humans [41] either directly through tissue/vessel calcification or indirectly through the release of mineral-regulating hormones, parathyroid hormone, and fibroblast growth factor-23 [42]. While some plausible mechanisms have been investigated, more research is needed to establish causal mechanisms.
Strengths and limitations
A key strength of this study is the use of a large nationwide sample, allowing for robust population-level inferences. The study period (1997–2011) encompassed a critical phase of China’s nutrition transition, capturing shifts in dietary patterns over time. UPF intake was assessed using a combination of 3-day dietary recalls and household food inventory data, providing a comprehensive and reliable estimate of long-term consumption. This methodological approach enhances the accuracy of dietary exposure assessment and strengthens the validity of the observed associations. The application of multilevel mixed effect modelling maximized the inclusion of all repeated measures over decades, allowing to account for long-term diet variations and to control for time-varying confounding in this open cohort study design in the investigation of association. A series of sensitivity analyses confirmed the robustness of the results either by including only those attending all waves of survey, or by using recurrent fracture as an outcome and cumulative UPF consumption as a long-term exposure factor in logistic regression analysis. Potential confounding factors including sociodemographic, behavioral, health, dietary factors, calcium and phosphorus were adjusted.
Limitation should be noted when interpreting the findings from this study. Firstly, fracture was self-reported. We could not differentiate fracture as an external injury or pathological event; there were neither biochemical markers to validate blood calcium, phosphorus, and vitamin D or inflammation levels, nor any bone images to verify bone mineral density or any further diagnosis as to the fracture site, which hampered the understanding of the underlying mechanism behind the increased risk of fracture associated with higher UPF consumption. Further, misclassification of UPF was possible due to incomplete records on food processing methods in the CHNS survey, which was not specifically matched with NOVA classification. The ascertainment of food items might not be subtle in reflecting the complexity of food processing and variabilities in additive composition between brands for a similar type of product, and some food items could only be grouped, therefore, the association between UPF and fracture could be biased. Finally, we cannot rule out the role of residual and other potential confounding factors, such as medication use (e.g., psychoactive medications, glucocorticoid use), supplement use (hormonal and dietary), and other health risks (e.g., kidney diseases, gout), which could potentially overestimate the associations.


Comments (0)