This NMA is, to our knowledge, the first to primarily address the comparative safety of treatments for external AGWs, an aspect that remains underrepresented in a literature largely focused on efficacy. The robustness of our findings is supported by the large number of included RCTs and patients. In addition, the use of a structured systematic review and standardized tools such as the Cochrane ROB instrument strengthens the methodological reliability of the analysis.
Our results suggest that, in general, topical treatments are better tolerated than ablative approaches, consistent with previous comparative trials evaluating TCA versus cryotherapy or imiquimod 5% versus cryotherapy [14, 15]. This supports the concept of a less invasive, topical-first strategy when clinically appropriate. However, adherence to topical treatments is often suboptimal. The World Health Organization and dermatology-specific studies estimate that one-third to one-half of patients do not adequately adhere to topical regimens [16, 17].
Imiquimod 5% was associated with a significant risk of LGL, while risks for MGL and HGL remained moderate. This requires nuanced interpretation. Yentzer et al. [18] have suggested that mild, expected local reactions may paradoxically support adherence by reinforcing the perception of an active and effective treatment, as shown in actinic keratoses. Furthermore, LGL may reflect local immune activation and a stronger inflammatory response, which has been linked to greater therapeutic benefit in some settings [19]. Thus, for imiquimod, frequent LGL might represent a manageable and expected trade-off rather than a strict disadvantage, provided that patients are adequately counseled.
Our findings are in line with the NMA by Jung et al. [6] and the meta-analysis by Yan et al. [20], confirming that podophyllotoxin is associated with higher AE rates than imiquimod. Imiquimod 5% does not appear to carry a higher AE risk than imiquimod 3.75%, contrary to the conclusions of O’Mahony et al. [21], who favored 3.75% based on its lower concentration and simplified regimen. For polyphenon E (sinecatechins), no major difference in AE risk between 10% and 15% concentrations has been demonstrated, supporting the hypothesis that the active compound rather than its dose predominantly drives tolerability [22].
CO2 laser showed the highest risk of medium-grade local adverse events. These events mainly consisted of transient post-procedural pain, minor bleeding, erosions, and local inflammatory reactions, which are expected consequences of tissue ablation and are generally self-limited. Importantly, no significant increase in high-grade local adverse events was observed, suggesting that although the CO2 laser is associated with substantial local morbidity, severe complications remain uncommon.
Cidofovir cream emerged in our analysis as the treatment with the most favorable safety profile, consistent with previous work that did not report major AEs [6]. Nonetheless, its role in treatment algorithms remains unclear. Although cidofovir appeared among the treatments with the most favorable safety profile, its efficacy remains uncertain and should be balanced against the efficacy reported for more established ablative therapies such as surgery, electrosurgery, and photodynamic therapy. Cidofovir is also absent from IUSTI’s main treatment flowcharts [3]. This suggests that cidofovir may be preferentially considered in selected clinical settings where tolerability outweighs the need for maximal efficacy.
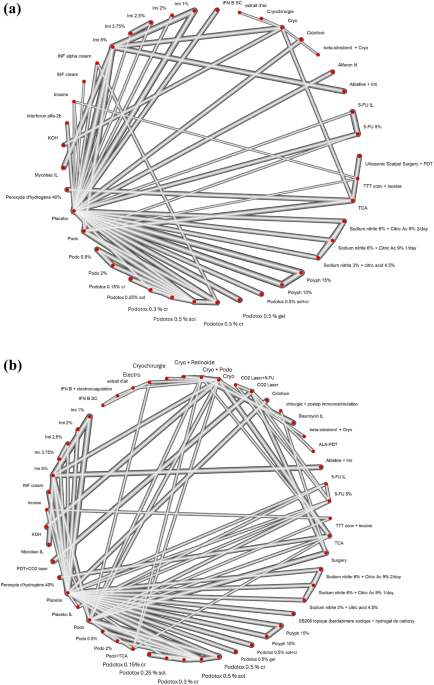
Our NMA also highlights the considerable heterogeneity in how AEs are defined and graded across AGW trials. Some studies, such as that by Tatti et al. [23], classify local reactions (e.g. edema, erosion, ulceration) into mild, moderate, and severe categories without using a standardized grading scale, making inter-study comparisons difficult. Subjective symptoms like pain are influenced by individual thresholds and psychological context, and many studies did not use validated tools such as the visual analog scales [24]. The assessment of visible signs such as erythema often relies on clinical judgment, which may vary with the observer’s experience and examination conditions. More objective methods, including computer-assisted image analysis [25], could help standardize the evaluation of erythema and better distinguish physiological from pathological changes.
Several limitations should be acknowledged. First, we did not adjust for baseline heterogeneity in important factors such as the sex ratio, number, size, and location of lesions, which may influence tolerability. Second, although global consistency was acceptable across most networks, some comparisons were based on relatively small sample sizes, and net heat plots revealed local inconsistencies, especially for certain topical combinations and placebo contrasts. Third, many included RCTs were judged to have high or unclear risk of bias, which may affect the certainty of the evidence. Finally, only the main connected component of the network was analyzed, leading to the exclusion of some potentially relevant treatments (e.g., oral isotretinoin) to maintain coherence.
Despite these limitations, the present study provides clinically relevant comparative information on the tolerability of commonly used AGW treatments, which has been lacking in prior work largely focused on efficacy alone.



Comments (0)