
Remember me



Based on accumulated experience with the RWD and RWE in regulatory submissions, this section organizes key considerations related to relevance and reliability and proposes approaches to database construction that reflect practical realities in clinical settings. The relevance and reliability discussed here assume that the data will be used as part of regulatory submission materials and that regulatory authorities may review individual patient-level data.
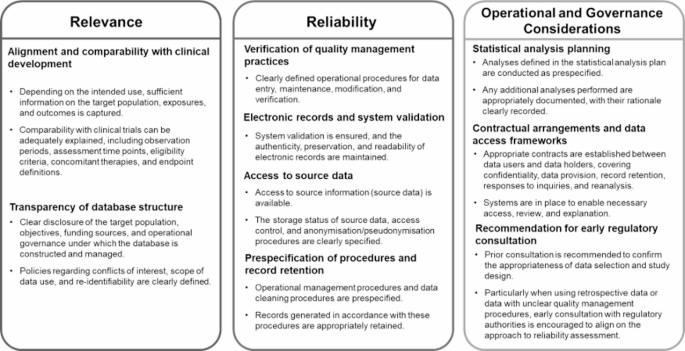
From this perspective, the key considerations for constructing such data can be consolidated into nine practical points: two related to relevance, four related to reliability, and three related to other operational considerations, as outlined below (Fig. 1).
Fig. 1
Key considerations for generating real-world data to support drug and medical product development are organized according to the concepts of relevance, reliability, and other operational considerations. Relevance focuses on alignment with clinical development objectives and ensuring comparability with clinical trials, as well as transparency of database structure and governance. Reliability addresses the establishment and documentation of quality management practices, electronic record management and system validation, access to source data, and prespecification of procedures with appropriate record retention. Other considerations include statistical analysis planning, contractual and data access frameworks, and the importance of early consultation with regulatory authorities, particularly when retrospective data or data with limited quality management information are used
RelevanceIt is essential that clinicians and healthcare professionals with expertise in the relevant development field clearly define, based on practical experience in clinical development, the data elements that should be collected. If the data are intended to be used as key evidence for regulatory purposes, data collection should, in principle, be conducted through prospective observational studies. This is because certain data elements that are critical for regulatory evaluation—such as key baseline characteristics, timing of assessments, and information related to patient consent—are difficult to collect retrospectively. Accordingly, data should be designed to ensure that necessary information is collected without excess or insufficiency. In addition, it is desirable to conduct exhaustive case registration that captures the full range of clinically anticipated patient profiles for the disease of interest.
i.Alignment and comparability with clinical development
For cases included in databases or registries, eligibility criteria should be defined in alignment with future clinical trials. When RWD are used as external control data, differences in patient populations and baseline characteristics can have a substantial impact on analytical results. Therefore, baseline factors that are expected to influence treatment effects or prognosis—many of which overlap with variables routinely collected in clinical trials—should be comprehensively captured. These data are essential for appropriate adjustment of confounding factors during analysis.
Primary, secondary, and exploratory endpoints should also be collected using assessment methods and definitions consistent with those employed in clinical trials. Such alignment should be carefully considered at the design stage.
When conducting prospective observational studies, it is necessary to establish systems that allow assessments to be performed at time points aligned with the observation periods and evaluation schedules used in clinical trials. Misalignment of time axes is difficult to correct retrospectively and therefore requires particular attention during study planning.
In comparative analyses, when toxicities associated with standard clinical practice or concomitant therapies are expected to act as significant confounding factors, such information should be prospectively included among the data elements to be collected.
ii.Transparency of database structure
Databases and registries are often constructed and operated by academic institutions. From an ethical perspective, it is practical to conduct data collection as academic research that has undergone ethical review in accordance with national ethical guidelines for life science and medical research involving human subjects.
Within this framework, it is desirable that research objectives, target populations, funding sources, and governance structures are clearly described in study protocols and publicly available documents. Appropriate systems should also be established to identify, manage, and disclose conflicts of interest within the academic research framework.
When data are collected through prospective observational studies and used for regulatory purposes, it is necessary to obtain consent for such use in accordance with the latest ethical guidelines, with explicit disclosure in the consent documents that regulatory authorities may review the data.
ReliabilityIt is important to establish reliability assurance systems that are sufficient for regulatory use while taking into account available personnel and resources. Reliability is evaluated not only in terms of data quality—centered on accuracy, completeness, and traceability—but also based on whether the procedures and records necessary to ensure such quality are appropriately established and maintained.
i.Verification of Quality Management Practices
Quality management procedures used in clinical trials and interventional studies can serve as a reference when developing quality management systems for observational research, while allowing for reasonable simplification appropriate to the study design and objectives. From the perspective of regulatory use, standard operating procedures and implementation records related to data entry, maintenance, revision, and verification should be prepared in advance.
When resources are limited, a stepwise approach—prioritizing essential procedures—may be acceptable, provided that the rationale is clearly documented. Essential processes necessary to ensure data reliability, including change histories and correction records generated during data collection and management, should be systematically recorded and retained.
ii.Electronic records and system validation
For RWD collected and stored electronically, system validation consistent with the principles of Good Clinical Practice (GCP), Good Vigilance Practice (GVP) and Good Post-marketing Study Practice (GPSP) is required. Although many electronic data capture (EDC) systems commonly used in clinical research are considered to meet these requirements, it is important, at the time of system implementation, to confirm whether vendors maintain GCP/GVP-compliant systems and supporting documentation.
iii.Access to Source Data
When RWD/RWE are used as part of regulatory submission materials, systems must be established to allow access to source data during regulatory review and reliability inspections. In particular, when RWD are intended for use as external control data, individual patient-level data should be prepared under the assumption that consistency with source documents will be verified, in a manner comparable to clinical trial data.
If cases intended for regulatory use are predefined, it is desirable to implement monitoring and source data verification (SDV) using a risk-based approach from the case accrual stage. When cases are selected for regulatory use after data collection has been completed, it is operationally reasonable to limit monitoring and SDV to the selected cases during dataset preparation. Even when cases are not intended for regulatory submission, monitoring activities—such as verification that data entry procedures and informed consent processes are appropriately conducted—may still be valuable, provided that sufficient resources and budget are available.
iv.Prespecification of Procedures and Record Retention
Data cleaning procedures should be clearly prespecified prior to implementation, and records demonstrating adherence to these procedures should be retained. When procedural or methodological changes occur during registry operation or data analysis, the details, rationale, and timing of such changes should be appropriately documented.
Comments (0)