Key Findings and Clinical Implications
This is the first study investigating the relationship between SwMM and TS and TE in HNC patients prior to treatment. We found no statistically significant correlations between SwMM, measured as the TCM area on CT scans, and TS or TE, assessed with the IOPI. Likewise, age, sex, BMI, tumor stage, comorbidity burden, and malnutrition risk were not associated with tongue performance. These findings indicate that, in untreated HNC patients, CT-based SwMM is not a reliable surrogate for TS, even when accounting for key demographic and clinical factors. In practical terms, lower tongue-function values do not necessarily indicate lower SwMM, nor do higher tongue-function values imply higher SwMM.
Discrepancies between Swallowing Muscle Mass and Tongue Function
The current diagnostic framework for sarcopenic dysphagia relies on tongue pressure measurement as a surrogate for swallowing muscle strength [6, 12]. However, the < 20 kPa cut-off was developed and has been used primarily in Japanese, non-HNC populations, including healthy older adults [14], stroke patients [35,36,37], and individuals with sarcopenia or malnutrition [16, 38,39,40,41]. Furthermore, most studies supporting this threshold were conducted using the JMS tongue-pressure device, and direct equivalence between JMS- and IOPI-derived measurements has not been established. As highlighted by Abu-Ghanem et al. [13], substantial heterogeneity remains in the assessment methods, measurement instruments, and diagnostic cut-off values used across studies of sarcopenic dysphagia, limiting the generalizability of existing diagnostic criteria across populations and clinical settings. As noted by Wakabayashi et al. [6], this diagnostic algorithm, although currently the only validated method, has been applied within a relatively narrow demographic and clinical context. In contrast, our study was conducted in a Dutch HNC population with different anthropometric and body composition characteristics [42]. The dissociation between structure (SwMM) and function (tongue pressure) observed in our study suggests that tongue pressure alone may not fully reflect swallowing muscle status in HNC patients and supports cautious interpretation when extrapolating diagnostic criteria beyond the populations in which they were developed. Because our analyses did not use cut-off thresholds, the absence of an association suggests that SwMM and TS may represent distinct but complementary aspects of swallowing muscle health in this cohort.
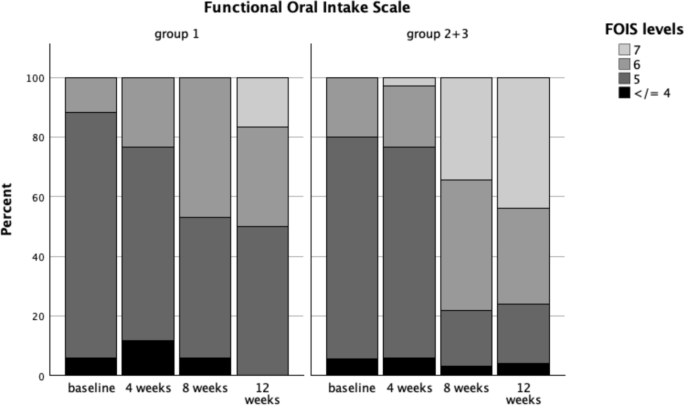
Clinically, these findings suggest that structural and functional swallowing assessments should not be considered interchangeable in HNC patients with suspected sarcopenic dysphagia. Reliance on tongue pressure measurements alone may overlook clinically relevant structural alterations in swallowing musculature, whereas imaging-based SwMM assessment alone may not adequately reflect functional swallowing performance. This pattern aligns with evidence from chronic radiation-associated dysphagia, where tongue-pressure training increases strength, yet does not translate into better functional oral intake [43], underscoring that strength gains alone do not capture the full complexity of swallowing impairment. Conversely, structural deterioration, including fibrosis and atrophy of swallowing muscles, may persist despite intense exercise-based rehabilitation [43, 44].
Previous imaging studies have investigated swallowing musculature because of its presumed relationship with swallowing function and dysphagia outcomes. In HNC populations, CT-based assessments of individual swallowing muscles or muscle groups have been associated with clinically relevant outcomes, including aspiration severity, oral intake, swallowing efficiency, treatment-related dysphagia, and nutritional status [45,46,47,48,49,50,51]. Similar efforts have been reported in other populations. Molfenter et al. demonstrated age-related differences in swallowing-muscle morphology using MRI in healthy older adults [52, 53], whereas Sporns et al. and Pinho et al. applied volumetric and composite approaches to characterize swallowing musculature more comprehensively [54, 55]. However, findings have not been entirely consistent, and structural muscle measures do not invariably correspond to functional swallowing outcomes, as illustrated by Labeit et al. [56]. These observations suggest that the relationship between swallowing-muscle morphology and swallowing performance may be more complex than a simple one-to-one correspondence.
In this context, the TCM area was developed as a CT-based proxy of global swallowing muscle mass rather than a measure of a single swallowing muscle. Previous work demonstrated strong associations between the TCM area and total swallowing muscle volume and showed that lower TCM values are associated with poorer overall muscle status in HNC patients [26, 57]. Together, these findings provided a rationale for exploring its relationship with tongue function. Such an investigation is particularly relevant because tongue pressure has been incorporated into contemporary diagnostic frameworks for sarcopenic dysphagia as a surrogate measure of swallowing-muscle strength. The present findings suggest that global swallowing muscle morphology and tongue-pressure performance provide complementary information and may represent distinct aspects of swallowing muscle health.
These observations align with current sarcopenia concepts in which muscle strength and muscle quantity are related yet distinct domains, each contributing unique clinical information [4, 58]. Recent consensus emphasize that low muscle mass alone should not be equated with sarcopenia; instead, it should be regarded as a clinically relevant sign, particularly in disease states, while sarcopenia requires the co-occurrence of low mass and low function [59]. A similar distinction may be relevant in sarcopenic dysphagia. Although tongue pressure has been incorporated into current diagnostic frameworks as a surrogate measure of swallowing-related muscle strength, Kunieda et al. found no significant association between tongue pressure and pharyngeal contractility measured using high-resolution manometry, suggesting that tongue pressure may not fully represent pharyngeal swallowing function and raising questions about its adequacy as a standalone marker of swallowing muscle function [60]. Similarly, Jones and Colletti reported that age-related declines in functional reserve previously described for tongue strength were not observed for pharyngeal swallowing pressures, further supporting the concept that different components of swallowing physiology may be affected independently [61]. Our findings reinforce this distinction by showing that variations in SwMM across patients did not correspond to meaningful differences in TS or TE.
SwMM still captured clinically meaningful structural variation across patient subgroups in our cohort. Older patients, women, and those at higher malnutrition risk had significantly smaller TCM areas, aligned with known determinants of muscle condition [10, 62,63,64]. Although these factors were not associated with tongue performance, this structural vulnerability remains clinically relevant given its links to treatment tolerance, frailty, and nutrition. Thus, our results demonstrate that SwMM provides valuable structural information that complements, but does not replace, functional measures. Consequently, treatment planning and patient monitoring may benefit from incorporating both structural and functional swallowing assessments, as impairment may be present in one domain despite preservation of the other.
The absence of correlation between SwMM and tongue pressure likely reflects fundamental physiological and anatomical differences between structural and functional metrics. Preserved SwMM with reduced TS output may reflect neuromuscular dysfunction or cancer-related fatigue, which can impair contractility before measurable atrophy occurs [65, 66]. Conversely, reduced SwMM with preserved TS may indicate reduced swallowing muscle reserve despite preserved tongue-pressure performance. This finding is consistent with the concept that swallowing tasks typically require only a fraction of maximal physiological capacity. Consequently, age-related reductions in maximal tongue strength may occur despite preservation of swallowing tongue pressures, reflecting a decline in physiological reserve rather than overt functional impairment [67, 68]. Moreover, studies of healthy aging indicate that swallowing function may remain clinically preserved despite age-related physiological changes, suggesting that compensatory mechanisms and neuromuscular adaptation may help maintain swallowing performance [61, 67]. Furthermore, tongue pressure is influenced by factors beyond muscle size alone, including muscle composition and the coordinated activation of multiple swallowing-related muscle groups [69]. Muscle quality, including fat infiltration, fibrosis, and metabolic alterations, plays a critical role in functional performance and often predicts weakness more strongly than cross-sectional area alone [70, 71]. Recent work further suggests that systemic indicators of muscle quality, such as phase angle measured via bioelectrical impedance analysis, are associated with tongue pressure in older adults [72]. Thus, structural and functional measures represent distinct physiological dimensions, neither of which can be assumed to infer the other, a distinction reflected in our findings.
Although an anatomical overlap exists between swallowing musculature represented within the TCM area and the muscles contributing to tongue-palate pressure, their physiological roles are not identical. The TCM area incorporates tongue musculature involved in pressure generation, including the intrinsic tongue muscles and genioglossus, but also captures additional swallowing-related muscles such as the mylohyoid–geniohyoid complex and the pharyngeal constrictors [67, 73]. This partial overlap justified examining their association; however, the observed dissociation indicates that shared anatomy does not equate to shared physiological behavior. Rather, SwMM captures global swallowing muscle mass, whereas tongue pressure reflects task-specific functional capacity. This mismatch in anatomical versus functional specificity likely contributed to our study results.
In addition, our CT-based SwMM measurement method quantifies cross-sectional area but does not capture muscle composition. Intramuscular fat infiltration, which is common in swallowing muscles, increases with age, and relates to declining tongue pressure, cannot be detected through area measurements alone [69, 70, 74]. Fat infiltration may impair contractility even when muscle size appears preserved.
Similarly, the lack of association between SwMM and TE is consistent with the understanding that endurance is more strongly modulated by neuromuscular efficiency, fatigue resistance, and metabolic capacity than muscle size. Evidence from tongue-pressure and fatigue studies suggests that endurance tasks reflect cumulative neuromuscular fatigue, motor unit recruitment efficiency, and task-specific load tolerance rather than anatomical bulk [68, 75,76,77]. In HNC patients, systemic inflammation and cancer-related fatigue likely exert greater influence on endurance performance than structural muscle mass, which may further explain the absence of correlation in our study.
Effect of Age and Nutritional Status
Older patients in our cohort exhibited lower SwMM (Supplementary Material 2), consistent with known age-related decline in skeletal muscle mass [4, 58]. However, unlike previous studies reporting age-related decline in tongue pressure in community-dwelling older adults [17, 68, 73, 78], we did not find differences in TS or TE in our HNC cohort. This finding is consistent with our overall observation that structural swallowing muscle measures and tongue-function measures may represent distinct physiological domains, such that age-related differences in muscle mass do not necessarily translate into measurable differences in tongue performance.
Malnutrition is a recognized risk factor for sarcopenia and sarcopenic dysphagia, and nutritional deficits accelerate muscle wasting and functional decline [10, 16, 63]. In line with this, in our study, patients at higher malnutrition risk demonstrated significantly smaller TCM areas (Supplementary Material 2), indicating structural vulnerability. However, their tongue performance did not differ across nutritional-risk groups, reinforcing the broader finding that structural muscle declines do not necessarily translate into functional impairment. Taken together, our results highlight that nutritional screening and tongue-function assessment provide distinct and complementary clinical information in HNC patients, rather than reflecting interchangeable aspects of the same physiological construct.
Strengths and Limitations
This study has some limitations that should be considered when interpreting the findings. First, the sample size was modest, which may have limited the statistical power to detect subtle associations between SwMM and tongue function; however, the observed effect sizes were small across all analyses, suggesting that larger sample sizes would likely only reveal relationships of limited clinical relevance. Second, CT-based SwMM quantifies muscle area but not muscle quality or composition; as mentioned above, fat infiltration, a known contributor to impaired contractility, cannot be captured on single-slice area measurement. Third, functional swallowing outcomes, such as oral intake and diet level, were not assessed. Consequently, the relationship between CT-based SwMM, tongue function, and overall swallowing performance could not be evaluated. Lastly, while the SwMM assessment method was recently developed, further external validation in larger cohorts would strengthen the robustness of this measurement approach.
Despite these limitations, this study presents several strengths. Its prospective design minimized selection and measurement bias. The minimal time interval between CT imaging and tongue function assessment (within two weeks) reduced the likelihood of temporal changes in muscle status influencing the results. Structural (CT) and functional (IOPI) measures were collected using established and standardized protocols, enhancing methodological rigor. Finally, the homogeneity of the cohort strengthens the internal validity of the findings by limiting variability from treatment- and disease-related factors.
Future Directions
The present findings highlight an important gap in the current diagnostic framework for sarcopenic dysphagia. Relying solely on tongue pressure as an indicator for swallowing muscle status may be insufficient. Future research should focus on validating imaging-based SwMM metrics across modalities, with the aim of reintegrating structural assessments into diagnostic pathways for sarcopenic dysphagia. In addition, beyond TS alone, future research should investigate how imaging-based SwMM relates to broader swallowing-function outcomes, including instrumental swallowing assessments such as Fiberoptic Endoscopic Evaluation of Swallowing (FEES) and Videofluoroscopic Swallow Study (VFSS), as well as the function of other key swallowing muscles, such as the pharyngeal constrictors and suprahyoid muscles, to capture swallowing physiology more comprehensively. Finally, imaging-based evaluation of muscle quality, particularly fat infiltration, should be incorporated, as these features may explain functional deficits that cannot be attributed to muscle size.





Comments (0)