
Remember me




This study was approved by the Salus University Institutional Review Board (IRB# K.Salmon11.14.23). All participants provided written informed consent before enrollment in accordance with the Declaration of Helsinki. The author declares no financial or non-financial conflicts of interest related to the design, implementation, or reporting of this study.
Experimental DesignThis randomized clinical trial investigated whether a six-week course of resistance-based perihyoid strengthening in healthy adults aged 18 and over produced measurable improvements in perihyoid strength. The primary aim was to determine whether the commonly used CTAR exercise improves indicators of perihyoid muscle strength, thereby contributing to the evidence base supporting its use in dysphagia rehabilitation. Secondary aims included comparing a traditional fixed-resistance CTAR approach (using a ball, per published protocols) with both a novel fixed-resistance and a novel progressive-resistance approach (using the Neckline Slimmer device). An additional aim was to explore whether a novel resistance device could serve as a feasible alternative to traditional CTAR equipment for perihyoid strengthening.
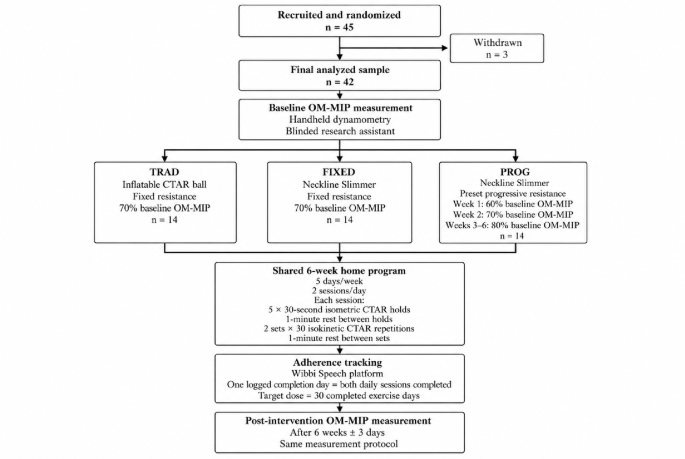
A pretest-posttest design with three intervention arms was employed; study flow, group allocation, and intervention dosage are summarized in Fig. 1. Participants were randomly assigned to one of three groups based on the resistance modality: (a) traditional fixed-resistance CTAR, (b) novel fixed-resistance CTAR, or (c) novel progressive-resistance CTAR. Dependent variables included pre- and post-intervention measures of perihyoid strength.
Fig. 1
Study flow and CTAR resistance training protocol by intervention group. Forty-five healthy adults were recruited and randomized, and 42 participants completed the six-week intervention and were included in the final analysis. Participants were assigned to traditional fixed-resistance CTAR using an inflatable ball (TRAD), fixed-resistance CTAR using the Neckline Slimmer device (FIXED), or preset progressive-resistance CTAR using the Neckline Slimmer device (PROG). TRAD and FIXED trained at 70% baseline OM-MIP, while PROG followed a baseline-derived progression schedule of 60% in Week 1, 70% in Week 2, and 80% in Weeks 3–6. All groups completed the same six-week home program, prescribed twice daily, five days per week. Each session included five 30-second isometric CTAR holds and two sets of 30 isokinetic CTAR repetitions. One logged completion day in the Wibbi Speech platform represented completion of both prescribed daily sessions. OM-MIP was measured at baseline and after completion of the intervention
A non-exercise control group was not included, as prior studies of CTAR interventions in healthy adults have not demonstrated spontaneous changes in perihyoid strength without training [9, 22]. Additionally, muscle strength in healthy individuals is generally stable over short intervals in the absence of targeted intervention [23,24,25,26].
Trial Registration and Sample SizeThis study was not prospectively registered. The study was conducted as a dissertation-based randomized clinical trial in healthy adults and was approved by the institutional review board before participant recruitment.
An a priori sample-size estimate was completed to determine the target enrollment for the three intervention groups. Because limited prior research had examined changes in perihyoid strength following CTAR-based resistance training, sample-size estimation was informed by available literature examining strength-based swallowing exercise outcomes in healthy adults. The study by Kraaijenga et al. was selected because its methodology most closely approximated the present protocol, including a six-week exercise program incorporating CTAR at a fixed level of resistance and pre- to post-training measurement of perihyoid/suprahyoid strength [27]. Raw pre- and post-training strength data from that study were used to calculate a mean change score and standard deviation. Values were converted from Newtons to kilograms force (kgF) to align with the OM-MIP measurement units used in the present study. The resulting estimated mean difference was 4.09 kgF with a standard deviation of 2.89 kgF.
Given the planned comparison across three intervention groups, a Bonferroni-adjusted alpha level of 0.017 was used. Using α = 0.017, β = 0.20, an estimated mean difference of 3.40 kgF, and a pooled standard deviation of 2.89 kgF, the target sample size was calculated as 14 participants per group. This yielded a total target sample size of 42 participants, providing 80% power to detect a 3.40 kgF difference in OM-MIP.
Participant RecruitmentA three-phase recruitment strategy was used to enroll healthy adults aged 18 years and older. Phase 1 targeted individuals affiliated with the institution and surrounding academic and clinical communities, including faculty, staff, alumni, clinical educators, externship supervisors, eligible students from neighboring academic institutions, and individuals connected to institutional clinical networks. If fewer than 50% of the target sample size had been reached within one month of enrollment opening, Phase 2 recruitment was initiated. Phase 2 expanded recruitment to the surrounding community through physical and digital postings on community bulletin boards, local libraries, supermarkets, educational institutions, and community centers. If fewer than 75% of the recruitment goal had been met within two months of enrollment opening, Phase 3 recruitment was initiated. Phase 3 included dissemination through professional organizations, discipline-specific interest groups, and relevant social media communities.
Participant EnrollmentStudy activities followed a hybrid model. All participants opted to complete the study introduction and informed consent process in person. Baseline and post-intervention perihyoid strength measurements were conducted on-site, while the six-week home-based exercise protocol was carried out independently by participants using provided materials and digital tools to track adherence.
Participants expressed interest in the study via phone, email, or by scanning a QR code linked to an online eligibility form. Eligibility was confirmed through direct screening, and participants were given the option to complete informed consent in person or virtually. Participants also needed to meet a predefined set of inclusion/exclusion criteria verified during screening before enrollment (see Table 1).
Table 1 Inclusion and Exclusion CriteriaA block randomization strategy was used to assign participants to one of three intervention groups: traditional fixed-resistance CTAR (TRAD), fixed-resistance CTAR using a novel device (FIXED), or progressive-resistance CTAR using the novel device (PROG). Group assignments were generated before participant recruitment using a computerized block randomization tool. Randomization was not stratified by baseline OM-MIP, age, sex, or other participant characteristics. A block size of three was used to maintain equal allocation across the three study groups, resulting in 14 participants per group. The research assistant responsible for screening and administering pre- and post-intervention OM-MIP measurements was blinded to group assignment; however, the principal investigator responsible for training participants on their assigned exercise protocol was not blinded.
Following consent, participants underwent a structured screening protocol conducted by a trained research assistant blinded to group assignment. The screening included a medical and swallowing history interview, administration of the Eating Assessment Tool (EAT-10), and an oral motor and cranial nerve examination. Exclusion criteria included any history of speech, swallowing, or neurologic impairment; structural asymmetries; or an EAT-10 score ≥ 3.
Pre- and Post-Intervention MeasuresThe primary outcome measure was perihyoid muscle strength, assessed using the OM-MIP protocol developed by Curtis et al. [18]. This protocol was selected for its ability to objectively quantify perihyoid strength via handheld dynamometry. Prior to OM-MIP, most investigations relied on sEMG, ultrasound, or indirect measures of swallowing kinematics and efficiency [9, 22, 36, 37, 40,41,42].
Participants completed OM-MIP testing at baseline and after the six-week intervention period. A trained, blinded research assistant performed all strength measurements using a Jamar handheld digital dynamometer. Participants were seated upright, leaning forward with elbows supported (on knees or a table, depending on mobility), and instructed to maintain a slightly open-mouth posture (2–5 mm interincisal distance), as verified using the TheraBite Range of Motion Scale. They were coached to apply maximal downward chin pressure without closing the mouth or allowing teeth to touch. Multiple trials were permitted until three consistent efforts within 10% of each other were achieved. The highest value among those was recorded as the OM-MIP value.
Additional data collected at the initial visit included demographic information (age, sex), medical and swallow history, and a self-reported physical activity level. The EAT-10 [28] was used to screen for dysphagia symptoms. Physical activity level was assessed using the International Physical Activity Questionnaire Short Form (IPAQ-SF) for participants under age 65 [29] or the International Physical Activity Questionnaire modified for the Elderly (IPAQ-E) for those 65 and older [30], with scores categorized using the IPAQ Automatic Report tool [31].
Intervention ProceduresGroup AssignmentParticipants were randomly assigned to one of three intervention groups using a block randomization method developed prior to recruitment [32]. The principal investigator (PI), who was responsible for training participants on their assigned exercise protocol, was not blinded to group assignment. Group 1 (TRAD) used a traditional fixed-resistance CTAR ball that matched the 12 cm inflatable ball described in Yoon et al. [9]. Groups 2 (FIXED) and 3 (PROG) used the Neckline Slimmer device, a spring-loaded resistance tool with interchangeable coiled springs labeled beginner (pink), intermediate (green), and advanced (black). The springs can be used individually or in combination to create seven distinct levels of resistance, allowing for intensity customization based on each participant’s strength.
Determination of Resistance LevelsFor participants in the TRAD group, the PI first measured the force generated during CTAR with the inflatable ball and calculated the target resistance at 70% of each participant’s baseline OM-MIP, based on published recommendations for moderate exercise intensity [33,34,35]. The ball’s inflation was then adjusted until the participant produced force output equivalent to 70% OM-MIP during chin tuck repetitions. In the FIXED group, the PI also calculated 70% of each participant’s baseline OM-MIP and selected the Neckline Slimmer spring or spring combination that most closely matched the calculated value. That spring configuration was then used for the full six-week protocol.
For the PROG group, resistance was assigned using a preset, baseline-derived progression schedule rather than recalibration based on repeated strength testing during the intervention period. Week 1 resistance was set at 60% of baseline OM-MIP. Resistance increased to 70% of baseline OM-MIP in Week 2 and to 80% of baseline OM-MIP for Weeks 3 through 6. Each participant was taught how to adjust the springs to match the prescribed weekly targets and was provided with written and video-based instructions. Because resistance levels were derived from baseline OM-MIP and were not recalibrated weekly using updated OM-MIP values, the PROG protocol represented a preset progressive ramp rather than a dynamically adjusted progressive-overload protocol.
Exercise Protocol TrainingAll participants were trained during Visit 1 on how to properly perform both isometric and isokinetic CTAR exercises using their assigned device. The PI demonstrated each task and guided the participant through a return demonstration, offering feedback to ensure proper technique. Each participant received a printed copy of the exercise program along with an electronic version, including video demonstrations, via the Wibbi Speech platform.
Participants were instructed to perform the exercise protocol twice daily, five days per week, for six weeks. Each session included five repetitions of 30-second isometric CTAR exercises with one minute of rest between repetitions, followed by two sets of 30 isokinetic CTAR repetitions. The isokinetic task involved tucking the chin for two seconds and releasing over the next two seconds, repeated consecutively. Rest between sets of isokinetic repetitions was set at one minute. Group 1 performed these tasks using the CTAR ball at 70% OM-MIP resistance. Group 2 used the Neckline Slimmer at a fixed resistance level equal to 70% OM-MIP. Group 3 used the Neckline Slimmer with resistance progressing from 60% to 80% OM-MIP across the six-week period.
Patient Tracking and AdherenceTo support adherence and reinforce proper execution of the exercises, all participants were enrolled in the Wibbi Speech online platform, which contained their customized home exercise program with embedded video instructions. Participants tracked exercise completion directly in the app or web interface. If a participant missed two consecutive days of recorded completion, the platform generated automated reminders via email and text message encouraging resumption of tracking and exercise. Participants were also encouraged to contact the PI with questions or concerns throughout the protocol period. The PI monitored exercise completion weekly using the Wibbi Speech dashboard.
Although the exercise protocol was prescribed twice daily, the Wibbi Speech platform allowed one completion entry per day. Participants were therefore instructed to log exercise completion only after completing both prescribed daily sessions. Because the protocol prescribed exercise completion five days per week for six weeks, the target dose was 30 completed exercise days. Adherence was calculated as the number of logged completed exercise days divided by 30 and expressed as a percentage. Weekly adherence was capped at five completed days to reflect the prescribed weekly dose.
Visit 2 ProceduresThe second study visit was scheduled approximately six weeks (± 3 days) after protocol initiation. During this visit, the blinded research assistant administered the post-intervention OM-MIP measurement using the same procedures as at baseline. These data were used to evaluate changes in perihyoid strength following the assigned intervention.
Statistical AnalysisAll statistical analyses were conducted using IBM SPSS Statistics. Descriptive statistics were calculated for participant demographic and baseline variables, including age, gender, ethnicity/race, EAT-10 score, and self-reported physical activity level. Measures of central tendency and dispersion were reported for continuous variables, while frequencies and percentages were reported for categorical variables.
Normality of OM-MIP data was evaluated using comparison of mean and median values, visual inspection of histograms, and calculation of Shapiro-Wilk test statistics, skewness, and kurtosis. For within-group analyses, change in perihyoid strength from baseline to post-intervention was examined separately for each group. The original analytic plan specified paired t-tests if data were normally distributed; however, because assumptions of normality were not met, Wilcoxon Signed-Rank tests were used to compare pre- and post-intervention medians within each group. Effect sizes for Wilcoxon Signed-Rank tests were calculated as r = |Z|/√N.
For between-group comparisons, the original analytic plan specified one-way analysis of variance (ANOVA) to evaluate differences in mean change scores across the three groups if normality assumptions were met, with Bonferroni-corrected post hoc comparisons when appropriate. Because the outcome data were not normally distributed, the Kruskal-Wallis test was used to compare median OM-MIP change scores across groups. If statistically significant group differences were identified, post hoc pairwise comparisons were planned using Dunn’s test with Bonferroni adjustment.
Adherence was analyzed descriptively and as a potential covariate. Adherence percentage was summarized overall and by intervention group using measures of central tendency and dispersion. Because adherence data were not normally distributed, Kruskal-Wallis testing was used to compare adherence percentage across groups. To examine whether adherence influenced post-intervention strength outcomes, an analysis of covariance (ANCOVA) was conducted with post-intervention OM-MIP as the dependent variable, intervention group as the fixed factor, and baseline OM-MIP and adherence percentage as covariates. Statistical significance was set at α = 0.05 for primary analyses.
Comments (0)