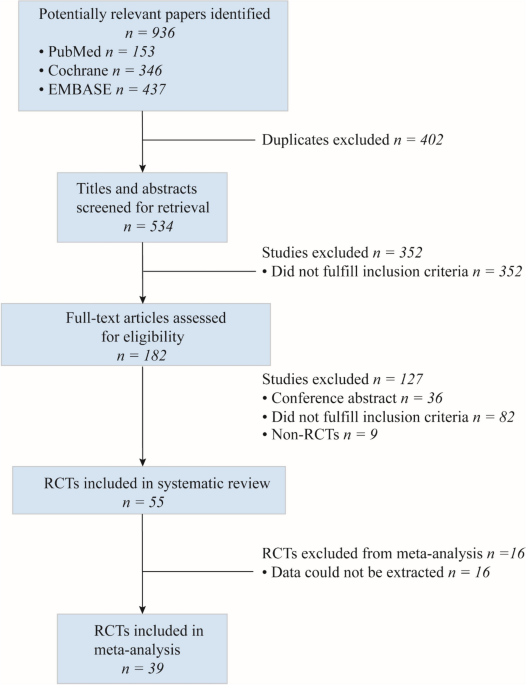
A total of 39 studies were included in this meta-analysis. The results indicated that electrical stimulation had a certain beneficial effect on improving swallowing function in patients with post-stroke dysphagia; however, no significant improvement was observed in physiological swallowing parameters (as measured by the PTT and OTT scales), suggesting that functional improvement may not directly equate to physiological recovery. Subgroup analyses showed that increasing the daily stimulation duration or total treatment length did not lead to better clinical outcomes, and the effects of different electrical stimulation modalities varied across treatment periods. Subgroup analysis based on the proportion of female participants revealed no statistically significant influence of female proportion on treatment effects; nevertheless, given the small sample size in this subgroup, these findings should be interpreted as exploratory.
Our findings confirm that electrical stimulation has a therapeutic effect on post-stroke dysphagia, which is consistent with the results of several previous meta-analyses [54,55,56,57]. Notably, among the primary outcome measures, electrical stimulation showed a more pronounced short-term effect when measured with the DOSS, whereas the opposite pattern was observed with the FOIS (i.e., long-term improvement). This discrepancy may be partially attributable to differences in the assessment dimensions of the two scales: the DOSS focuses on the degree of impairment in swallowing physiology as observed by clinicians through instrumental examinations (e.g., video fluoroscopy or endoscopic evaluation) and is thus more sensitive to short-term physiological changes; in contrast, the FOIS reflects the patient’s actual functional oral intake capacity and level of dependence, which often requires a longer intervention and rehabilitation period to achieve improvement.
Furthermore, there is a marked imbalance in the distribution of electrical stimulation types across studies using the two scales. Among the studies that adopted the DOSS as an outcome measure, 71% (5 out of 7) reported on the effects of tDCS for post‑stroke dysphagia. In contrast, among the studies that used the FOIS, 85% (11 out of 13) reported on NMES for post‑stroke dysphagia. This imbalance may influence the observed differences in short‑term versus long‑term effects, an interpretation that is supported by subsequent subgroup analyses based on the type of electrical stimulation. Nevertheless, these interpretations are post‑hoc in nature and are limited by the number of included studies and the quality of the original research; therefore, the conclusions should be treated with caution.
For secondary outcomes, no significant benefits were demonstrated in PTT or OTT. Post-stroke dysphagia manifests as oral phase alterations, prolonged pharyngeal transit time, and delayed swallowing response latency [58]. One meta-analysis indicated that while swallowing function improvement correlates with tDCS stimulation sites, stimulating lesioned areas fails to ameliorate oral/pharyngeal transit times [13]. An RCT demonstrated no significant differences in post-stroke OTT/PTT improvement between tDCS treatment and control groups [46]. Following NMES stimulation, swallowing coordination improved with reduced OTT/PTT values, but these changes lacked statistical significance [35]. Krueger et al. [59] previously demonstrated that lesions in the left hemisphere are associated with oral phase dysfunction, whereas right hemisphere lesions result in pharyngeal phase abnormalities. Therefore, further research is warranted to investigate the influence of lesion location and electrical stimulation on swallowing transit time.
The functional improvements (DOSS, FOIS) contrast with the lack of significant changes in physiological measures (OTT, PTT). The functional scales DOSS and FOIS reflect overall clinical efficacy and are more dependent on clinical observation and patient performance, whereas OTT and PTT are objective, quantifiable physiological and kinematic measures. Electrical stimulation may improve swallowing safety by enhancing coordination rather than simply increasing strength, thus functional improvement can occur without significant changes in physiological parameters. On the other hand, some patients may maintain high FOIS and DOSS scores through compensatory strategies (e.g., multiple swallows, postural adjustments), even while PTT and OTT remain significantly prolonged, indicating a potential ongoing risk of aspiration. Importantly, in our study, the number of studies reporting OTT and PTT as outcomes was small, and among the included studies, stroke type, lesion location, and stimulation site were not standardized. Therefore, the above findings should be considered exploratory.
Notably, among the included studies, only two reported alterations in sEMG of the swallowing muscles. These studies indicated that NMES combined with conventional swallowing therapy enhanced the maximum amplitude of sEMG signals in these muscles, whereas NMES alone produced no significant changes in sEMG parameters. This pattern likely arises because the vast majority of NMES trials incorporate swallowing training, constituting a multimodal intervention. Swallowing-related muscles are primarily composed of type I and type II muscle fibers. Type II fibers are smaller and less polarizable than type I fibers [60]. During the application of NMES, type II fibers are preferentially activated. In contrast, conventional rehabilitation training primarily recruits type I fibers [61]. The concurrent application of NMES and rehabilitation training facilitates the simultaneous activation of both type I and type II fibers, enabling the lingual and pharyngeal muscle groups to generate greater contractile force. Furthermore, electrical stimulation triggers the release of vasoactive peptides, inducing local vasodilation and thereby improving blood circulation at the injury site [62]. This enhanced perfusion accelerates nerve regeneration and repair, promoting accurate axonal projection along regenerative pathways towards target organs, as well as axonal regrowth and myelin maturation [63]. These processes collectively facilitate functional recovery and reorganization within the cerebral cortex and associated neural connections and pathways [64, 65]. The above mechanisms are currently based primarily on basic research and indirect evidence, and require direct validation in future studies. These findings suggest that integrating electrical stimulation with rehabilitation training may offer superior benefits for improving post-stroke swallowing function in clinical practice.
In the subgroup analysis based on electrical stimulation type, NMES demonstrated significantly more pronounced long-term effects compared to short-term effects on the FOIS scale outcome. This finding is consistent with one meta-analysis [66]. Notably, the NMES treatment protocols in the included studies generally involved longer durations (>3 weeks), whereas most tDCS studies utilized shorter treatment periods (<3 weeks). The superior long-term efficacy of NMES may be associated with its underlying mechanism (as previously described, involving muscle-level adaptations) and these prolonged treatment protocols. In contrast, the effects of tDCS were evident immediately after the intervention and persisted. One meta-analysis observed medium- to long-term effects of tDCS, with significant improvements attainable after just four treatment sessions [13]. This likely relates to tDCS directly stimulating and activating cortical/subcortical swallowing centers. The short- and long-term effects of tDCS involve distinct mechanisms, including non-synaptic mechanisms leading to resting membrane potential depolarization and N-methyl-D-aspartate (NMDA)-receptor-dependent mechanisms [67, 68]. Relevant studies indicate that the durable effects of tDCS can extend beyond 3 months [46]. Furthermore, another study reported significantly greater improvement in swallowing function in the active tDCS group compared to the sham group among 60 acute stroke patients with dysphagia receiving tDCS stimulation over four consecutive days [32]. These findings are also consistent with the results of our meta-analysis.
In additional subgroup analyses, we observed that various forms of electrical stimulation (tCDS, NMES, ES) demonstrated significantly greater efficacy within the subgroup receiving a total treatment duration of ≤3 weeks. Furthermore, in the subgroup analysis of daily stimulation time, the subgroup receiving daily electrical stimulation sessions lasting <30 minutes yielded larger effect sizes. These findings align with previous research. A meta-analysis incorporating 20 randomized controlled trials suggested that for swallowing recovery in stroke patients, anodal tDCS at 20 minutes and 1.4 mA may be the most beneficial regimen; increasing either the stimulation duration or intensity of tDCS did not enhance its efficacy for post-stroke dysphagia [69]. Another meta-analysis reported a lack of positive correlation between tDCS treatment effects and stimulation intensity [12]. Similarly, a meta-analysis on NMES for post-stroke dysphagia indicated that treatment courses of 4 weeks or shorter might achieve more satisfactory clinical outcomes compared to courses exceeding 4 weeks [70]. Prior research suggests that greater stimulation does not necessarily confer superior benefits. Post-stroke, particularly in the early phase, excessive NMDA receptor activation could exert detrimental effects [68]. Other studies have documented a ceiling effect, where prolonged stimulation can ultimately lead to a reduction in motor evoked potential (MEP) amplitude [71, 72]. Crucially, most primary swallowing muscles contain a high proportion of type II muscle fibers. While type II fibers generate higher force, they fatigue more rapidly [73]. NMES systems preferentially recruit these type II fibers; consequently, prolonged stimulation may induce muscle fatigue, resulting in diminished muscular endurance, inadequate force generation, and potentially increased risk of aspiration/penetration. This physiological basis supports our observation that longer stimulation durations may yield smaller effects or potentially adverse outcomes. Notably, a significant lack of consensus exists regarding optimal stimulation parameters (including intensity and duration) for tDCS, NMES, and PES [10, 13].
This finding is counterintuitive, as longer stimulation durations are generally thought to yield better outcomes. Potential explanations include: short‑term, high‑frequency intensive stimulation may be more conducive to neural remodeling in the subacute phase; prolonged treatment may be associated with patient fatigue or reduced adherence, thereby diluting the treatment effect; and there may be confounding factors (e.g., stroke severity) related to the distribution of intervention durations across the included studies. However, it must be acknowledged that the current data cannot distinguish among these possibilities. Furthermore, the distribution of treatment durations differs across stimulation types: most NMES trials had a course of >3 weeks, whereas most tDCS trials had a course of <3 weeks, which may confound the effects of "stimulation type" and "treatment duration." Therefore, the conclusion that shorter stimulation durations are more beneficial should be considered hypothesis‑generating rather than a definitive dose‑response relationship.
In our study, we performed, for the first time, subgroup analyses based on the proportion of female participants and found no significant effect of female proportion on the treatment efficacy of electrical stimulation. However, given the lack of clear biological or clinical theories supporting an association between sex and the response to electrical stimulation, as well as the small number of studies and insufficient statistical power in each subgroup, these findings should be considered hypothesis‑generating rather than conclusive.
Our findings indicate that electrical stimulation contributes to the amelioration of post-stroke dysphagia, potentially through the following mechanisms. tDCS is a non-invasive technique that modulates cortical excitability via two electrodes. Anodal stimulation increases cortical excitability by depolarizing resting membrane potentials, while cathodal stimulation decreases cortical excitability (and may promote functional reorganization) by hyperpolarizing resting membrane potentials [74]. The pharyngeal cortical motor area is a key region involved in swallowing. According to research by Dipesh H. Vasant et al., when applied to the pharyngeal motor cortex, tDCS may enhance the integration of functional information within the swallowing cortical network and strengthen task-related synaptic connectivity within this region [75]. Concerning NMES, which targets the peripheral neuromuscular system, it is postulated to enhance laryngeal elevation, restore motor function in weakened muscles, counteract muscular atrophy, heighten sensory awareness, and facilitate muscle contraction. Neuroplasticity research has demonstrated that cortical representations can be modified by sensory and motor input, suggesting that NMES may improve swallowing partly through inducing cortical reorganization. Compared to volitional contraction, NMES recruits a greater number of remote motor units and has the potential to elicit greater gains in muscle strength than motor training alone [76, 77]. Although these explanations are reasonably plausible, no direct data currently support that the effects observed in this meta-analysis are indeed mediated through these pathways. Therefore, the above mechanistic discussion should be considered speculative and awaits direct validation in future studies using neurophysiological or histological approaches.
Limitations
Finally, several limitations of this study must be acknowledged. First, although 39 studies were included, the sample sizes for specific subgroup analyses remained small, resulting in insufficient statistical power; thus, the subgroup findings should be explicitly defined as exploratory (including a post-hoc exploratory analysis based on female proportion, which lacked a pre-specified hypothesis and strong theoretical support). Second, in most included trials, both the experimental and control groups received conventional swallowing rehabilitation training, which is the current standard of care; therefore, the independent effect of electrical stimulation could not be completely isolated. Third, substantial heterogeneity existed across studies with respect to stroke type (ischemic/hemorrhagic), lesion severity, and time from stroke onset to treatment (acute/subacute/chronic phase), limiting the generalizability of the conclusions. Fourth, the electrical stimulation parameters (electrode placement, frequency, intensity, duration per session, and total treatment course) varied considerably across studies, and pooling these data may have masked true effects. Fifth, most primary studies did not clearly report the methods of randomization sequence generation and allocation concealment, introducing risks of selection and performance bias. Sixth, the follow-up durations were inconsistent across studies, undermining the reliability of comparisons of long-term efficacy. Seventh, although we performed a pooled analysis of different electrical stimulation types and subsequently supplemented it with subgroup analyses, comparisons between subgroups may still be subject to residual confounding. Therefore, the above findings should be considered exploratory. Future high-quality, large-scale, standardized randomized controlled trials are needed to validate the optimal regimen of electrical stimulation for post-stroke dysphagia.





Comments (0)