
Remember me




A total of 154 responses were received. Fifty-one responses were excluded due to insufficient data for extraction, as they provided demographic data only with no clinical data, leaving 103 responses for analysis. All responses related to feeding infants hospitalised on the neonatal unit.
Quantitative AnalysisComplete data were available for 64 responses, with partial data provided by an additional 39. Data are therefore reported on a per-question basis, using the number of respondents who answered each item, as a result the (n) varies across questions.
DemographicsThe characteristics of respondents are presented in Table 1. 59% of respondents worked in a Neonatal Intensive Care Unit (Level 3), 33% worked in a Local Neonatal Unit (Level 2) and 8% worked in a Special Care Baby Unit (Level 1) (n = 103).
Table 1 Demographics of respondentsGuidelines58% of respondents followed no guidelines when making decisions regarding oral feeding on nCPAP or HFNC, and 42% did or had guidelines in development (n = 83).
Oral Feeding AssessmentWhen asked who is involved in carrying out oral feeding assessments on the neonatal unit, respondents (n = 81) were able to select multiple options, with most choosing SLTs (90%) as part of the assessment team. The most reported reasons for assessing an infant’s oral feeding readiness were ‘prior to commencing oral feeds’ (63%) and ‘at around 32–34 weeks’ gestation’ (52%) (n = 81). When asked which oral feeding observation assessment tools they use, 40% of respondents reported using the UNICEF Breastfeeding Assessment Tool. A subgroup analysis showed that a similar percentage of SLTs (n = 44; 41%), nurses (n = 19; 38%) and doctors (n = 18, 39%) used the UNICEF Breastfeeding Assessment Tool. Other assessment tools used were the Infant Driven Feeding Scale (13%), Neonatal Oral-Motor Assessment Scale (NOMAS) (9%), Non-nutritive Sucking (NNS) Scoring System (7%), Early Feeding Skills (EFS) Assessment (6%) and the Neonatal Eating Assessment Tool (NeoEAT) (6%). 12% of respondents reported the use of ‘other’ assessment tools and 10% reported using ‘no’ assessment tools. When asked what areas they consider when assessing an infant’s oral feeding 80% or more of respondents (n = 78) said they ‘always’ consider these five things; readiness cues (88%), infant state of alertness (86%), safety of oral feeding (86%), signs of distress (81%) and physiological state at rest (80%). The main indicators respondents use to determine if an infant is not tolerating an oral feed (n = 81) are behavioural cues (74%), changes in state (71%), organisation of suck-swallow-breathe (71%) and clinical signs of aspiration or laryngeal penetration (70%). In total, 63% (n = 81) of respondents said they used instrumental evaluation on their unit, including cervical auscultation (36%), pulse oximetry (34%), video-fluoroscopy swallow study (25%) and fibreoptic endoscopic evaluation of swallowing (8%). These figures reflect overall availability and use of instrumental evaluation on neonatal units, rather than use specific to infants receiving oral feeding on NIV.
Terminology and DefinitionsRespondents (n = 44) were asked, when observed, how often they use specific terms to indicate clinical signs of aspiration or laryngeal penetration (Table 2). Six terms were identified that at least 55% of respondents reported ‘always’ using when observing an infant: increased respiratory rate (61%), work of breathing (55%), oxygen desaturation (59%), disorganised suck-swallow-breath pattern (57%), wet breathing (55%) and bradycardia (55%). Fifty-eight respondents reported on the definition of HFNC. HFNC was defined as >2L/min (43%); >3L/min (36%); >1L/min (14%); L/kg (2%) and ‘other’ (5%).
Table 2 Frequency of terms used to indicate clinical signs of aspiration or laryngeal penetrationReported use of nCPAP and HFNC94% (n = 80) of respondents reported that they use nCPAP on their unit and 100% (n = 72) reported that they use HFNC.
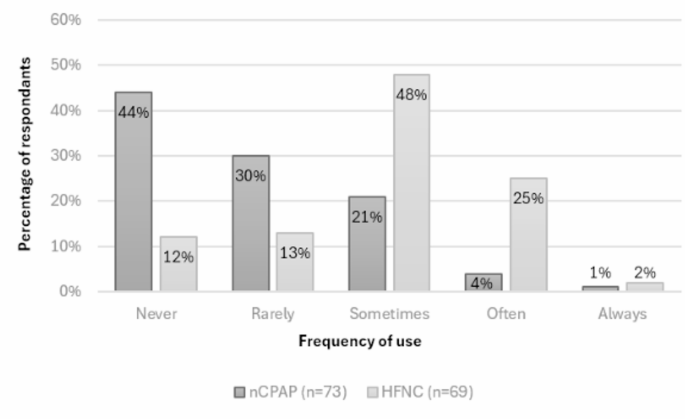
Oral Feeding on nCPAP and HFNCWhen asked if infants who receive nCPAP feed orally, most respondents said never (45%); 30% said rarely; 21% said sometimes; 3% said often; and 1% said always (n = 73). Regarding HFNC, most respondents (48%) sometimes fed; 23% often fed; 1% always fed and 28% never or rarely fed (n = 69) (Fig. 1).
Fig. 1
Frequency of oral feeding on nCPAP and HFNC
Clinical Factors for Orally Feeding on nCPAP and HFNCRespondents were asked to select which clinical factors they consider when deciding whether to orally feed an infant on nCPAP (n = 57) or HFNC (n = 34) (Table 3). Six factors emerged as the most consistently considered, with 65–81% of respondents reporting that they ‘always’ take them into account: medical complexity, gestational age, flow rate, feeding readiness cues, route of oral feeding and pre-existing feeding difficulties. All six factors are also referenced in the Royal College of Speech and Language Therapists (RCSLT) position paper: Feeding on Non-invasive Respiratory Support [22].
Table 3 Frequency of clinical factors considered when deciding to orally feed an infant on HFNC/nCPAPStrategies used During oral Feeding on nCPAP and HFNCWhen respondents were asked about the strategies they use when orally feeding infants on nCPAP (n = 31) or HFNC (n = 54) three approaches emerged as being the most consistently implemented. Between 57% and 80% of respondents reported ‘always’ using the following strategies: monitoring physiological state; oral preparation (e.g. non-nutritive sucking practice) and monitoring for clinical signs of aspiration. Other strategies are outlined in Table 4.
Table 4 Frequency of strategies when orally feeding an infant on HFNC/nCPAPWho Decides When to Orally Feed Infants on nCPAP or HFNCWhen asked who is involved in deciding when oral feeding is initiated for infants receiving nCPAP and HFNC the most common response was medical staff (neonatology) (nCPAP 56%; HFNC 62%), followed by SLT (nCPAP 42%; HFNC 53%), nursing staff (nCPAP 38%; HFNC 48%), parent/carer (nCPAP 14%; HFNC 20%), Infant Feeding Lead (nCPAP 14%; HFNC 18%), medical staff (respiratory) (nCPAP 6%; HFNC 8%), Lactation Consultant (nCPAP 3%; HFNC 2%) and other (nCPAP 15%; HFNC 2%) (n = 78). In the UK, the Infant Feeding Lead is a recognised role within the National Health Service, responsible for supporting complex feeding decisions, providing staff training, and promoting high-quality feeding practices. Respondents could select more than one option for this question, so percentages do not sum to 100%.
How are Infants Orally Fed on nCPAP or HFNCRespondents (n = 78) were asked which feeding methods they used to feed infants on nCPAP and HFNC. Respondents could select multiple responses. The most common response for nCPAP was ‘infants are not orally fed when receiving nCPAP’ (31%) (HFNC; 8%), the most common response for HFNC was ‘breastfeeding’ (56%) (nCPAP 28%). Other methods reported where ‘bottle feeding’ (nCPAP 18%; HFNC 49%), ‘cup feeding’ (nCPAP 1%; HFNC 5%), ‘syringe feeding’ (nCPAP 5%; HFNC 6%) and ‘other’ (nCPAP 5%; HFNC 6%).
No Oral Feeding on nCPAP and HFNCRespondents (n = 78) were asked why infants may not be orally fed on nCPAP or HFNC. Selecting from a list provided, the most common reason for both nCPAP and HFNC was the ‘aspiration risk is unclear’ (nCPAP 31%; HFNC 9%). Other reasons included ‘medical team do not allow it’ (nCPAP 22%; HFNC 3%), ‘infants are too young to commence oral feeding’ (nCPAP 12%; HFNC 5%), ‘team doesn’t have sufficient expertise at this current point in time’ (nCPAP 6%; HFNC 4%) and ‘other’ (nCPAP 19%; HFNC 9%).
Staff OpinionsThe final survey question asked how often respondents agreed with specific professional groups regarding oral feeding practices for infants on nCPAP or HFNC. Overall, respondents most commonly reported that they ‘always’ agreed with SLTs (nCPAP: 51%, n = 57; HFNC: 47%, n = 58). However, this pattern was largely driven by SLTs’ own responses: among SLTs (n = 29), 90% reported ‘always’ agreeing with SLTs for nCPAP and 83% for HFNC, indicating strong intra-professional agreement. In contrast, smaller proportions of nurses (n = 12; nCPAP 25%, HFNC 15%) and doctors (n = 16; nCPAP 0%, HFNC 6%) reported ‘always’ agreeing with SLTs. Taken together, these findings suggest that while SLTs demonstrate high internal agreement, this is not reflected across the wider multidisciplinary team, indicating limited inter-professional agreement on oral feeding practices for infants on NIV.”
Qualitative AnalysisWhere free text responses were minimal (e.g. 1–3 words) content analysis was used with a frequency count to quantify how often particular words, items, or ideas appeared within each theme or subtheme, providing an indication of their importance in the dataset (Table 5). Respondent’s comments focused on documentation, approaches, clinical considerations, multidisciplinary input, risk, assessment, pre-feeding, dis/agreement within teams, timing of feeding and methods.
For more detailed responses, thematic analysis was used. From this, five main themes and ten subthemes were identified. These are presented in Tables 6, 7, 8 and 9 and appear again in the headings used to structure the section that follows. Excerpts from the transcripts are provided within the tables and demonstrate content from all themes and subthemes.
Table 5 Frequency count for themes and subthemes from content analysisTheme 1: Decision-making when Orally Feeding Infants on Non-invasive VentilationRespondents discussed the variation in consultant decision-making and the variable influence the SLT assessment has on decision-making for oral feeding infants on NIV (Table 6). It’s possible that the lack of guidelines (58% of respondents reported having no guidelines for orally feeding infants on nCPAP or HFNC, n = 83) has contributed to this variation in practice. Decision-making on a ‘case-by-case’ basis, considering the infant’s ‘readiness’ to feed was also noted as important in the decision-making process.
Table 6 Decision-making when orally feeding infants on NIVTheme 2: Risk of Aspiration Suggested by the Evidence-baseBoth the frequency count (n = 22) and thematic analysis identified risk of aspiration as a key challenge. Respondents recognised the ‘risk of aspiration for oral feeds based on research’. However, acknowledged that the research was ‘limited’ (Table 7). The lack of evidence and clarity regarding decision-making for orally feeding infants on NIV is repeatedly cited in the literature and may explain the ‘varying agreement of healthcare professionals’ identified in the frequency count (Table 5) as well as the conflict referred to in theme 4.
Theme 3: Local Speech and Language Therapy team don’t allow itThematic analysis indicated that some respondents, primarily medical staff, perceived local Speech and Language Therapy teams as not allowing oral feeding for infants receiving NIV. These respondents felt that SLTs tended to overstate the risk of aspiration, which they believed contributed to a more restrictive approach to oral feeding.
Table 7 Risk of aspiration suggested by the evidence-base and local SLT team don’t allow itTheme 4: Continuum of Conflict Related to Orally Feeding Infants on Non-invasive VentilationA continuum of conflict, relating to orally feeding infants on NIV, was established from the data. Some respondents (n = 17) commented that healthcare professionals agree while others (n = 13) reported a difference of opinion. Variation in opinion was also highlighted in the thematic analysis with some respondents referring to decisions being ‘discussed mindfully as an MDT’ and others commenting that recommendations and advice were contradictory (Table 8). Disagreement was also noted within the same discipline as one respondent stated, “It depends which medical staff or nursing staff are on shift as they all hold different opinions about oral feeding on HFNC” (Table 8).
Table 8 Continuum of conflict related to orally feeding infants on NIVTheme 5: Parental Experience of Feeding Decision-making‘Parents’ were mentioned 14 times throughout the data (Table 5), in relation to parental experience in decision making and parental attunement with their baby. SLTs described a lack of parental input with parents being “pushed to feed” and “rarely being included in decision-making” (Table 9). All disciplines (nurses, medical staff and SLTs) agreed that parents were in tune with their baby and play an important part in the feeding journey.
Table 9 Parental experience of feeding decision-making
Comments (0)