
Remember me



A budget impact model was developed in Microsoft Excel following International Society for Pharmacoeconomics and Outcomes Research (ISPOR) guidelines [22]. The model employed a 10-year time horizon and simulated two parallel cohorts of one million US adults with T2D: one receiving standard of care (SoC) monitoring alone, and one receiving SoC plus PromarkerD testing with risk-stratified management. The model simulated a base-case cohort of 1 million US adults with T2D to enable transparent estimation of clinical and economic outcomes and facilitate proportional scaling to alternative populations. Results are presented both for this one-million-person T2D cohort and translated to a hypothetical health plan population with the estimated impact on national estimates also presented.
For contextualization within a health plan setting, national epidemiologic data from 2023 indicate that approximately 28.8 million US adults (10.8%) have diagnosed diabetes, of whom 90–95% are estimated to have T2D, corresponding to ~9.7–10.2% of the adult population [23]. A T2D prevalence of 10% was applied for translation purposes. Accordingly, in a hypothetical one-million-member health plan, ~100,000 individuals would be expected to have diagnosed T2D. Model outputs were proportionally scaled to this population. At the national level, approximately 26–28 million US adults are estimated to have diagnosed T2D [23]. Model results were similarly extrapolated to this population to provide contextual estimates of potential aggregate economic impact. These extrapolations assume proportional scalability of costs and outcomes and are intended to illustrate magnitude rather than provide precise national forecasts.
The analysis adopted a US healthcare payer perspective, incorporating direct medical costs associated with CKD and ESRD management, PromarkerD testing, and SGLT2i treatment. All model inputs were derived from published literature and are summarized in Table 1 and the Electronic Supplementary Material (ESM) Fig. 1 and Tables 1, 2, 3. Model inputs were identified through targeted literature review of PubMed and guideline documents focusing on US CKD epidemiology, renal outcome trials, and healthcare cost studies relevant to T2D populations. Preference was given to large observational cohorts and RCTs reporting KDIGO stage-specific outcomes. Where multiple sources existed, the most recent US-representative dataset was selected with confidence intervals or alternative data sources explored in sensitivity analyses.
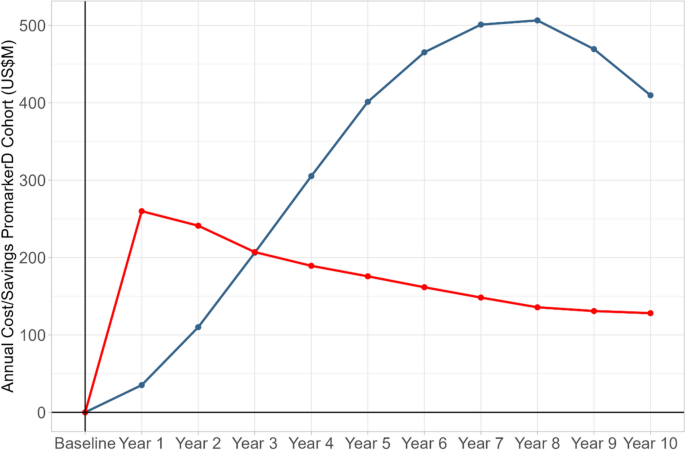
Fig. 1
Annual intervention costs with PromarkerD (red line) versus annual savings from delayed CKD progression (blue line). US$M, million USD; CKD, chronic kidney disease
Table 2 Economic impact summary (10-year NPV, million USD per million population)Table 3. Sensitivity analysis results2.2 Study PopulationThe initial study population was stratified according to KDIGO-based CKD staging [8] using US national population estimates [24] (Supplementary Table 1A). The simulated cohort characteristics reflected real-world demographics: mean age 63.9 years, 52% male, with an average diabetes duration of 10.7 years. Prevalent comorbidities included hypertension (74%), retinopathy (22%), and coronary heart disease (12%). Ethnic distribution comprised 22% Mexican Americans, 38% non-Hispanic white Americans, and 27% non-Hispanic Black Americans [24]. CKD severity was categorized by eGFR (stages G1–G5) and albuminuria (categories A1–A3) according to KDIGO classification [8]. Owing to small numbers in advanced stages, G3b, G4, and G5 were not further stratified by albuminuria. To distinguish between patients with advanced kidney dysfunction (eGFR < 15 mL/min/1.73 m2) and those receiving RRT, stage G5 (no RRT) and ESRD (with RRT) were modeled separately. The model assumed a closed cohort with no new patient entry and death as the only absorbing end-state.
2.3 Standard of Care Model2.3.1 Annual CKD Progression Probabilities and SGLT2i UseAnnual CKD progression probabilities were derived from Nichols et al. [25] and represent the total 1-year probability of transitioning out of a given KDIGO category, including progression to more advanced CKD stages and all-cause mortality (Supplementary Table 1B; Supplementary Fig. 1). For example, the 7.5% annual progression probability for G1A1 reflects the sum of transitions from no CKD to moderate CKD (5.7%), advanced CKD (0.3%), ESRD (0.1%), and death (1.4%). Updated 1-year probabilities were obtained directly from the authors of Nichols et al. [25] owing to errors identified in the originally published supplementary figure and are presented in Supplementary Fig. 1. For advanced CKD stages (G3b–G5), transition probabilities were derived by aggregating published estimates across albuminuria strata, as the source data report outcomes separately by eGFR and albuminuria categories. Where direct transitions to ESRD were not available, ESRD risk was estimated using an incidence-based approach combined with hazard ratios from the CKD Prognosis Consortium [26]. Mortality was incorporated across all CKD stages. To account for competing risks, transitions to ESRD and death were modeled as mutually exclusive within each cycle.
A Markov process simulated annual transitions between KDIGO stages, with patient distributions updated annually on the basis of net transitions between categories. Transitions were modeled on the basis of eGFR decline; movement between albuminuria categories was not modeled owing to data limitations and the non-independence of eGFR and albuminuria changes. Death was modeled from all KDIGO stages. ESRD with initiation of RRT included 12% peritoneal dialysis, 85% hemodialysis, and 3% kidney transplantation [3]. The 5-year survival rate for ESRD was 25% [1]. Assuming exponential survival, this corresponds to an annual mortality rate of 1 − (0.25)1/5, or 24.2%, which was applied in the model.
Background SGLT2i use was based on 2020 US Centers for Disease Control and Prevention (CDC) prescription data: 18% for G1–G2 stages and 16% for stages G3a–G3b [27]. No additional pharmacologic or lifestyle interventions were assumed in the SoC model. The effectiveness of SGLT2i therapy was informed by hazard ratios from the EMPA-REG OUTCOME trial for the renal outcome of doubling of serum creatinine, initiation of RRT, or renal death, as this endpoint closely reflects clinically meaningful CKD progression [28]. For each KDIGO risk category, hazard ratios were applied to baseline progression probabilities (i.e., 1 – (1 – baseline probability)hazard ratio) (Supplementary Table 1C). This transformation assumes proportional hazards and converts relative risk reductions into absolute transition probabilities under a constant hazard assumption.
2.3.2 Annual Care CostsAnnual all-cause healthcare costs by KDIGO stage ranged from $29,993 (G1) to $119,944 (G5), covering inpatient, outpatient, emergency department, pharmacy, and skilled nursing services (Supplementary Table 4) [6]. ESRD-related costs included $172,788 annually for dialysis [29] and $9179 annually for transplant care [30], with an initial transplant procedure cost of $442,500 [31]. Death was assigned a one-time cost of $12,605 [5]. Monthly SGLT2i costs ranged from $450 to $800 [32], with a baseline modeled average of $600 per month ($7300 annually) (Table 1). The cost for generic SGLT2i was assumed from the start of the model given the recent FDA approval [33]. Following patent expiry, prices were reduced according to published post-patent erosion trends, with progressive annual reductions thereafter, reaching approximately $1314 annually by year 10 [34, 35] (Table 1).
2.4 PromarkerD Model2.4.1 CKD Progression and SGLT2i UseIndividuals with eGFR ≥ 30 mL/min/1.73 m2 (KDIGO G1-G3b) were eligible for PromarkerD testing. On the basis of data from the Fremantle Diabetes Study [12], patients were stratified as low-, moderate-, or high-risk for kidney function decline. Multiple randomized, placebo-controlled trials and prespecified or post hoc renal analyses demonstrate that SGLT2i therapy could slow CKD progression even in individuals with preserved renal function (eGFR ≥ 60 mL/min/1.73 m2), including those classified as KDIGO low risk [17, 28, 36,37,38,39,40]. On the basis of the effectiveness of SGLT2i, the model assumed that PromarkerD implementation would reduce CKD progression through targeted interventions based on patient risk. Low-risk PromarkerD patients progressed as per the SoC model. High-risk patients initiated SGLT2i therapy, resulting in reductions in CKD progression probabilities, with greater absolute effects observed in higher-risk KDIGO categories (Supplementary Table 1C) [28]. The number of individuals receiving additional benefits from SGLT2i treatment was determined by the sensitivity of PromarkerD at the high-risk cutoff (50.5%), while unnecessary treatment costs were determined by the false positive rate (1 − specificity; specificity 94.5%) [12]. At the moderate-risk threshold, sensitivity (85.1%) determined the proportion of true moderate-risk individuals receiving the health management benefit, whereas the false positive rate (1 − specificity; specificity 71.7%) represented individuals incorrectly classified as moderate risk and therefore receiving management without corresponding risk reduction. Individuals incorrectly classified as low risk (false negatives) were assumed to follow SoC progression without additional intervention, while incurring testing costs. Treatment with SGLT2i was the only therapy considered in the present budget impact model, as robust stage-specific renal outcome data was not available for other renoprotective therapies (glucagon-like peptide-1 receptor agonists and nonsteroidal mineralocorticoid receptor antagonists) during model development. For moderate-risk patients, the model assumed a 20% reduction in CKD progression from enhanced clinical management. This estimate was informed by Lewis et al. [41], which demonstrated a similar risk reduction with irbesartan among patients with emerging nephropathy receiving targeted intervention. In the present model, the 20% reduction represents a management effect triggered by risk stratification rather than the effect of a specific pharmacologic effect. Because this parameter is uncertain, sensitivity analyses were performed across the reported 95% confidence interval (3–34%) to assess its influence on results. Adherence to treatment was assumed to be 80%, with sensitivity tested at 60% and 100%.
2.4.2 PromarkerD Test and Treatment CostsPromarkerD testing cost was set at US $390 per test, reflecting the 2026 US CMS Clinical Lab Fee Schedule published rate [42]. Retesting frequencies were every 48 months for low-risk, 24 months for moderate-risk, and no retesting for high-risk individuals (remained on continuous SGLT2i therapy), on the basis of recommendations from the ADA diabetes-related CKD Consensus report [43] and the PromarkerD Clinical Advisory Board, being intended for guidance only. CKD stage-specific healthcare costs and SGLT2i treatment expenses were as per the SoC model.
2.5 Economic AnalysisAnnual costs and savings were calculated over 10 years in USD. All costs are reported in 2026 USD. A 3% annual discount rate was applied to future costs and savings to reflect their present value [44]. The consumer price index (CPI) inflation adjustment was based on US inflation rate trends from the last 10 years and extrapolated out to the next 10 years [45]. Net savings were defined as:
$$\begin }\;} = \, \left( }\_}\_} - }\_}\_}} \right) - \left( }\_}\_} + }} \right) \hfill \\ \quad \quad - \left( }\_}\_} - }\_}\_}} \right) \hfill \\ \end$$
Net present value (NPV) represents the sum of discounted annual net savings over the 10-year period, providing a time-adjusted measure of the total economic benefit. Since progression of chronic kidney disease to ESRD is very slow, a time horizon of 10 years was considered appropriate to capture the potential benefits of early detection of the disease.
2.6 Sensitivity AnalysisOne-way sensitivity analyses tested model robustness by varying key assumptions. CKD progression probabilities, the assumed benefit of enhanced health management in moderate-risk individuals, SGLT2i costs, and the effectiveness of SGLT2i therapy were each varied across the extremes of their reported 95% confidence intervals [25, 28, 32, 41]. Scenario analyses also examined the impact of doubling the frequency of PromarkerD retesting or removing retesting entirely, as well as applying treatment effects to both moderate- and high-risk, or only high-risk, individuals. Additional scenarios explored alternative levels of SGLT2i use under SoC, including no background use and increased background use to 40% [27]. Finally, treatment adherence varied by assuming either 60% adherence or perfect adherence to SGLT2i therapy.
Comments (0)