
Remember me
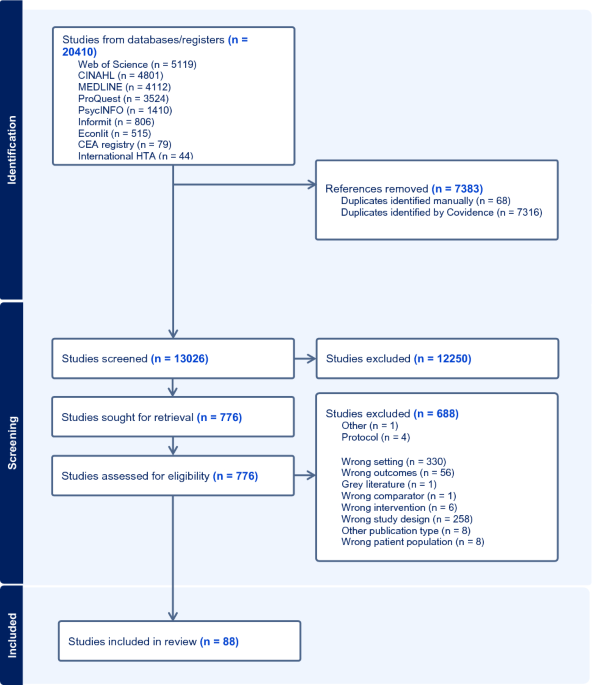



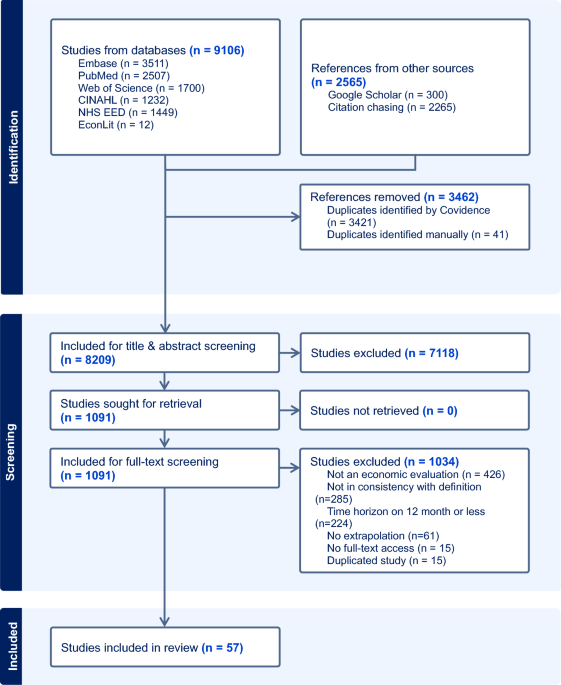
Figure 1 illustrates the study selection process. Initially, 324 articles were identified through database searches and hand searches. After removing 55 duplicate records, the remaining studies were screened based on their titles and abstracts for relevance to the topic. Subsequently, 11 full-text articles were assessed for eligibility, of which eight met the inclusion criteria and were included in the final review.
Fig. 1
Preferred reporting items for systematic reviews and meta analysis (PRISMA) diagram. This diagram demonstrates the process of review, inclusion and exclusion of studies
3.2 Overview of Included StudiesAll studies were conducted in Sub-Saharan Africa, with South Africa accounting for 50% of the studies. Regarding country income level, half of the studies were from upper-middle-income countries, while the rest came from lower-middle-income and low-income countries. Most studies (87.5%) were conducted in public hospitals, and antibiotics were the most commonly offending drugs (62.5%). The number of ADRs per patient, severity, and type of ADR were inconsistently described. The majority of studies (62.5%) were published before 2020. Details are presented in Table 1.
Table 1 Geographic and clinical overview of included studies based on World Bank classification (N = 8)3.3 Methodological Approaches of StudiesData collection approaches are nearly equally distributed between prospective (50%) and retrospective (37.5%). The remaining 12.5% of studies did not report a data collection approach. Seventy-five percent of the studies did not report whether they employed a prevalence or incidence-based approach, with only one study in each category explicitly identifying a prevalence or incidence-based design. Similarly, six studies reported their study perspectives, including both health system and combined perspectives.
All studies except one consistently reported only direct medical costs, while indirect costs were notably missing (Table 3). Half of the studies used a bottom-up costing method, whereas the other half did not specify their approach. Regarding the timeframe, five studies (62.5%) limited cost estimation to the hospitalization period, one study (12.5%) assessed costs over <1 year, and two (25%) collected data over a year or more. The majority of studies (87.5%) reported costs at the health facility, with only one study reporting at the national level. Only half of the included studies stated the cost year. Details are found in Table 2.
Table 2 Methodological characteristics of studies (N = 8)3.4 Cost of Adverse Drug ReactionsAll included studies except one consistently estimated only direct medical costs, excluding direct non-medical and indirect costs. Medications were the most frequently cited and dominant cost driver, followed by laboratory tests, hospital bed charges, and intensive care unit stays (Table 3). This highlights a significant gap in the literature and underscores the need for more comprehensive COI studies, including both direct and indirect costs. The average cost of ADR per patient per hospitalization ranged from I$54.75 in Nigeria to I$7438.47 in South Africa, reflecting substantial variation in costs across studies per hospital stay. In Eritrea, the average cost per cohort is I$420,368 over 5 months, with a per-patient cost of I$456 [39]. In contrast, a study in South Africa reported per-patient per hospital stay costs of I$7438.47 [34]. Some studies also reported annual per-patient costs, such as the study conducted in South Africa, which estimated costs ranging from I$174.92 to I$671.66 for ototoxicity-related ADRs [32]. The variations of reporting units, whether per-patient, per-cohort, per-event, or annual, illustrate the challenge of across-study comparisons, thereby further emphasizing the need for structured and similar research approaches in future COI studies.
Table 3 Average reported costs and included cost types per study (N = 8, costs reported in I$)The studies varied in their clinical context and the severity of ADRs considered. For example, Oshikoya et al. in Nigeria categorized direct medical costs according to ADR severity, reporting costs ranging from I$1089.25 to I$6989.07, with a total expenditure of I$22,519.91 for admitted patients in one teaching hospital [36]. This underscores the importance of early identification as a potential cost-saving benefit of early targeted management of ADRs. Similarly, Oxley-Oxland et al. reported ADR-related costs ranging from I$2892.80 to I$5520.92, specifically for patients requiring mechanical ventilation [33]. This indicates that the highest ADR-related costs were found in critical patients, suggesting a correlation between ADR severity and treatment cost.
In addition, the type of offending medication causes cost variations. For example, Chikeya et al. reported annual per-patient costs of I$39.07 for zidovudine (AZT) and I$35.67 for tenofovir (TDF) [35]. However, the respective cohort costs are I$668.22 for AZT and I$2829.83 for TDF. This suggests a clear cost difference between these groups of medications. However, this does not imply that patients should preferentially initiate treatment with TDF solely to reduce ADR-related costs. Details of cost types and cost drivers are available in Table 3.
3.5 What Determines ADR-Related Costs?Some studies differentiated costs by ADR severity, while others categorized them by affected body system or other criteria. This indicates that the authors were unable to present the data in a table or graph and, therefore, reported it narratively.
Severity of ADR: The cost associated with ADR management increases substantially with the severity of the reaction. For example, a study in Nigeria reported that the mean treatment cost per severe ADR was I$6989.07, which was significantly higher than the cost for moderate reactions (I$1089.25) [36]. Similarly, severe ADRs related to highly active antiretroviral therapy (HAART) were consistently associated with higher treatment costs [35]. Schnippel et al. also reported that severe dermatologic reactions often required intensive care management, resulting in higher costs (I$671.66) compared with moderate reactions (I$174.92), with an attributed cost of I$358.53 for severe ADRs [32]. These findings highlight the substantial financial burden associated with severe ADRs and underscore the importance of early detection and prevention strategies.
Level of health facility: ADR-related costs also vary by the level of healthcare facility. In Eritrea, over 5 months, the average government expenditure per patient with an ADR ranged from I$241 at community hospitals to I$481 at the national referral hospital. Similarly, patient out-of-pocket costs increased from I$49 to I$261, with higher levels of care [39]. These findings indicate that treatment at higher-level hospitals is associated with substantially greater costs for both patients and the health system.
Hospitalization and ICU care: Hospitalization is a major cost driver in ADR management, accounting for up to 65%–70% of total expenses in some cases, such as cutaneous ADRs related to anti-TB drugs [34]. Patients who developed ADRs during admission often experienced prolonged hospital stays, whereas those admitted for mild or moderate ADRs generally had shorter stays. The need for intensive care, including interventions such as ventilation or dialysis, further increased costs, particularly among patients with severe outcomes [33]. Limited access to specialized services, such as pediatric ICUs, and the need for procedures like hemodialysis may also influence cost estimates and contribute to the underestimation of the true economic burden of ADRs [33]. Overall, prolonged hospitalization substantially increases the financial burden associated with ADR management.
Patient and treatment-related factors: Certain patient characteristics were consistently associated with higher ADR-related costs. Elderly patients, individuals with multiple comorbidities, and those receiving polypharmacy were identified as high-risk groups, incurring greater healthcare expenses due to the increased likelihood and severity of ADRs [37]. Among HIV patients, lower CD4 counts and younger age at HAART initiation were also linked to a higher incidence of ADRs, contributing to increased treatment costs [35]. In addition, drug regimen and ADR type were important cost determinants. For example, gastrointestinal ADRs in HAART patients were among the most costly for both TDF- and AZT-based regimens, largely due to laboratory investigation costs [35]. Similarly, ADRs associated with theophylline resulted in high expenditure because of the need for specialized interventions such as dialysis [33].
3.6 Reporting Quality of Included StudiesThe quality of studies was assessed using a consensus-based COI study checklist, and most studies clearly presented their results. The results presentation was consistently aligned with the study aim and corresponded with their conclusions. This quality assessment tool is divided into three main domains: population and clarity of objectives, methodology and cost analysis, and result transparency and reporting quality.
3.6.1 Population, Study Objective, and PerspectivesAll included studies [32,33,34,35,36,37,38,39] clearly described the study objectives and defined the target population, with population characteristics consistent with the study analyses. However, the reporting of the study perspective was inconsistent. Although 75% of the studies [32,33,34,35,36, 39] stated a study perspective, only three studies [33, 35, 36] provided justification, citing reasons such as conducting the study in a provincial clinic, reliance on cost data from local authorities, or shared costs between government and patients. The remaining studies did not clearly specify or justify their perspective, representing an important reported gap. Since the study perspective determines which costs should be included in the analysis, its omission or inadequate justification may affect the validity and interpretability of cost estimates.
3.6.2 Methodology and Cost AnalysisEpidemiological, costing, and data collection approaches: All included studies [29,30,31,32,33,34,35,36] reported the data collection method as either retrospective or prospective. However, only two studies specified their epidemiological approach, using either an incidence-based design in South Africa [32] or a prevalence-based approach in Eritrea [39]. Similarly, only half of the studies clearly report their costing approach [32,33,34, 36].
Resource identification, measurement, and valuation: Three studies conducted in South Africa [33,34,35] and one in Eritrea [39] fully identified relevant healthcare resources, including consultations, laboratory tests, hospital stays, medications, and medical interventions. Two studies from Nigeria [36, 37] partially identified these resources, while the study conducted in Ethiopia [38] did not report resource identification. Except for the Ethiopian study [38], all included studies [32,33,34,35,36,37, 39] measured and valued the identified resource components. Furthermore, the Ethiopian study [38] did not justify the omission of resource measurement and valuation.
Time horizon, discounting, and sensitivity analysis: All included studies [29,30,31,32,33,34,35,36] specified their time horizon for cost assessment; however, only two studies from South Africa [34, 35] and one from Nigeria [37] provided justifications. Discounting was applied in one study [32] due to a time horizon exceeding 1 year, whereas it was not required in the remaining studies [33,34,35,36,37,38,39], with time horizons <1 year typically limited to hospital stays. Sensitivity analysis was conducted in three South African studies [33,34,35], which clearly reported the variables tested. Subgroup analysis was not performed in the Ethiopian study [38], while the Nigerian studies [36, 37] conducted partial subgroup analyses. In contrast, the South African studies reported more comprehensive subgroup analyses [32,33,
Comments (0)