
Remember me



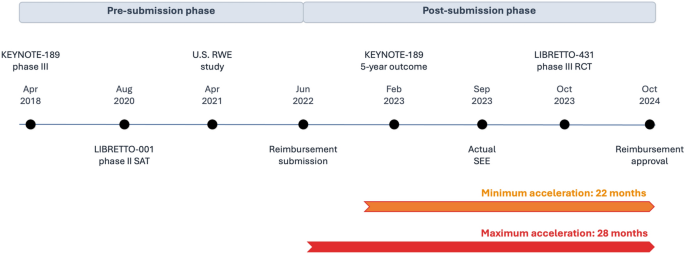
We used a model-based approach to conduct a series of cost-effectiveness analyses, grouping different sources of evidence (i.e., published clinical evidence and SEE) to estimate the long-term health and economic consequences of selpercatinib versus pembrolizumab plus pemetrexed and platinum-based chemotherapy for patients with advanced RET fusion-positive NSCLC in Norway. Given the June 2022 adjustment of the selpercatinib reimbursement application to extend its indication to the first-line setting, we chose this timepoint as a hypothetical first-line reimbursement submission. We categorized available SoC evidence into either “pre-submission” or “post-submission” phases (Fig. 1), on the basis of their availability relative to this hypothetical submission timepoint. To assess whether incorporating SEE would result in cost-effectiveness findings consistent with those obtained once phase III evidence became available, we compared the cost-effectiveness findings associated with SoC evidence potentially available prior to June 2022 (i.e., “pre-submission evidence”), which includes SEE, with the cost-effectiveness findings using evidence available after June 2022 (i.e., “post-submission evidence”). We evaluated future costs and health outcomes over the remaining lifetime of the cohort, in accordance with Norwegian HTA guidelines [29]. Costs were measured in 2024 Norwegian Kroner and converted to 2024 US dollars (exchange rate 1 USD = 10.7574 NOK) [30]. Costs and health outcomes were discounted at 4% annually, as recommended by the Norwegian guidelines [29]. We adopted an extended healthcare perspective, in line with Norwegian guidelines [29]. Incremental cost-effectiveness ratios (ICERs), calculated as the additional costs per quality-adjusted life-years (QALY) gained, were compared with the Norwegian severity-specific cost-effectiveness threshold, based on the absolute shortfall (see Supplementary Document and Supplementary Table S1), of $46,015 per QALY [31] to indicate a cost-effective intervention. Key model inputs, including long-term survival, health-related quality-of-life (HRQoL) inputs, and cost inputs, are provided in Table 1.
Fig. 1
Timeline impact of SEE on reimbursement. Note: The range assumes a hypothetical SEE timepoint before reimbursement submission. The 28-month estimate assumes SEE-informed evidence was available at submission; the 22-month estimate allows for up to 180 days of assessment after submission. RCT, randomized controlled trial; RWE, real-world evidence; SAT, single-arm trial; SEE, structured expert elicitation
Table 1 Key parameter inputs2.2 Target Patient PopulationThe target patient population was based on the Norwegian reimbursement dossier [23]: Norwegian patients who were aged at least 18 years with pathologically confirmed unresectable stage IIIB, IIIC, or IV metastatic RET-positive non-squamous NSCLC who had not previously received systemic treatment for metastatic disease, i.e., first-line treatment.
2.3 InterventionsWe compared selpercatinib 160 mg twice daily in continuous 21-day cycles with pembrolizumab plus pemetrexed and platinum-based chemotherapy, which represents the current SoC and the relevant comparator for reimbursement decision-making in Norway for first-line treatment of advanced nonsquamous RET fusion-positive NSCLC. Chemotherapy alone is not considered a clinically relevant or reimbursed first-line option in the Norwegian setting and was therefore not included as a comparator. Specifically, the SoC arm received pembrolizumab 200 mg once every 21 days, for up to 35 cycles (24 months), carboplatin (area under the concentration–time curve, 5 mg per milliliter per minute) every 21 days for 4 cycles, and pemetrexed (500 mg/m2) every 21 days.
Patients discontinuing the above first-line treatment continue with second-line treatment. The patients who received selpercatinib continued with pembrolizumab plus pemetrexed and platinum-based chemotherapy, whereas the second-line treatment for patients in the SoC arm was docetaxel (100 mg/m2) every 21 days for up to ten cycles (7 months). These assumptions reflect a simplified, but representative, second-line treatment for each treatment arm based on Norwegian clinical practice and national guidelines. Although subsequent-line treatment patterns are heterogeneous in real-world clinical practice, this approach was adopted to ensure consistency across analyses. After completion of second-line treatment, patients were assumed to receive best supportive care (BSC) until death.
2.4 OutcomesThe outcomes included long-term survival such as progression-free survival (PFS) and overall survival (OS), extrapolated either from available clinical trials and RWE studies or from SEE. We further leveraged long-term survival to evaluate discounted total costs, quality-adjusted life-years (QALYs), life-years (LYs), and incremental cost-effectiveness ratios (ICERs) to compare the cost-effectiveness of selpercatinib with SoC.
2.5 Model StructureWe developed a partitioned survival model (PSM) in R version 4.2.1 [32, 33] with a 3-week cycle length to probabilistically project expected costs and outcomes over time for first-line treatment of selpercatinib and SoC, based on PFS and OS curves derived from available clinical evidence or SEE. Consistent with standard practice in PSM [34], PFS and OS were modeled as independent survival functions rather than assuming a correlation between treatment effects. As a result, incremental OS benefits are not mathematically derived from PFS, and improvements in PFS do not imply proportional improvements in OS. Instead, time spent in the progressive disease (PD) state is defined by the area between the PFS and OS curves. Therefore, the model consists of three mutually exclusive health states: PFS, PD, and death (D) (Supplementary Fig. S1). The cohort of patients was assumed to start in the PFS state. Over time, the proportion of patients in each health state was determined by the PFS and OS curves, with the time spent in the PD state calculated as the difference in area between these two curves. Accordingly, incremental QALYs may arise not only from differences in OS, but also from differences in the amount of time spent in the PFS and PD states, which are associated with different HRQoL values in the model (Table 1). Patients transitioning from the PFS state to the PD state were assumed to initiate second-line treatment. Upon completion of second-line treatment, patients were assumed to receive BSC until death.
2.6 Clinical Parameters OverviewWe derived clinical parameters from two sources: published clinical evidence and SEE. Our primary clinical evidence included PFS and OS curves from the phase II LIBRETTO-001 and phase III LIBRETTO-431 trials. For the post-submission analyses based on LIBRETTO-431, the PFS and OS for the SoC arm were derived from the intention-to-treat (ITT) pembrolizumab population. Although not all patients assigned to this arm ultimately received pembrolizumab, the ITT population reflects a predominantly pembrolizumab-based chemo-immunotherapy strategy, consistent with Norwegian first-line practice.
To complement the primary evidence, we also incorporated data from three external studies, two in the “pre-submission” phase and one in the “post-submission” phase (Fig. 1). In addition, to further supplement the evidence for the “pre-submission” SoC, we conducted SEE to gather expert opinions regarding survival probabilities for various time points (Table 2). For long-term projections of PFS and OS, we used parametric regression to extrapolate the values beyond the observed durations.
Table 2 Progression-free survival (PFS) and overall survival (OS) estimates from structured expert elicitation2.6.1 Published Clinical EvidenceIn addition to our primary evidence, two “pre-submission phase” studies were identified to supplement the SoC evidence: (1) the pembrolizumab treatment arm of the phase III KEYNOTE-189 RCT, i.e., SoC in our analysis [35], and (2) a RWE study from the USA, providing the real-world clinical evidence of SoC [36]. Neither of these two studies were specific to the RET fusion-positive NSCLC population. The KEYNOTE-189 RCT included patients with metastatic nonsquamous NSCLC without sensitizing epidermal growth factor receptor (EGFR) or anaplastic lymphoma kinase (ALK) mutations, while the US RWE study included patients whose tumors tested negative for EGFR and ALK alterations. Although both sources represent RET-unselected populations, in the absence of RET fusion-positive comparator data for pembrolizumab-based chemo-immunotherapy, these studies were considered as the best available external evidence to inform pre-submission SoC effectiveness.
We also identified one additional study to complement the SoC evidence in the “post-submission phase”: the 5-year outcomes from the phase III KEYNOTE-189 trial [37]. We reviewed and compared the patient characteristics of these external studies with those of the target patients in the phase II LIBRETTO-001 and phase III LIBRETTO-431 trials (Supplementary Table S2).
2.6.2 Extrapolation of Published Clinical EvidenceWe used parametric regression approaches to allow for extrapolation of PFS and OS up to the lifetime horizon. As individual patient data (IPD) were not available for any of the studies, we first reconstructed IPD from the Kaplan–Meier (KM) PFS and OS curves by using the IPDfromKM package in R [38]. Parametric models were then fit to the KM trial data for PFS and OS for extrapolating effectiveness estimates from the short-term trial periods (range 19–42 months) to the remaining lifetime horizon. The survival curve fitting was carried out in line with the Norwegian guidelines [29]. In the base case, we fitted exponential, Weibull, log-normal, log-logistic, Gompertz, gamma, generalized gamma, and Royston–Parmar spline distributions. Model fit was assessed using the Akaike information criterion (AIC) and the Bayesian information criterion (BIC) (Supplementary Table S3), combined with visual inspection and clinical plausibility, to select the best-fitting parametric distributions for the model. Hazard rates over time, estimated nonparametrically from the observed data using kernel-based methods, were compared with hazard rates predicted by each parametric model to assess the long-term extrapolations. Results of the extrapolation are provided in Supplementary Table S4 and Supplementary Figs. S3–S13.
Importantly, for phase III LIBRETTO-431, patients who experienced disease progression were eligible for treatment crossover to selpercatinib [27], leading to uncertainty regarding the survival benefit of the SoC. As current statistical approaches are inadequate for treatment switch adjustments without IPD, we did not adjust the OS treatment effect estimate for treatment crossover. Alternatively, we factored in the costs for the estimated proportion of patients switching from SoC to selpercatinib.
2.6.3 Structured Expert ElicitationTo supplement the pre-submission SoC evidence, we conducted a SEE in September 2023 prior to the phase III LIBRETTO-431 results presented at the European Society for Medical Oncology [39] (Fig. 1). Three Norwegian clinical oncologists with experience in treating advanced lung cancer were identified and shortlisted by NOMA. An evidence dossier summarizing relevant clinical trial data, along with standardized guidance on probabilistic judgements, were provided to the experts in advance. Using a facilitated individual elicitation process, based on the SHELF framework [16], experts provided their probabilistic judgments on the distributions of PFS and OS for three time points (i.e., 1, 2, and 5 years). We aggregated individual estimates from experts using linear pooling and a Bayesian method within the expertsurv package in R [40]. Details about the elicitation procedures can be found in the Supplementary Document and Supplementary Table S5.
2.6.4 SEE ExtrapolationWe applied the Bayesian method developed by Cooney and White to fit a range of parametric models [40], including the exponential, Weibull, log-normal, log-logistic, and Royston–Parmar spline distributions, to the SEE-informed estimates to extrapolate long-term survival. We used elicited estimates in two ways as “pre-submission” evidence for SoC, either as the sole source of information or combined with other external published clinical evidence, to investigate their impact. Consistent with our extrapolation approach for published clinical evidence, we evaluated the AIC and BIC, combined with visual inspection and clinical plausibility, to select the best-fitting parametric distributions. We evaluated the long-term plausibility by comparing the projected survival against aggregated expert-elicited uncertainty ranges. Parametric survival curves showing repeated deviations from the expert uncertainty intervals across multiple elicited timepoints were considered less plausible for extrapolation. However, parametric distributions with a single or minor deviation, particularly at later timepoints, were not excluded but would be given lower priority relative to models showing closer agreement. Results of SEE extrapolation can be found in Supplementary Table S6.
2.7 Health-Related Quality of Life (HRQoL) InputsAs HRQoL data for Norwegian patients with NSCLC are not available, we utilized UK-specific HRQoL values from a published study [41], which employed time trade-off methods to measure HRQoL for NSCLC patients receiving first-line treatment in the UK, Australia, China, France, and Korea (Table 1). We considered adverse events (AEs) of grade 3 or higher with an incidence of 5% or more, on the basis of the phase III LIBRETTO-431 trial (Supplementary Table S7), including aspartate aminotransferase (AST) increase, alanine aminotransferase (ALT) increase, hypertension, fatigue, thrombocytopenia, leukopenia, neutropenia, QT prolongation on electrocardiogram (ECG), and anemia. HRQoL decrements associated with AEs, based on the same HRQoL study [41], were applied (Table 1). We assumed that the decrement of QT prolongation on ECG was the same as hypertension, and the decrements of thrombocytopenia, leukopenia, and anemia were the same as neutropenia.
2.8 Resource UseResource use linked to first-line treatment, subsequent treatment, disease management, AE management, clinical tests, and follow-up procedures was derived from official Norwegian guidelines [42], published literature [43], and independent expert opinion (Table 1). Drug prices were derived from the NOMA medicine database [44] of maximum pharmacy purchase price less value added tax. These costs were applied at each infusion up to disease progression or death and limited to dosing schedule reported in LIBRETTO-431 (see “Interventions” section).
We applied outpatient visit costs, based on 2024 diagnosis-related group (DRG) (~ $4857) with DRG weight of 0.048 (DRG code 904 C) [45], to reflect routine disease monitoring and clinical management during active treatment. Patients receiving selpercatinib were assumed to receive an outpatient visit at treatment initiation, at months 2, 4, and 7, and subsequently every 3 months thereafter. Patients receiving pembrolizumab-based chemo-immunotherapy or docetaxel were assumed to have outpatient visits every 3 weeks. As a proxy for BSC costs, we used average healthcare costs incurred in specialist care for cancer patients during the final 2–3 months before death based on Norwegian data. End-of-life costs were applied as a one-off cost at death and were estimated using average primary care and home- or community-based care costs for death of cancer patients. Both BSC and end-of-life costs (Table 1) were based on published literature [46].
Similar to the Canadian Agency for Drugs and Technologies in Health (CADTH) reimbursement review [47], we applied a one-off cost associated with treatment-related AEs at the onset of the model (i.e., in the first cycle) under the assumptions that all identified AEs required hospitalization. The average duration of hospitalization was extracted from a paper [48] that provided the mean length of hospitalization stay of treating grade 3 or 4 AEs associated with metastatic melanoma in the USA (Supplementary Table S7). The hospitalization cost was based on the DRG weight of 0.614 (DRG code 102) and cost of treating lung cancer patients in the Norwegian guideline [45]. We assumed that the cost of managing leukopenia was the same as neutropenia, the cost of managing fatigue was similar to managing nausea, and the cost of QT prolongation on ECG was the same as hypertension.
2.9 Analyses2.9.1 Analysis OverviewWe conducted a total of seven cost-effectiveness analyses (Table 3): five “pre-submission” analyses and two “post-submission” analyses.
Table 3 Source of evidence for selpercatinib and standard of care (SoC) in the pre-submission and post-submission analysesFirst, we conducted three “pre-submission” phase cost-effectiveness analyses that directly incorporated SEE to inform SoC estimates, with selpercatinib data from the phase II LIBRETTO-001 SAT, including using:
(1)Aggregated SEE information alone
(2)Aggregated SEE information, combined with data from the KEYNOTE-189 phase III trial as a prior
(3)Aggregated SEE information, combined with the US RWE data as a prior
We conducted two additional “pre-submission” phase analyses that did not utilize SEE to inform SoC estimates by using:
(4)KEYNOTE-189 phase III alone
(5)US RWE data alone
Finally, in the “post-submission” phase, we conducted two cost-effectiveness analyses that incorporated the phase III LIBRETTO-431 RCT:
(6)Directly applied LIBRETTO-431 phase III trial data for both selpercatinib and SoC, and adjusted treatment costs in the SoC for the proportion of patients (assumed 54%) who switched from SoC to selpercatinib
(7)Adjusted SoC by substituting the OS curves with the KEYNOTE-189 5-year outcomes and maintained the PFS curves from the LIBRETTO-431 phase III
Notably, in the LIBRETTO-431 trial, patients randomized to the SoC arm were permitted to switch to selpercatinib upon disease progression. Several statistical approaches can, in principle, be used to adjust OS estimates for treatment crossover, including rank-preserving structural failure time models, inverse probability of censoring weights, or surrogacy-based adjustment. In addition, assumptions regarding post-progression survival duration according to subsequent treatment received could also be considered. However, these approaches require access to IPD, including information on the timing of crossover, duration of post-progression treatment, and outcomes after switching, or otherwise rely on strong and unverifiable assumptions when only published data are available. As IPD from LIBRETTO-431 were not publicly available, we did not consider these approaches sufficiently robust for the present analysis. Consequently, OS treatment effects were not adjusted for crossover. Instead, we chose to reflect the observed trial design by incorporating the drug costs associated with treatment switching for the estimated proportion of patients who crossed over from SoC to selpercatinib. Our intention was not to redefine the comparator or to assume routine Norwegian practice after progression, but rather to capture the economic consequences of crossover without imposing assumptions about its effect on survival. In doing so, we aimed to preserve an internally consistent, trial-based incremental comparison (and ICER), not to emulate Norwegian practice per se.
2.9.2 Assessing the Predictive Validity of SEEWithin the “pre-submission” phase, we compared Markov traces for PFS and OS derived from SEE-informed SoC estimates versus those obtained from published literature (KEYNOTE-189 and US RWE). Additionally, we also compared Markov traces for PFS derived from SEE-informed SoC estimates in the pre-submission phase with those from the LIBRETTO-431 RCT.
2.9.3 Probabilistic Cost-Effectiveness AnalysesAll cost-effectiveness analyses were performed probabilistically through Monte Carlo simulations across 10,000 iterations, jointly sampling key model parameter inputs from their commonly recommended parametric distributions (Table 1).
We compared mean discounted costs, QALYs, and ICERs:
(1)Among three SEE-informed analyses within the pre-submission phase,
(2)Between three SEE-informed analyses and two non-SEE analyses within the pre-submission phase
(3)Across the pre- and post-submission phases
Costs were disaggregated (i.e., first-line treatment, second-line treatment, best supportive care, patient follow-up (including outpatient visits and computed tomography (CT) scans), AE management, and end-of-life costs) to identify key cost drivers across pre- and post-submission analyses.
2.9.4 Scenario Analyses2.9.4.1 Time Horizon Scenario AnalysesTo assess the sensitivity of the results to the analytic time horizon, we conducted additional scenario analyses using shorter time horizons of 5 years and 10 years, respectively. The resulting cost-effectiveness estimates were compared with those from the base-case analysis using a remaining lifetime horizon.
2.9.4.2 Parametric Survival Distribution Scenario AnalysesTo assess the sensitivity of the results to long-term survival extrapolation, we conducted scenario analyses comparing the base-case parametric distributions with alternative parametric distributions for selected survival curves.
First, in the pre-submission analysis using aggregated SEE information alone (i.e., analysis 1 described in Sect. 2.9.1), for the SoC OS curve informed by SEE, we used a Weibull distribution in the base case and an exponential distribution in the scenario analysis.
Second, in the post-submission analysis (i.e., analysis 6 described in Sect. 2.9.1), we explored an alternative distribution for the SoC OS curve in the LIBRETTO-431 RCT. We extrapolated the SoC OS curve from the LIBRETTO-431 RCT using a Gompertz distribution in the base case and a Weibull distribution (shape: 0.077, scale: 1.891) in the scenario analysis.
We compared the cost-effectiveness results from these two scenario analyses with those from the corresponding base-case analyses.
Comments (0)