Since the first laparoscopic appendectomy was performed in 1980, major developments have been made in the field of minimally invasive surgery (MIS). MIS has been found to be superior to open procedures in a variety of general surgery operations including appendectomy, cholecystectomy, hernia repair, and colectomy [1,2,3,4,5]. The ability to perform these procedures through a minimally invasive approach has led to shorter hospital stays, decreased surgical site infections, decreased intra-operative blood loss, and decreased overall morbidity while providing similar operative results [6,7,8,9,10]. Laparoscopic surgery has become the standard of care for many emergent and elective general surgery operations.
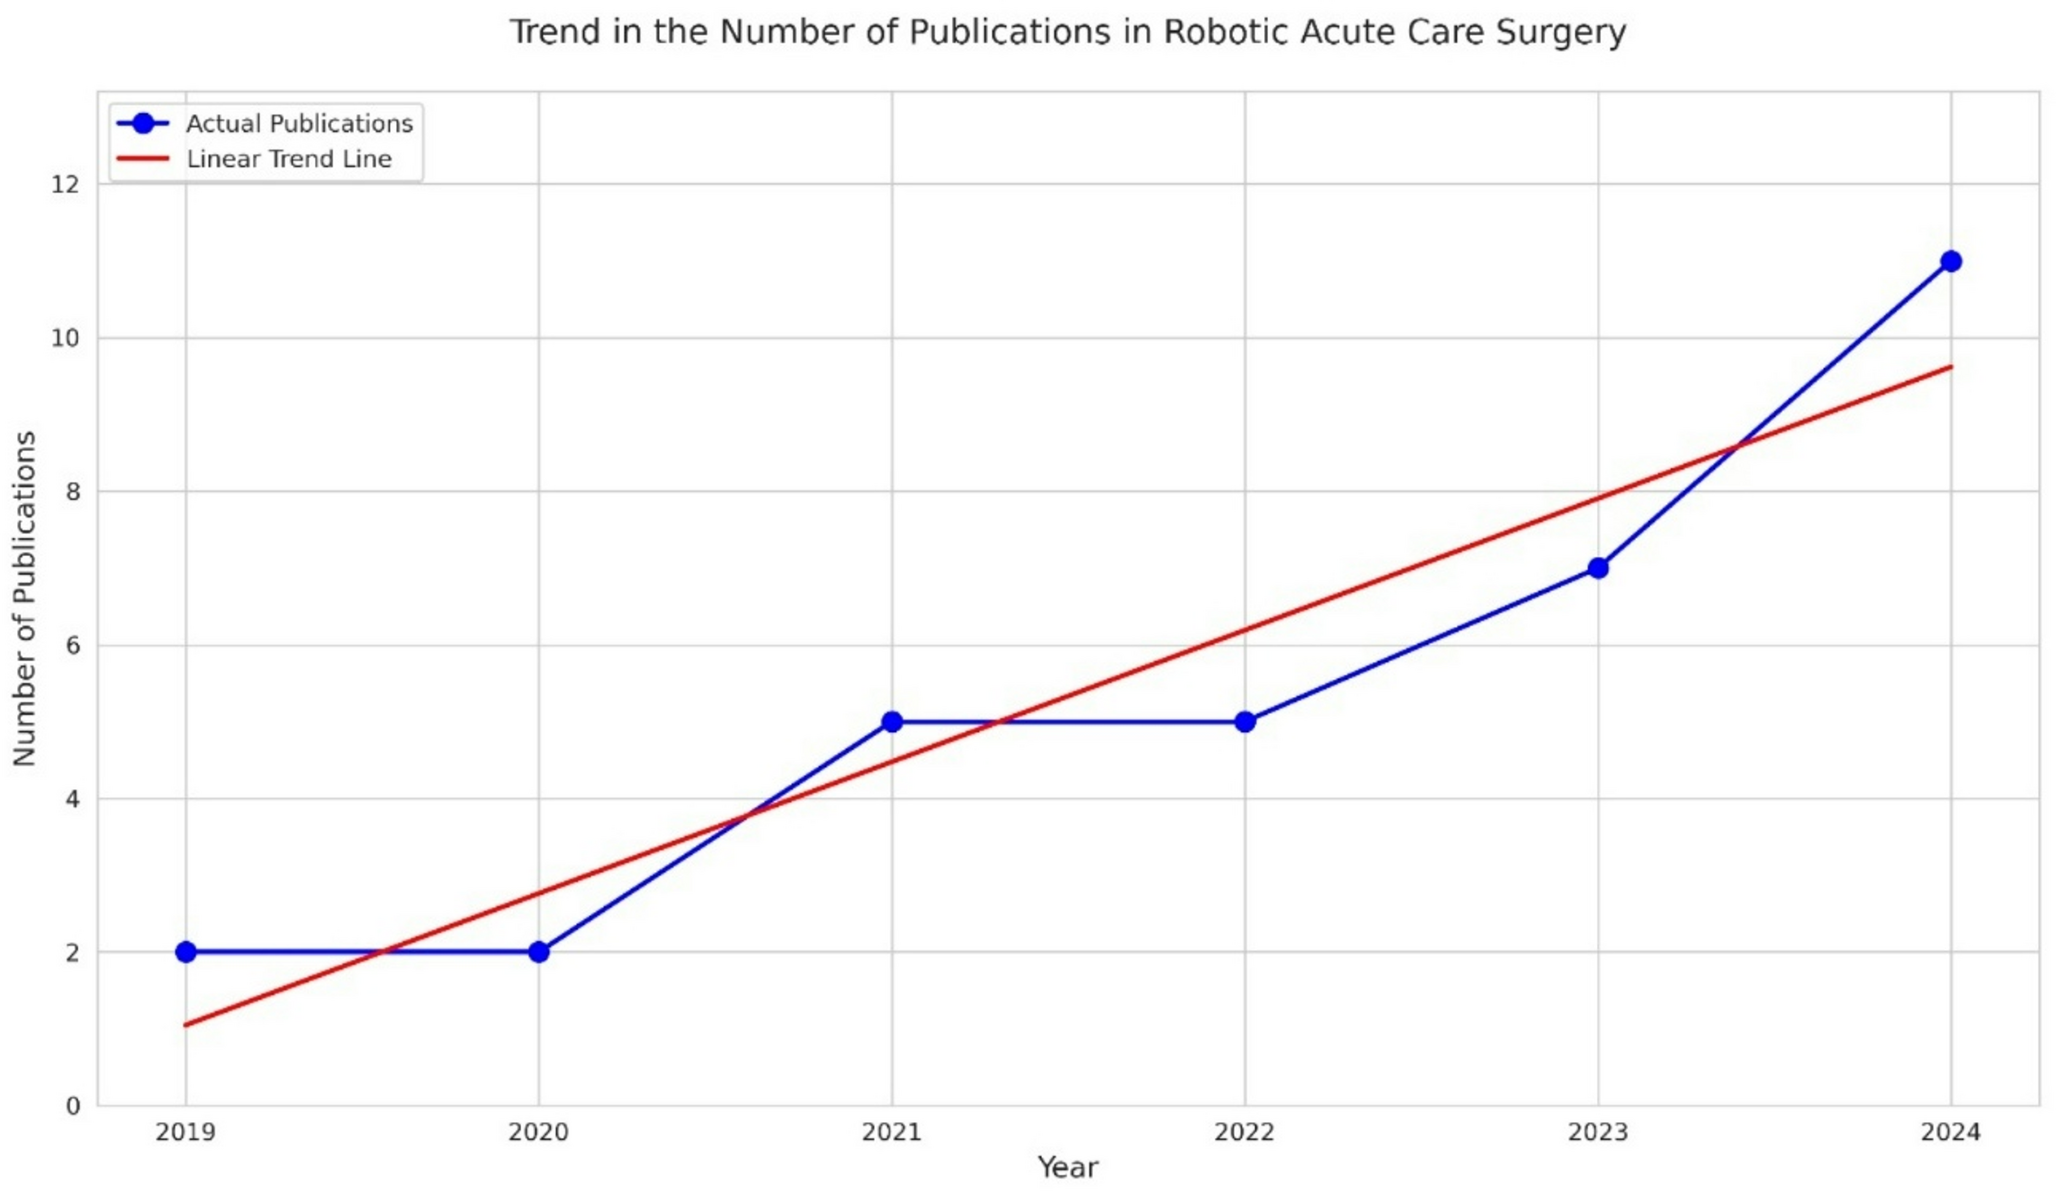
Over the past 15 years, the use of robotics in the field of surgery has drastically increased so much so that the World Society of Emergency Surgery (WSES) recently published its position statements on the role of robotics in emergent general surgery (EGS) [11]. From 2012 to 2018 there was an 8.4-fold increase in the use of robotic surgery (1.8–15.1%) as a whole. Furthermore, general surgery has seen a 41% increase in inguinal hernia repair (0.7% to 28.8%) and a 37-fold increase in cholecystectomy (0.1% in 2010 to 5.2% in 2019) [12,13,14]. The increase in robotic assisted operations is likely due to two significant factors.
First, robotic surgery benefits both the patient and the surgeon. For the patient, robot assisted surgery (RAS) has been found to have less conversions to open in multiple procedures including cholecystectomy, colon resection, and hernia repairs [5, 15, 16]. RAS has been associated with decreased length of stay and less readmissions for cholecystectomies [17]. Robotic hernia repair has been found to be effective and safe in the emergent repair of acute cholecystitis, as well as incarcerated ventral/incisional hernias [14, 18].
Second, for the surgeon, the robotic platform provides both a technical and ergonomic advantage. For example, the stereoscopic camera provides a 3-dimensional view of the operating field with improved visualization of vitals structures and tissue planes. The platform also provides motion scaling and tremor filtering which allows for more precision and fine motor control. Wristed instruments provide greater articulation and degrees of freedom, relative to a laparoscopic platform, allowing for more precise movements and tissue manipulation. Finally, the robotic platform provides superior ergonomics and reduced workload for the operative surgeon compared to laparoscopic surgery [5, 19, 20].
In addition to the increase in robotic surgery, Emergency General Surgery patients also make up more than 7% of inpatient admissions [10]. Even so, literature on the use of the robotic platform in Emergency General Surgery (EGS) is limited. With the significant increase in robotic assisted operations being performed nationwide, along with the promising literature regarding patient outcomes after robotic surgery, our goal was to create a Robotic Acute Care Surgical Program (RACS-P) to be able to provide the right care, for the right patient, at any time. This manuscript demonstrates a step-by-step process for developing a RACS-P at our tertiary care facility along with seven lessons learned along the way.
Lesson One: Building a Vision
To provide a framework for program development, we started by creating a vision and establishing a hypothesis. Our goal was to provide high quality care to our patient population by being able to perform the “correct operation on the correct patient, at any time of the day.” We hypothesized that the use of the robotic platform in the EGS setting would be superior to conventional laparoscopy, by decreasing our rate of open surgery and its inherent complications (e.g. SSIs). This, we felt, would provide our institution with a profitable quality improvement opportunity. Better surgical outcomes (fewer conversions to open operations) would lead to shorter lengths of stay (LOS), which would allow for increased hospital patient throughput. The increase in patient throughput had the potential to increase the profit margin for our health care facility. Ultimately, our vision statement and hypothesis served as a key strategic element in the process of getting approval for our initiative with our C-suite (Lesson 3).
Lesson Two: Evaluate Roadblocks
Our next step was to assess barriers to change. In microeconomics, the term “switching cost” is to describe the disadvantages consumers feel they experience when switching from one product, service, or supplier to another. These “costs” may be paid by the consumer in the form of money, time, effort, or emotion - the costs are inclusive of both economic and psychological costs. In our scenario, we recognized that there would be switching costs as we made the conversion from a robotic platform from traditional laparoscopy. Not only would the transition be associated with increased costs (e.g. supplies and equipment), but it would also require training of OR staff, residents/fellows, and the operative surgeons. We acknowledged that it would take time for surgeons to learn how to optimize each step of the operation, including docking the robot, placing ports, and performing the technical aspects of the case. At the same time, access to the robotic, circulator and scrub nurse training, longer case times, and anesthesia familiarity with the robotic platform would all serve as “costs” that we would have to account for.
At the same time, we recognized that our programmatic growth through the process would follow the classic “S-Curve.” [21] S-curves were originally used to show how ideas and technologies spread through societies or corporations. We felt that there be a slow progression at the launch point (case 0–30), rapid growth to the ‘sweet spot’ (case 30–100), and mastery of skills at the peak (case > 100). When combining the concepts of switching costs and the S-curve, we hypothesized that around case 30, a surgeon’s ‘switching cost’ would equilibrate. As a result, we felt that it was of paramount importance to compress the time from case zero to thirty into as short a period as possible. Programmatic access to the robot would play a key role in getting our program the “touches” to succeed.
We immediately recognized that we faced significant access issues. We felt strongly that the key to progression through the learning curve with both faculty, residents, and OR staff is by increasing case volume. At our institution, our service had portents access to two robotic systems. Those systems were primarily being used for elective Gynecologic-Oncology and Urologic procedures: those two programs had a long history of robotic use and had the classic first mover advantage. We were able to get trace access to the robot (two elective days per month) in order to train faculty. We rapidly realized that this would be inadequate to overcome our switching costs.
The solution to our access issues became apparent when we realized that the robot was only being used for elective, daytime case volume. We postulated that by enabling our service to use the robot at nights, on weekends, and holidays, we could facilitate the transition to a more robust elective robotic practice and a higher quality Emergency General Surgery service. More cases would accelerate the learning curve and would build an argument for more elective block time based off case volume. After-hours access could provide a new frontier for the treatment of ACS patients and eliminate the need for a surgical first assist at night. Overall, it would provide the means to build a robotic program while also benefiting patient care.
Lesson Three: ACS Robotics is Good Business
Gaining stakeholder “buy in” is critical to the establishment of an RASC-P [10]. When we introduced our proposal for night time access to the OR committee, we met with repeated refusals. Multiple concerns were raised, including a lack of nursing familiarity with the equipment, longer case times, and sterile processing agility for specialized equipment. Clearly, our steering committee was concerned about their switching costs. As a result, we turned to the C-suite for support.
Our argument to the executive officers was two-fold. First, we felt that RASC-P would advance the Quintuple Aim of the hospital system. Second, ACS robotics is good business.
The Quintuple Aim idea is a set of goals that acts as a framework to guide healthcare improvement. As its name implies it is centered around five pillars: better outcomes, improved patient experience, lower cost, clinician well-being, and health equity [22]. We discussed with our C-suite leadership that RASC-P would touch on every one of the five pillars.
Clinical Outcomes: The hospital would see better patient outcomes by shortening length of stay, reducing readmissions, and reducing overall complications. (e.g. surgical site infections, ventral hernias, conversions to open operations, transfusions)
Patient Experience: Patient experience would improve with reduced post-operative pain, achieve faster discharges, allow patients to return to normal activate in a shorter length of time.
Provider Satisfaction: The overall ergonomic benefit of the robotic system and ability would contribute to surgeon satisfaction. The educational opportunity for our surgical residents and fellows would allow them to receive robot training in a structured university training program. Finally, it would allow attending surgeons to operate without a resident, in the event that our on call residents were involved in other activities at night.
Health Equity: RASC-P would advance the goal of equitable healthcare by providing equal access to MIS and robotic surgery for emergency room patients despite the time of day.
Financial Sustainability: By reducing variability, reducing total cost of care (shortened LOS, less complications), increasing asset utilization (e.g. the robot was a sunk cost), RASC-P provided a sound financial argument. At the time, our administration was considering the a “pay per click” purchase of a new robot. In this paradigm, the more clicks that could be generated in a shorter period of time, the shorter the length of time to ownership. 24-7-365 access would certainly facilitate a more rapid path to ownership.
Fortunately, these principles allow us to gain the support of the administration for after-hours robotic surgery, as well as a “pay per click” purchase of an additional robotic system. Once we had obtained C-suite approval for the initiative, we turned toward implementation, knowing that we had the necessary administrative leverage.
Lesson Four: Training Support Staff
Engaging support staff and creating a highly efficient team was the next integral step in the success of our RASC-P. While the daytime OR team was well trained on the robotic platform, we still needed to train the nighttime staff so that we could offer robotic surgery at any hour of the day. One of our great revelations in the process was that this was the ideal group for this process. Nighttime OR staff are capable of a great deal: they were cross trained to scrub any case (trauma, transplant, ortho, spine, etc.). For this group, additional training, and “being comfortable being uncomfortable,” was standard of care [10, 11].
First, a core support team was identified and trained on a reduced staffing model (one scrub, one circulator) using our robotic platform’s training paradigm. Training sessions were held with robotics company staff and our surgeon champion at night. We frequently held training sessions at 05:00 AM, at the end of the surgeon champions on call shift, when the operating rooms were the least busy, and when the OR staff was the least likely to be involved in another case. We trained on a “reduced staffing model,” in which we would staff each room with a circulator and a scrub nurse. Scrub nurses were trained to exchange instruments, to facilitate the resident’s ability to sit at the console.
Once we felt that the staff had completed the necessary training steps, we aligned the staff with the call schedule for the robotic trained surgeons. The first twenty cases were supported by an on-call robotic representative. If we identified a robotic case after hours, our representative would come into the hospital and help the trained staff set up the case. S/he would then stay for the case, and we would all conduct a post-case debrief to address perceived challenges that arose during the case. Over the course of three months, we no longer need any participation from our training representative.
Once the core support staff team had been trained, additional staff were added to the team. The goal was to have all staff trained in a short time interval. As our robotics program has matured at our institution, we now consider robotics training a core competency amongst our operating room staff, similar to laparoscopy.
Lesson Five: Changing Culture
As our program began to develop, we realized that we also needed to focus on changing our culture to one that was robotics forward. It is not an understatement to say that cultural change was clearly the most demanding, and time-intensive, phase of our implementation. The transition to RASC-P had an effect on everyone involved in the cases, including anesthesia teams, OR staff, and residents. Open and honest communication were keys to solving these issues. Education was provided on the benefits of the program to all staff, and we identified several “halo cases” that could be utilized to celebrate wins and rapidly educate naysayers about our successful patient outcomes. Expectations were set about the case length as everyone progressed through the learning curve and, using objective data, showed that case times were decreasing as our program matured. Through leadership, education, and communication, we were able to start to change the culture to be more accepting of ACS robotics.
Lesson Six: Learning Curve Proctoring
After the implementation of the RASC-P, we then were tasked with the training of additional ACS surgeons beyond our core robotic surgeons in order to expand the program. The dilemma was in identifying a way to proctor surgeons who did not have a reliable volume generated through an elective practice.
Now with the better understand of the process, we focused on shortening the length of time that the S-curve required. First, each surgeon attended a robotics training course. Immediately following this training, they took a week of daytime ACS call in order to have daytime access to the robotic system while other robotically trained surgeons were available to assist. All non-urgent cases were funneled to the training surgeon for “touches: during regular hours when they could be proctored and educational resources were optimal. With careful planning and coordination, we were able to successfully proctor new surgeons without a true elective practice.
The other challenge was learning how to simultaneously train residents, as the attending surgeons were progressing through the learning curve themselves. This process took humility, as attendings and residents learned together and from each other. Residents and attendings were provided a pathway to independence and skill development by using inguinal hernia, appendectomies, and cholecystectomies as gateway procedures. The importance of performing these procedures cannot be underestimated: they are used to develop robotic fundamentals, such as tissue handling and intracorporeal suturing. Dual consoles were used to guide teaching, and the residents could track their case progress with the technology integrated within the platform.
Lesson Seven: Leverage the Technology
The final lesson we learned while building our RASC-P was how to use the platform’s integrated intelligence system to facilitate ongoing resident and attending education. Our robotics system has many platforms available for education and a safe progression to mastery, including learning modules, procedural and technical simulation, video recording, and an app which allows users to track case times and efficiencies. By using the objective data inherently available in these systems, we have been able to flatten the learning curve for trainees and continue to hone robotic skills for trained surgeons.




Comments (0)