
Remember me

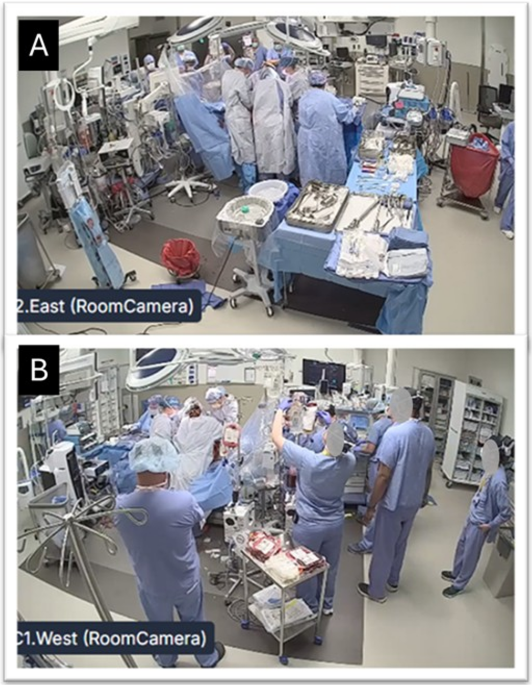


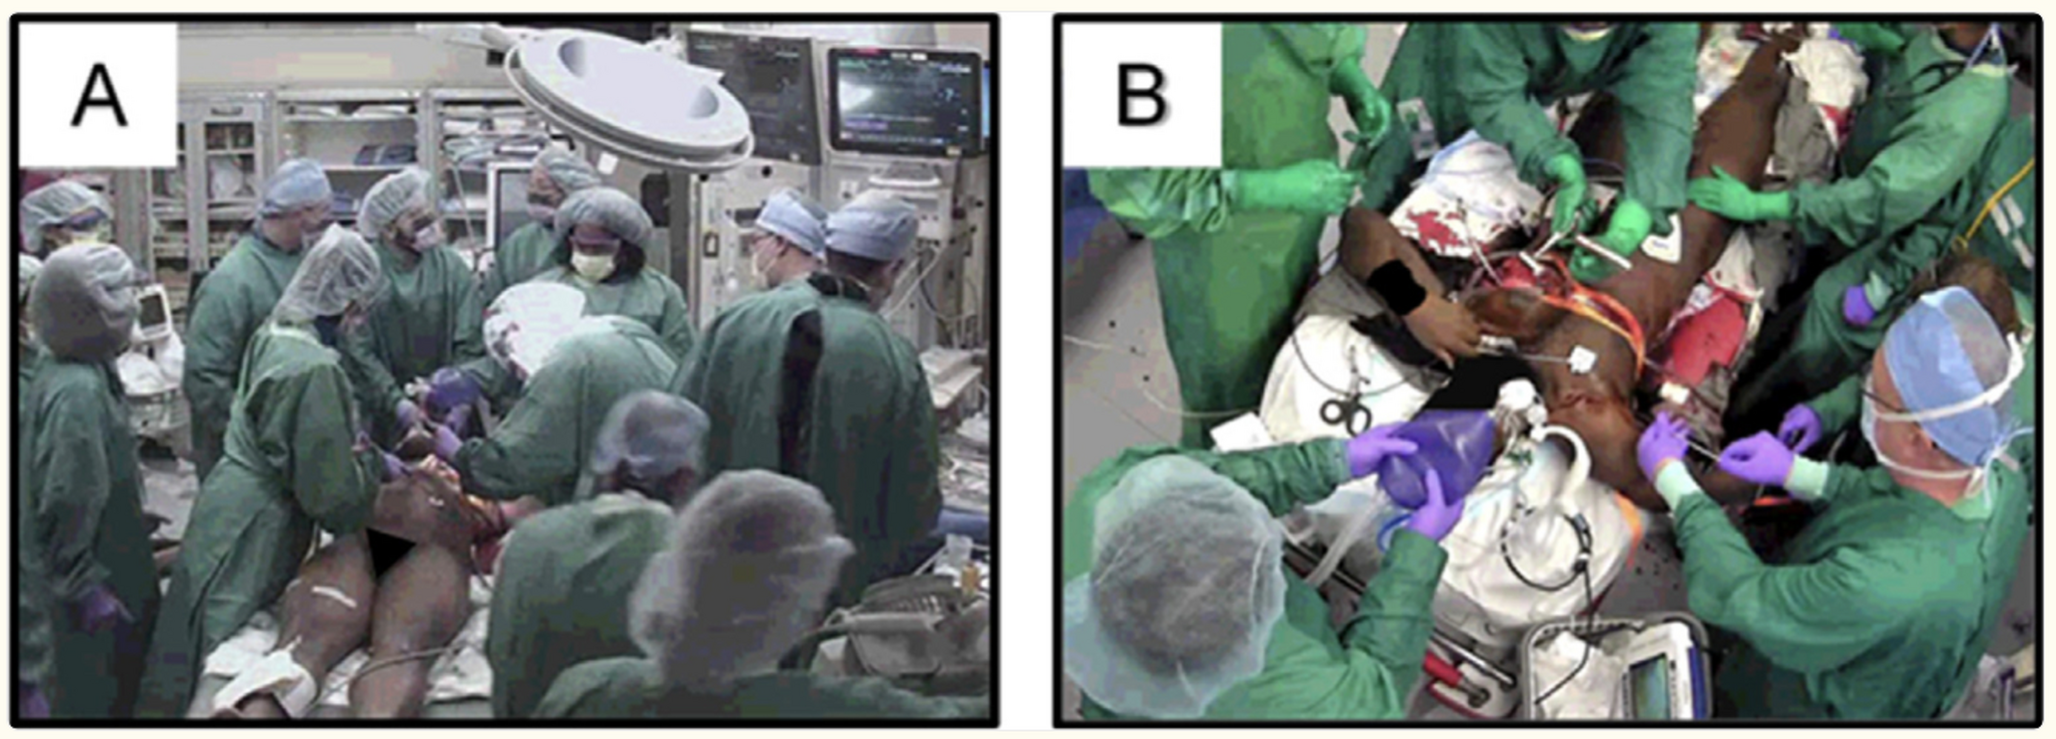
Multiple prior studies have demonstrated that ED TVR is an invaluable tool for assessing NTS in the resuscitation bay, but fewer studies have been published in the OR space. IOTVR can be a powerful tool employed in ‘meta QI’; that is, identifying opportunities to improve the quality of existing QI processes. As an example, a typical IOTVR program might utilize wall-mounted cameras and microphones to capture data on non-technical aspects of operative care, such as the communication occurring upon patient arrival between the anesthesia and surgical teams at the foot of the bed (Fig. 1.A) and communication occurring between the scrub nurse and the surgery team at the head of the bed (Fig. 1.B). A recent study using IOTVR to examine ED to OR handoffs in trauma surgery found that despite the presence of a standardized 18-point trauma anesthesia checklist, teams consistently verbalized only a fraction of the required elements, demonstrating not only opportunities for improving ED to OR handoffs but also for enhancing the tools used to perform these handoffs themselves [19]. IOTVR has also been used to evaluate OR readiness for emergent trauma surgery, a key but often overlooked determinant of timely operative intervention. In a review of 53 consecutive trauma operations over an 8-week period, researchers used video to measure room setup and equipment readiness prior to patient arrival. While setup times and preparedness were generally high, the study found important variability in equipment availability, especially with items like patient warmers and video laryngoscopes [20]. Another IOTVR-based study introduced the OR door-to-incision time (orDTI) metric to evaluate preoperative efficiency in trauma surgery. Despite nearly half of patients presenting with hypotension or massive transfusion protocol activation, median orDTI was ~ 17 min, revealing a disconnect between clinical urgency and operative workflow. These findings underscore how IOTVR can pinpoint delays in team coordination or procedural readiness, offering a concrete target for process improvement in hemorrhage control timing [21].
Fig. 1
Example of how IOTVR-derived data can support non-technical skills education: intraoperative field footage showing communication during patient arrival to the operating room between the scrub nurse and surgical team at the foot of the bed (A), and between the surgical and anesthesia teams at the head of the bed (B)
EducationVideo-based surgical coaching is emerging as a promising method to enhance operative performance by enabling structured, objective feedback [22]. With respect to technical skills, in a non-clinical analog of IOTVR, a study using head-mounted cameras to record surgical residents performing open trauma procedures on cadavers demonstrated that video review is a valid tool for assessing technical performance in trauma training [23]. For education surrounding operative trauma, IOTVR can serve as the data source for coaching sessions with residents and fellows or in multidisciplinary trauma rounds. A recent study of a large-scale video education program used handheld and head-mounted cameras to record > 250 open trauma surgeries, creating more than 1,000 h of video for resident education. The program demonstrated that high-fidelity intraoperative recording is feasible with minimal disruption and helps address the declining exposure to operative trauma cases in training [9].
Video of the operative field can be synchronized with real-time vital sign data to contextualize the pace, precision, and technical quality of intraoperative actions in relation to the patient’s physiology, further enhancing IOTVR’s role in education. Most trauma surgeons will at some point be called upon to operatively manage a patient with pericardial tamponade- a relatively rare event at many centers but nevertheless a high-impact clinical scenario. However, due to its low frequency, many trainees complete their surgical education with little to no hands-on exposure to this condition, leaving them underprepared when faced with it in practice. IOTVR offers a valuable tool to bridge this training gap. For instance, synchronized footage can show the operative view of a tense pericardium while an arterial line tracing displays the hallmark equalization of systolic and diastolic pressures (Fig. 2.A). As the surgeon opens the pericardium and relieves the tamponade, the video captures the immediate normalization of blood pressure (Fig. 2.B), vividly linking the technical action to its physiological effect - something rarely appreciated in real time during a high-stress emergency. IOTVR can be used to create a high-fidelity, low-stress environment for reviewing these critical moments. Freed from the pressure of actively caring for a dying patient, trainees can revisit and reflect on complex operative decisions and their physiological consequences. This allows for deeper understanding of surgical reasoning, timing, and technique allowing for reflection and processing of information in a way that real-time participation often cannot.
Fig. 2
An example of how IOTVR-derived data can be used for technical skills education: intraoperative field footage at sternotomy and real-time vital signs data, including heart ECG tracing, arterial line waveform, and oxygen plethysmography, recorded before (A) and after (B) pericardial incision in a patient with traumatic pericardial injury due to blunt cardiac rupture
ResearchWhile IOTVR has been explored for education and quality improvement, there are currently no published studies using IOTVR data for formal research purposes. This distinction is important: QI efforts aim to enhance internal processes and patient care within a specific institution, often under the protection of hospital quality improvement frameworks. In contrast, research seeks to create generalizable knowledge that can be applied across institutions and populations and typically requires formal Institutional Review Board (IRB) approval.
As IOTVR adoption expands across institutions, the opportunity to leverage these recordings for research-grade datasets will likely grow. With larger sample sizes and standardized protocols, it may become possible to examine non-technical and technical skill variation across sites, paving the way for benchmarking studies and hypothesis-driven investigations to advance the science of operative trauma care.
One potential barrier to using IOTVR for research is the complex issue of informed consent. Intraoperative recordings are often captured under that aegis of quality improvement through hospital consent, but this is distinct from obtaining explicit consent for research use.
Some IRBs have taken the position that if recordings are collected under a QI framework, and if researchers later abstract de-identified, minimal-risk data from those videos (e.g., timing metrics, communication elements, team behaviors), the recordings may be treated analogously to electronic health records - that is, as an existing data source that can be used for research under a waiver of consent. This perspective hinges on the argument that the additional risk incurred through video data abstraction is minimal, particularly when the recordings themselves are rigorously safeguarded and not shared or re-identified.
As IOTVR programs mature, careful collaboration with IRBs will be critical to define ethical frameworks that protect patients while enabling meaningful scientific inquiry. Institutions considering research applications should prioritize transparent data governance, robust de-identification practices, and clear boundaries between QI and research workflows.
Comments (0)