
Remember me






The surgeon places the patient in the unaffected-side lateral position or floppy lateral position [14], depending on the presence of an additional anteromedial medial malleolar fracture, under general or epidural anesthesia, with a tourniquet applied. A longitudinal skin incision is made along the posterolateral border of the fibula, extending sufficiently distally to expose the distal fibula and posterior–lateral aspects of the ankle. The region within 3 cm proximal to and distal to the fibular fracture site is exposed along the anterior aspect of the longus and brevis peroneus muscles. The fracture ends of the fibula are cleaned.
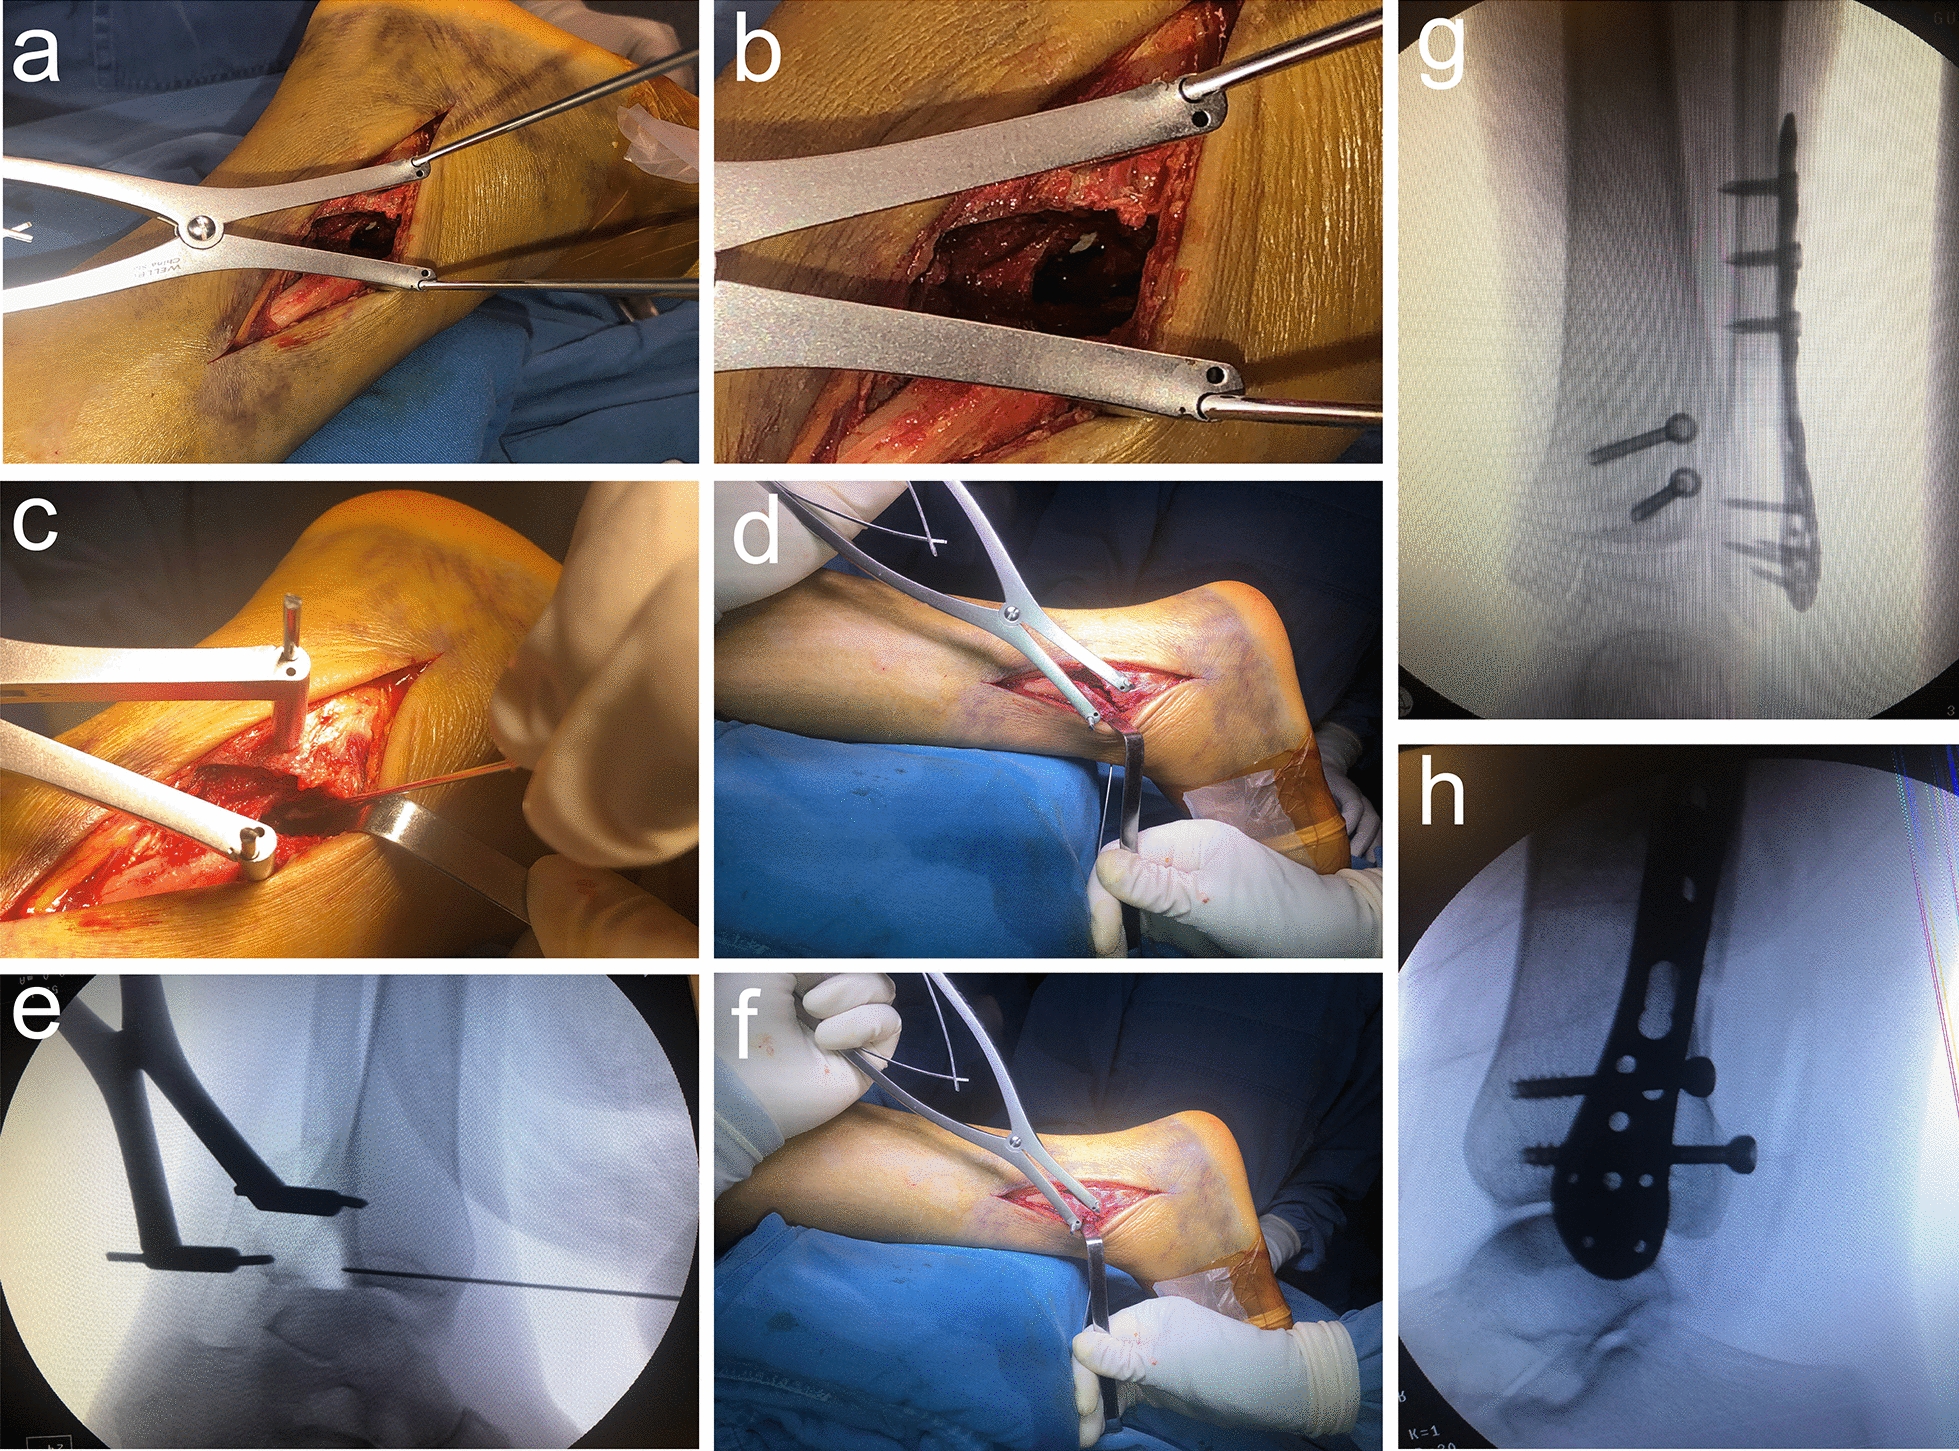
K-wires are placed proximal and distal to the fibula fracture to temporarily stabilize the fracture and allow proper reduction. The distal end of the fibula fracture is pulled backward with a K-wire spreader, to create a gap of approximately 1 cm × 1 cm (Fig. 1a,). The fractured posterior malleolus and impacted joint surface bone fragments are visible under direct view (Figs. 1b, 2a). The intercalary bone fragments are reduced by gently pushing the impacted joint surface back into place with a bone tamp (a tool used to apply gentle force) (Fig. 1c). Temporary fixation of the intercalary joint surface fragments is achieved using an anterior-to-posterior K-wire (Figs. 1d, e, 2b).
Fig. 1 Fig. 2

Schematic of surgical procedure
The fibular fracture is reduced and fixed with an anatomical or reconstruction plate (Fig. 1f, 2c). The space between the peroneus brevis and flexor hallucis longus muscles is dissected, and care is taken to avoid damaging the sural nerve and small saphenous vein. The flexor hallucis longus muscle is retracted medially. The peroneus longus and brevis muscles are retracted laterally to expose the posterior malleolar fragment. Reduction of the posterior malleolar fracture is achieved by cortical alignment (Fig. 2d). After reduction, buttress plates or screws are used for fixation. If there is a concurrent anteromedial medial malleolar fracture, the patient in the floppy lateral position is then rolled more posteriorly with the operative leg in external rotation. The medial malleolar fracture is reduced through a medial incision and fixed with screws.
After fracture fixation, satisfactory reduction is confirmed using a C-arm X-ray machine under fluoroscopy (Fig. 1 g, h).
Posteromedial approachThe posteromedial approach utilized in this cohort was originally described by Assal et al., being referred to as the modified posteromedial approach [2]. The patient is placed in the prone position under general or epidural anesthesia, with a tourniquet applied. The knee is flexed and internally rotated. Initially, a posteromedial approach is used. A 6-cm curved incision is made along the posterior medial edge of the Achilles tendon, extending to the medial malleolus. Care is taken to avoid damaging the deep layer of the posterior triangle ligament at the distal end of the incision. The deep fascia is incised, to expose the tibialis posterior retinaculum. The posterior tibial tendon is retracted posteriorly, and soft tissues are dissected along the posterior edge of the tibia. The contents of the tarsal tunnel are retracted posteriorly to expose the posterior malleolus. The posterior fragment is elevated distally, and intercalary articular surface compression fragments are visible. The intercalary fragments are reduced and temporarily fixed in place using K-wires oriented anterior to posterior.
A lateral approach to the lateral malleolus is then performed. The methods used to reduce and fix the lateral malleolar fragment and posterior fragment are the same as those used in the TFFR approach. If there is concurrent medial malleolar fracture, the medial malleolar fragment is reduced through a medial incision and fixed with screws.
Postoperative managementAll patients received standard postoperative management. Passive and active motion of the ankle was encouraged starting from the second day after surgery, as long as pain was tolerable. Patients were allowed to walk with axillary crutches 2 weeks after surgery, but weight bearing was not allowed until 8 weeks post-surgery. Permission to return to work depended on three-dimensional reconstructive CT and clinical signs of healing, usually 12 weeks after surgery.
Evaluation of clinical outcomesPostoperative follow-up was conducted through scheduled outpatient visits at 1-, 2-, 3-, 5-, 8-, and 12-month intervals, with subsequent annual remote evaluations. X-ray examination was performed preoperatively; on postoperative day 2; and at the 1-, 2-, 3-, and 12-month follow-up intervals. Computerized tomography (CT) examination with three-dimensional reconstruction was performed preoperatively, immediately post-reduction, and 3 months postoperatively. Clinical outcomes were assessed over an average 8 year follow-up. The surgical duration, intraoperative fluoroscopy times, and postoperative complications were recorded. The time to fracture healing and full weight bearing were observed. Functional outcomes were evaluated via the Foot and Ankle Outcome Score (FAOS), Foot and Ankle Ability Measure (FAAM), and Short Form-36 (SF-36) at last follow-up.
Statistical analysisStatistical analysis was performed using the Statistical Package for the Social Sciences 26.0 software (SPSS; IBM, Armonk, NY, USA). Descriptive statistics (means and standard deviations) are used to summarize the data. p-Value < 0.05 was considered statistically significant. Normality of the data was assessed using the Shapiro–Wilk test, and differences between groups were compared using Student’s t test for continuous variables and the χ2 test for categorical data.
Comments (0)