This systematic review and single-arm meta-analysis pooled PANQOL HRQoL scores for patients with unilateral VS managed with W&S, SRS or MS. Overall, patients managed with W&S had a pooled PANQOL total score of 69.1, those managed with SRS scored 66.9, and patients undergoing MS had a pooled PANQOL total score of 61.3. Importantly, differences in total and subdomain PANQOL scores across W&S, SRS, and MS did not exceed the established MCIDs, indicating no clinically meaningful differences in HRQoL and suggesting that outcomes are broadly comparable across treatment modalities.
However, these findings should be considered in the wider context of tumor management and clinical decision-making, where HRQoL outcomes are only one of several important factors. At first glance, it may appear counterintuitive that W&S yields HRQoL outcomes comparable to those of active interventions, such as SRS and MS. However, this should not be interpreted as a lack of therapeutic benefit of active treatment. PANQOL primarily captures symptom burden and functional impact rather than tumor control. Moreover, treatment decisions should not be based solely on HRQoL scores; rather, they must integrate the effectiveness of each management strategy in terms of tumor control, the risks associated with each treatment, including the risk of mortality, treatment-related morbidities, and the potential long-term impact on HRQoL. A comprehensive evaluation of these factors is essential to ensure that patients receive the most appropriate care. Given the complexity inherent in these decisions, shared decision-making is crucial. Clinicians must engage in thorough, transparent, and individualized counseling with patients, providing them with a clear understanding of the potential benefits and risks of each treatment option. This collaborative process is vital for aligning treatment decisions with the patient’s values, preferences, and clinical circumstances, thereby optimizing the selection of the most suitable therapeutic approach.
Nevertheless, the interpretation of pooled PANQOL scores requires caution, given the substantial heterogeneity observed across studies, with I2 values exceeding 75% in all analyses. This heterogeneity is likely explained by several factors. First, many included studies had a cross-sectional or retrospective design, often lacking power calculations, and failing to report the timing or rationale for initiating treatment. These designs also precluded baseline PANQOL scores and the opportunity to evaluate the change in PANQOL scores during follow-up following W&S, SRS, or MS. Second, variability in patient populations—including tumor size, Koos classification, age, comorbidities, and overall health status—and reporting those may have affected both baseline HRQoL and the impact of treatment. Third, patient and clinician preferences, as well as geographic differences in treatment approaches, likely influenced management choice and outcomes [38]. Finally, differences in response rates, influenced by whether questionnaires were administered in-hospital, online, or via post, may have introduced further variability in reported outcomes [39, 40].
Taken together, these sources of heterogeneity highlight the challenges of synthesizing HRQoL outcomes across diverse study designs and populations. Despite this heterogeneity, pooling of PANQOL scores was methodologically warranted using a random-effects model, which accounts for both within- and between-study variability. This approach allows synthesis of treatment-specific PANQOL outcomes, integrating variability in patient populations, tumor characteristics, and management delivery—including surgical approach, radiosurgery protocols, and follow-up schedules—thereby providing pooled estimates that meaningfully reflect the impact of each management strategy on HRQoL despite the observed heterogeneity.
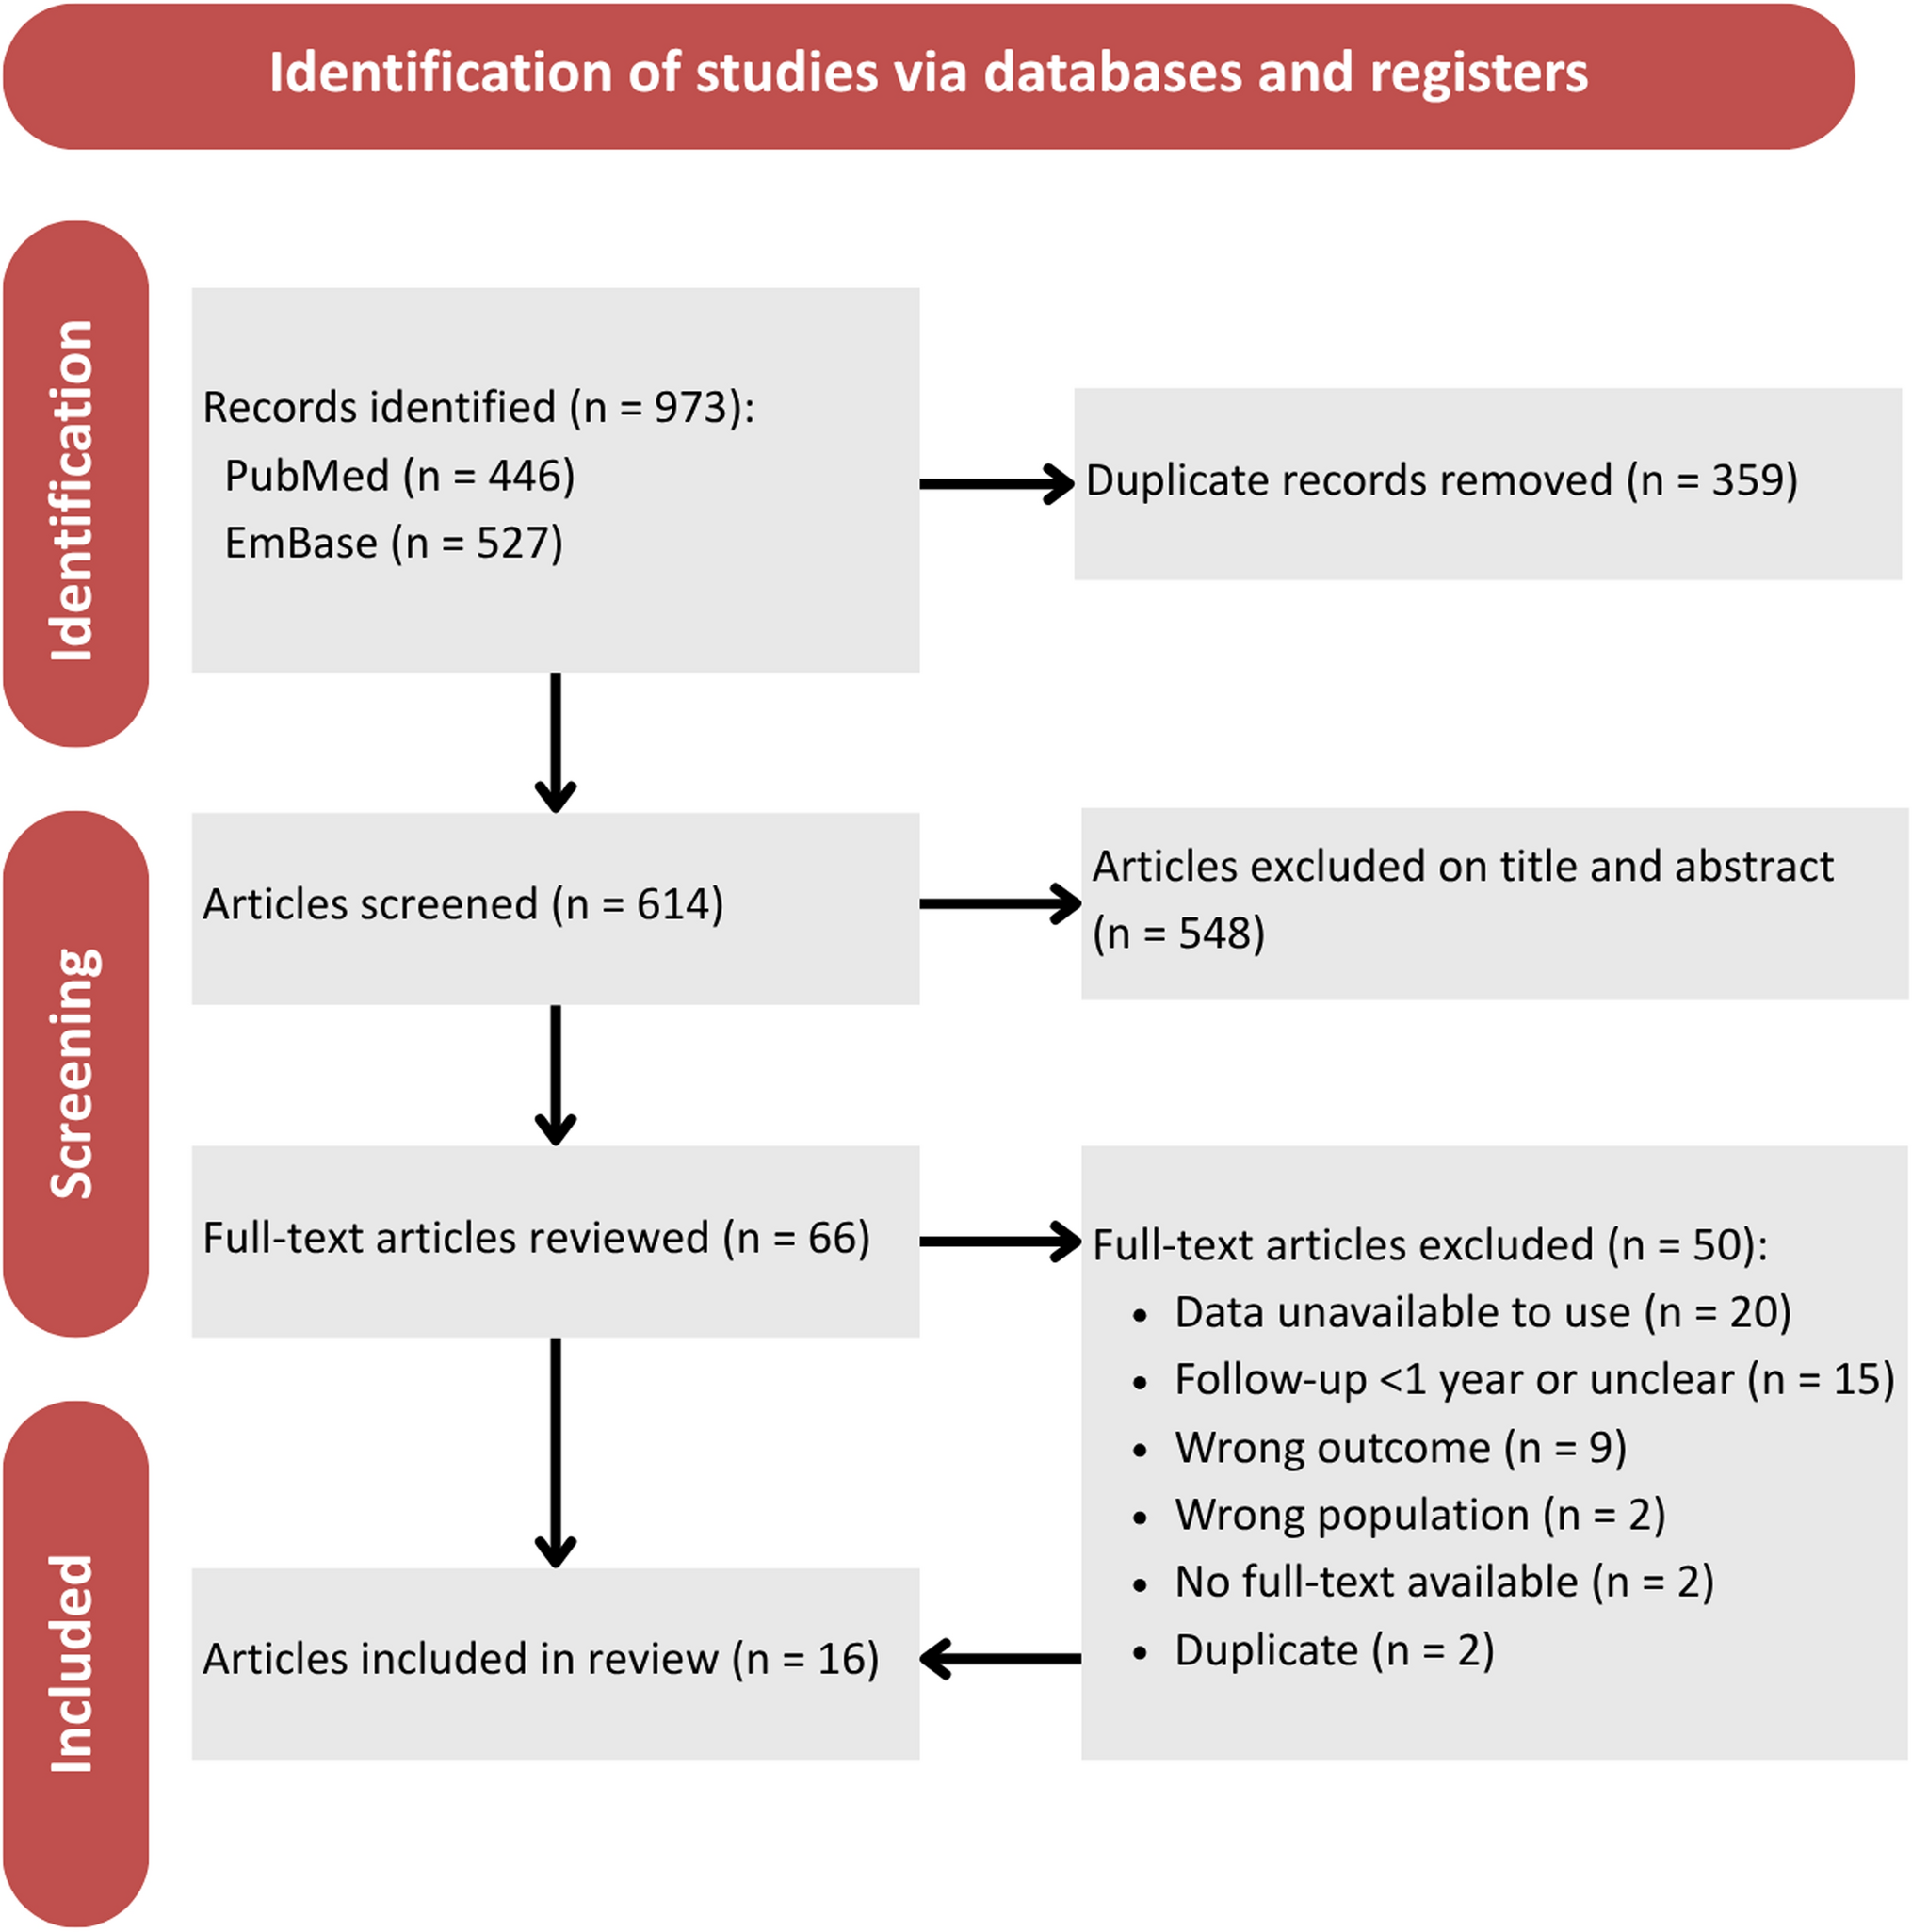
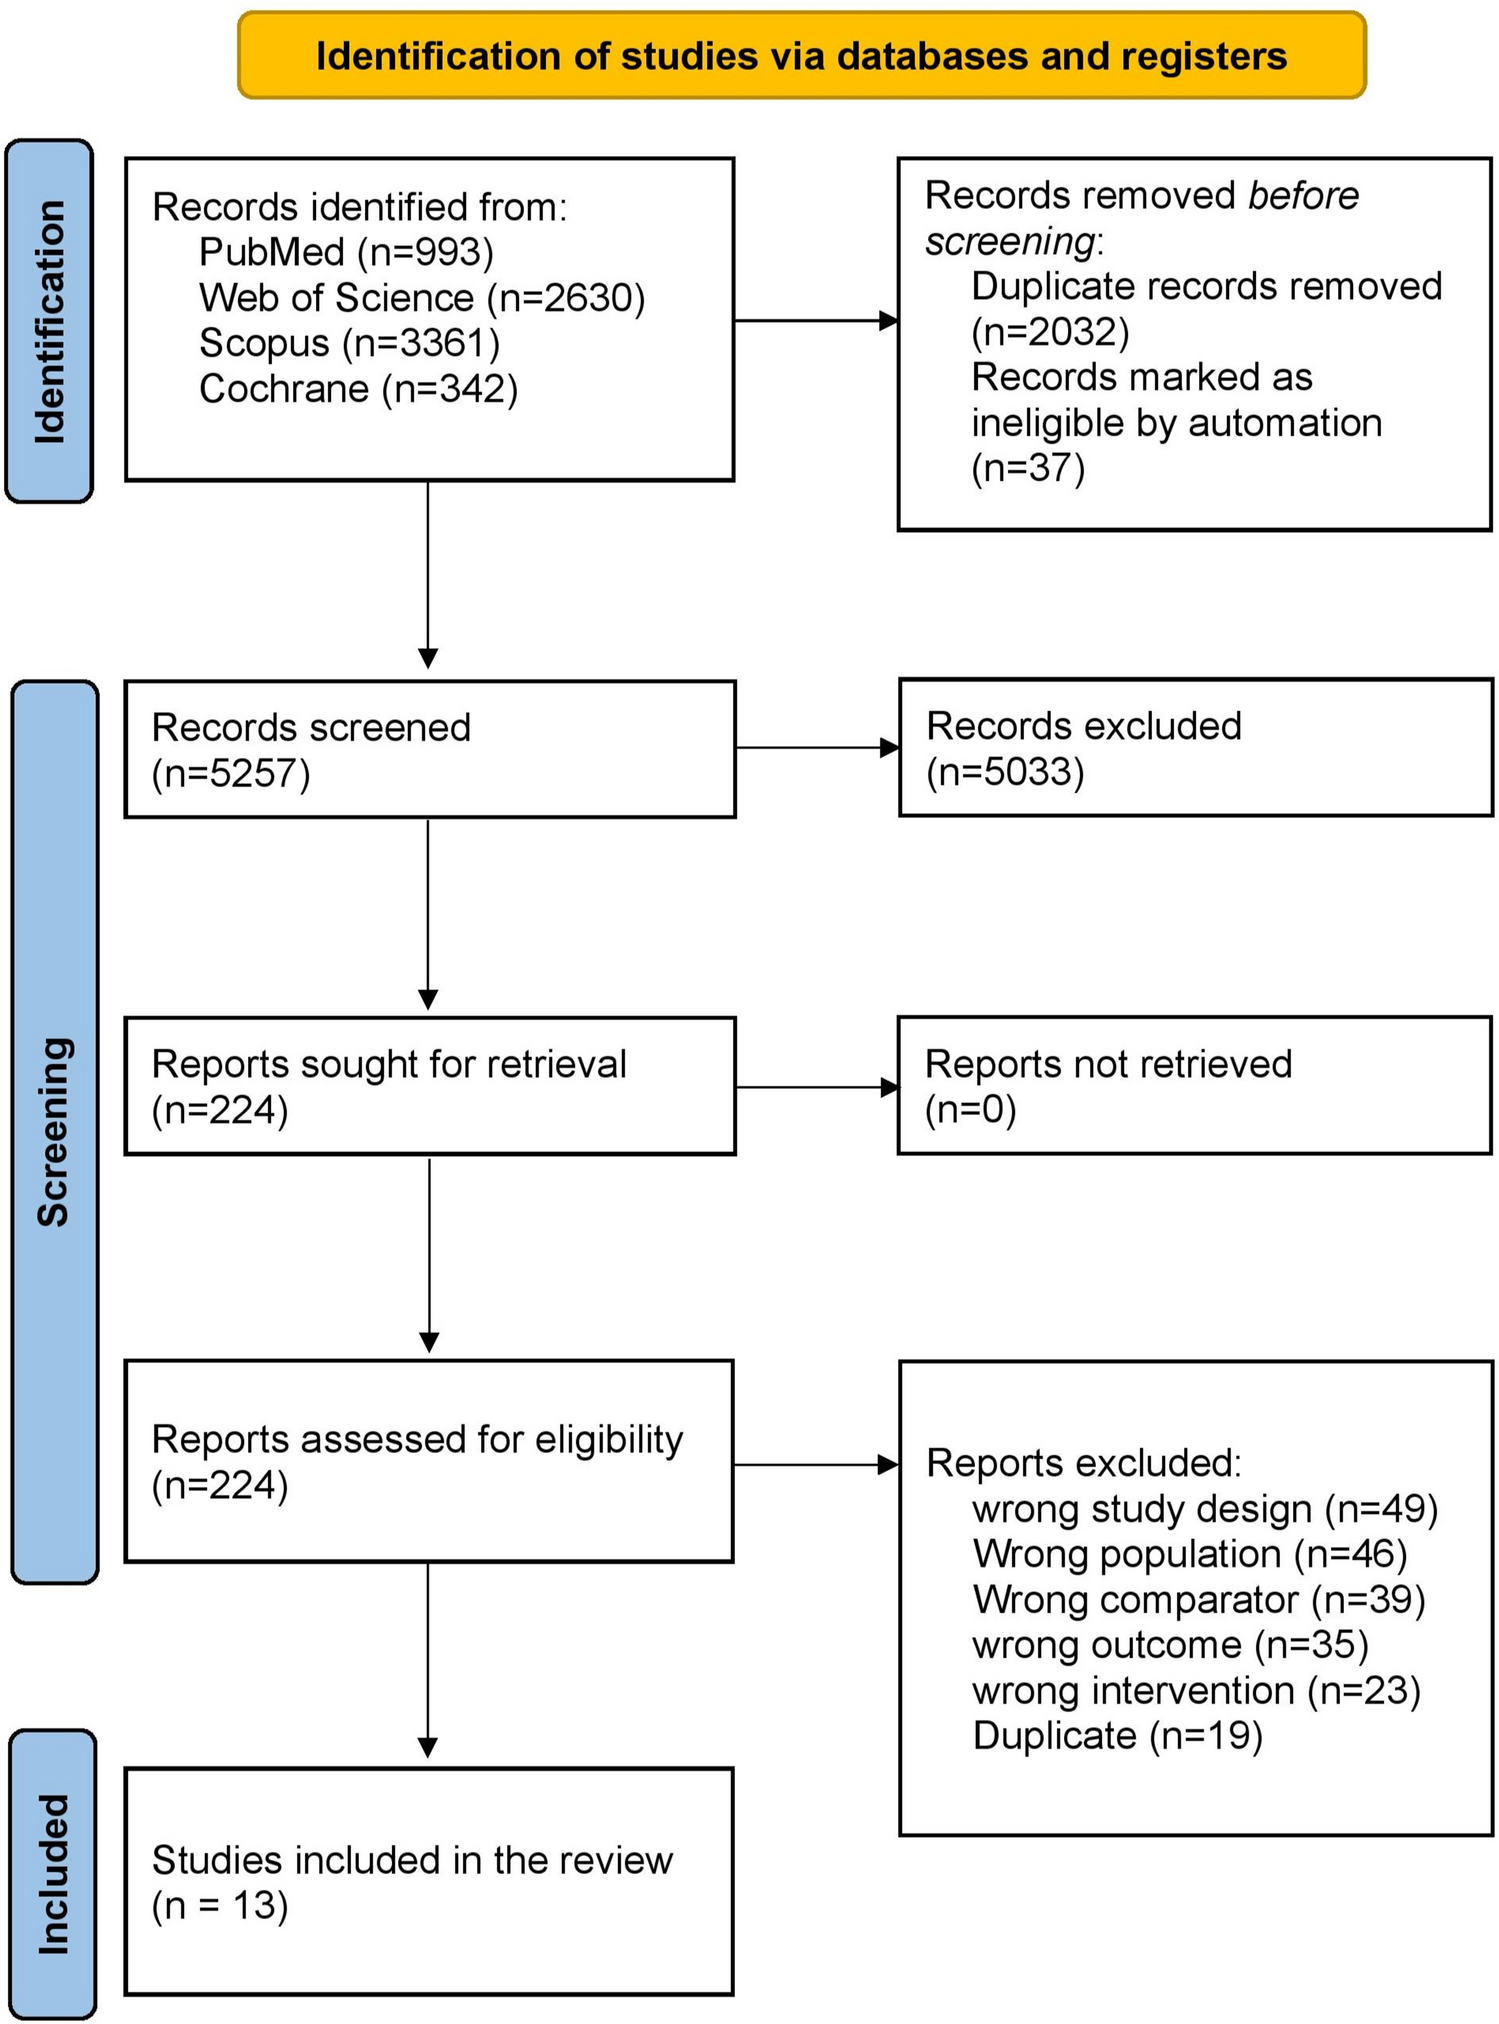
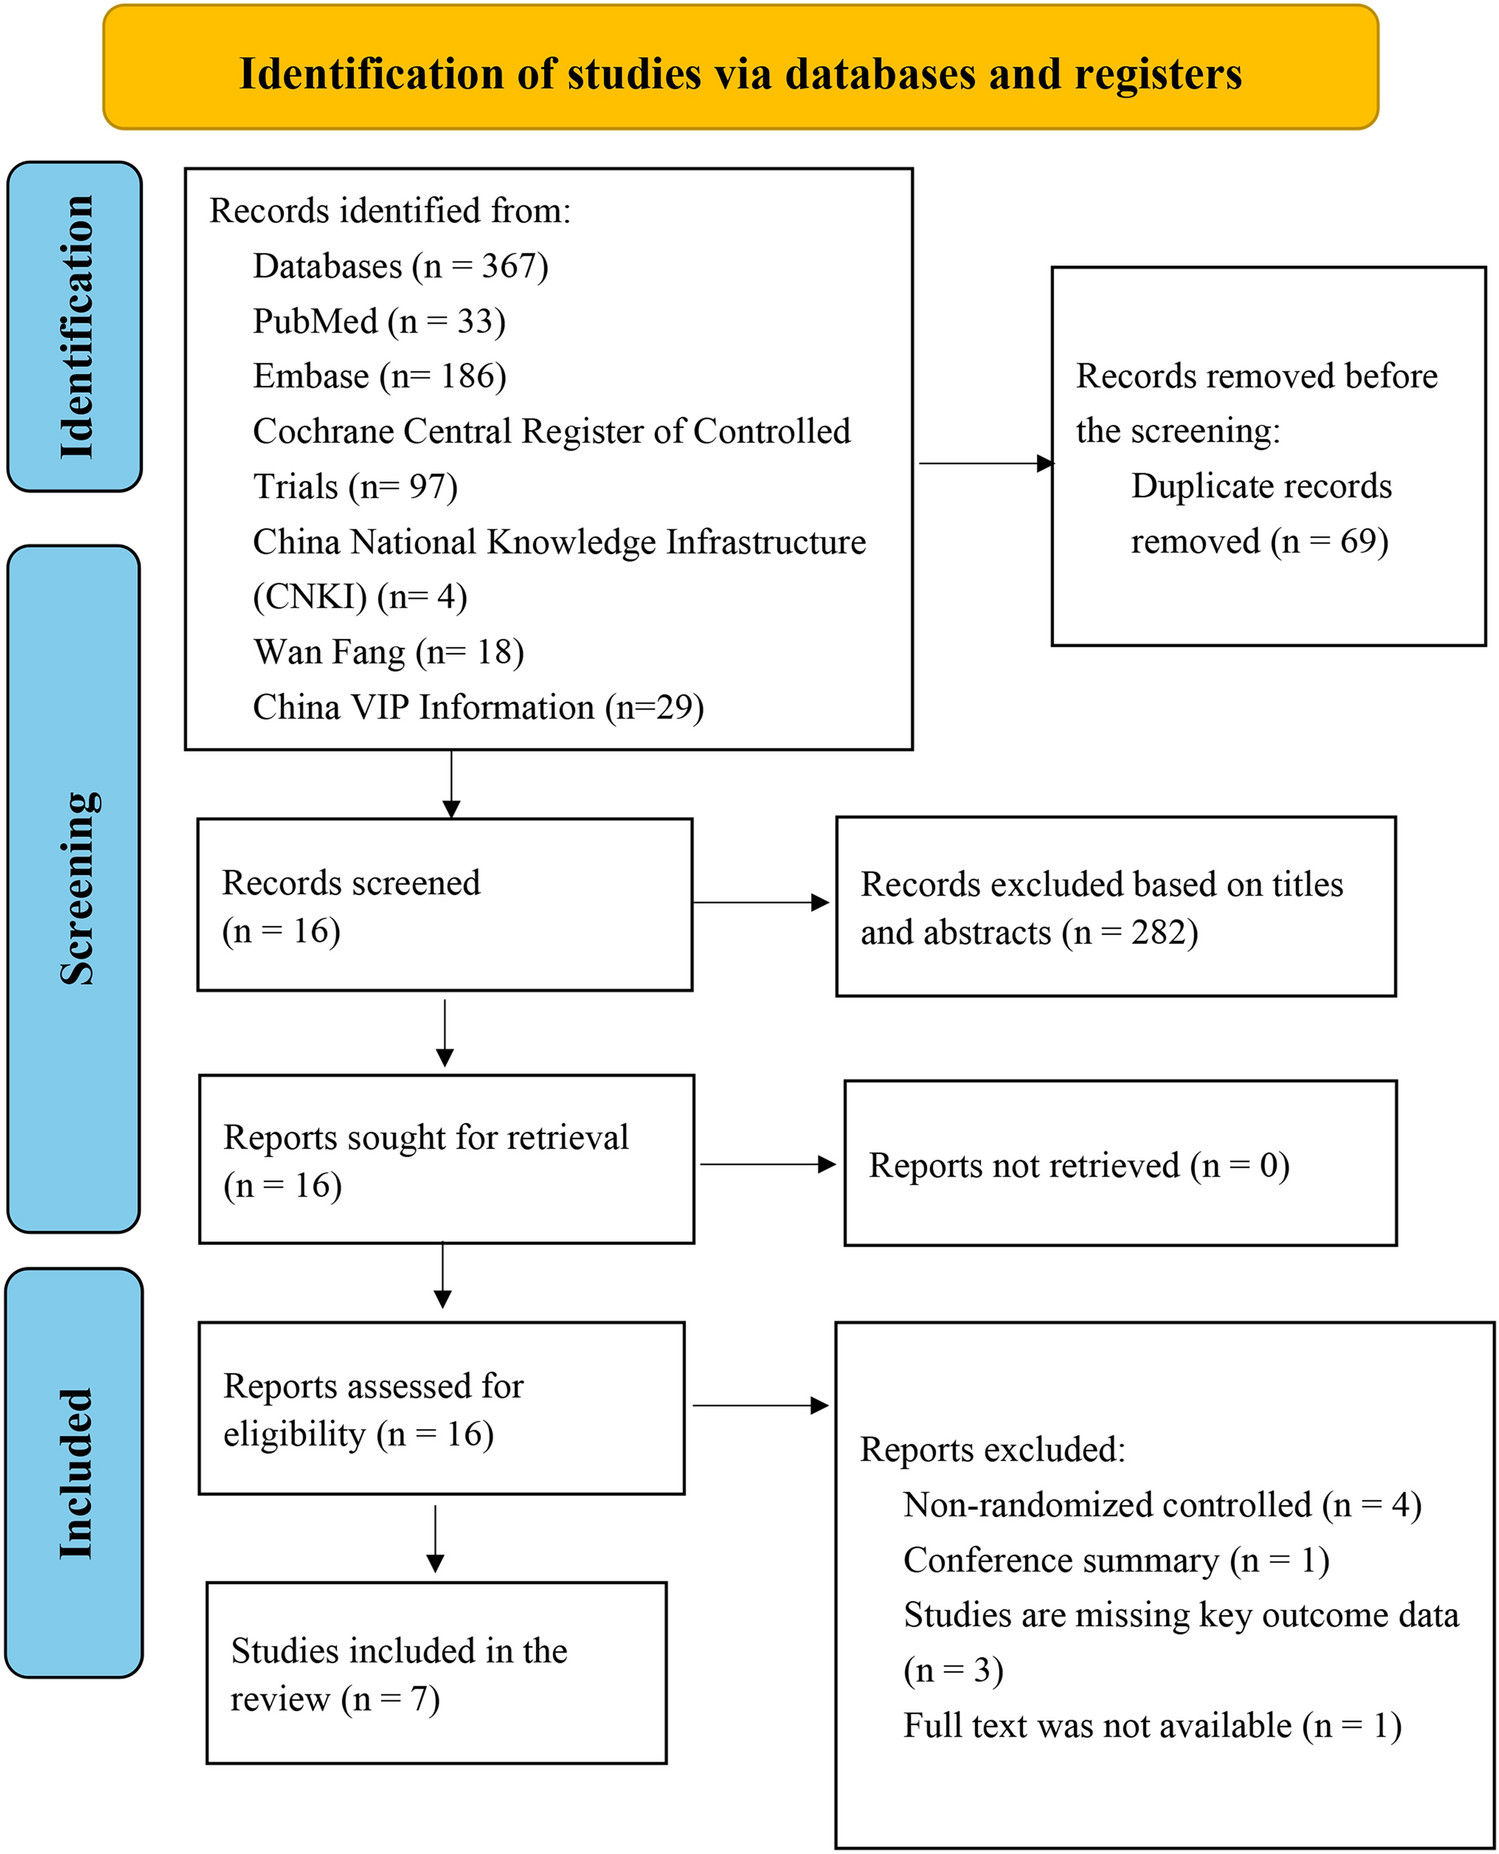
In addition to this variability within the included literature, several methodological considerations also limited the number of studies eligible for inclusion in the meta-analysis. The V-REX study [41], for example, which is a RCT, was excluded because it used an intention-to-treat (ITT) analysis, which is particularly useful in reflecting real-world clinical scenarios. In clinical practice, patients often switch between treatments or discontinue their assigned therapy, and ITT analysis captures this variability by including all patients as initially assigned, regardless of whether they complete the treatment as planned. This allows for a more realistic estimate of the overall effectiveness of the treatments. However, in the context of this meta-analysis, we sought to isolate the effects of the treatments as per protocol, to better understand the specific outcomes of each treatment modality, and to minimize confounding from therapy switching or discontinuation. As nearly half of the patients in the V-REX study (44%) switched from W&S to active treatment, the HRQoL results were difficult to interpret in the context of actual management strategies when viewed through the lens of ITT. Furthermore, multiple studies with larger cohorts and longer follow-up periods could not be included because they did not report, but only visualized, PANQOL scores, and attempts to obtain these data from the authors were unsuccessful. Studies that lacked measures of variability (SD, IQR) or reported PANQOL outcomes stratified according to other factors (for example, hearing) were similarly excluded, further reducing the available evidence base.
A further limitation of the included studies is the absence of PANQOL baseline scores, precluding meaningful assessment of within-group changes in HRQoL over time for each management strategy. Without baseline measurements, it remains unclear whether reported follow-up scores reflect true stability, improvement, or deterioration relative to pretreatment status. In addition, limited reporting on patients lost to follow-up—particularly the reasons for non-response—raises concerns about attrition bias. In patients who may experience greater morbidity as a result of their VS or treatment modality, HRQoL may be more severely impacted, potentially leading to non-completion of questionnaires. Therefore, these patients, who may represent the most clinically relevant cases, are often underrepresented in the final HRQoL scores. This could introduce bias and limit the generalizability of the findings.
Beyond these practical exclusions, there remains a more fundamental question regarding the ability of the current PANQOL instrument to capture true differences between management strategies. One could argue whether there actually are differences to be measured between management strategies, given that pooled PANQOL HRQoL scores show only small variations that do not exceed the MCID. This raises the question whether these differences are truly negligible or simply not captured due to limitations in the PANQOL instrument. The PANQOL equally weights all seven domains in calculating the total score, despite evidence that certain domains—such as energy, anxiety, pain, and balance—contribute more strongly to overall HRQoL than others like hearing or tinnitus [3, 4]. This uniform weighting may obscure clinically meaningful differences between patient groups or treatment modalities. The recently developed Vestibular Schwannoma Quality of Life (VSQOL) index [42], which includes additional domains, such as cognitive function, treatment satisfaction, and broader pain assessment, has been designed to capture a more comprehensive and nuanced view of HRQoL. Given its enhanced sensitivity and psychometric robustness, the VSQOL may be better suited to detect (subtle) clinically relevant differences in patient-reported outcomes that the PANQOL cannot fully reveal. Future studies employing the VSQOL could therefore determine whether subtle but clinically relevant differences exist between treatment strategies, ultimately supporting more informed, patient-centered decision-making.
This naturally leads to the broader issue of how the field can generate higher-level evidence in future. Ultimately, the highest level of evidence regarding HRQoL outcomes in patients with vestibular schwannoma would be obtained from meta-analyses of RCTs or rigorously controlled cohort studies directly comparing management strategies. However, such studies are exceedingly scarce, reflecting both ethical and practical challenges in randomizing patients to distinct treatment modalities in this population. An alternative approach could be a network meta-analysis, in which studies comparing different pairs of interventions—for example, W&S versus SRS and SRS versus MS—are synthesized to enable indirect comparisons across all three strategies. While this method has theoretical appeal, its validity depends on sufficient overlap in baseline patient, tumor and HRQoL characteristics across studies to satisfy the transitivity assumption. Moreover, network meta-analysis fundamentally relies on randomized comparative trials using a common comparator to construct the network, as randomization ensures that patients with similar baseline characteristics could theoretically have been allocated to any treatment arm across studies. Observational studies, including matched cohort designs, do not fully satisfy this assumption and therefore may introduce residual confounding if incorporated into the network. In the context of VS HRQoL research, such comparability is generally lacking, hence the high heterogeneity in this meta-analysis, limiting the interpretability of indirect comparisons. Given these constraints, single-arm meta-analyses remain the most feasible and methodologically defensible approach to synthesize existing data, providing valuable insights into patient-reported outcomes across treatment modalities while transparently acknowledging the limitations imposed by heterogeneity and study design.
Looking forward, strengthening the evidence base will require coordinated efforts to enhance data quality and comparability across studies. Future research should prioritize standardized collection and reporting of HRQoL outcomes, including the consistent use of validated instruments such as the PANQOL or VSQOL at baseline and during follow-up, complete reporting of measures of variability, and stratification according to clinically relevant factors, such as tumor size, treatment indication, and baseline patient, tumor, and HRQoL characteristics. Establishing a national database and fostering international collaboration would facilitate larger and more representative datasets. This, in turn, would enable individual patient data (IPD) meta-analyses, which are widely considered the most methodologically rigorous approach to evidence synthesis. By allowing direct access to raw, patient-level data across centers, IPD meta-analyses enable uniform data harmonization, adjustment for confounding variables, and exploration of subgroup effects that are not possible with aggregate data alone. Such an approach would substantially improve the validity and interpretability of comparative effectiveness research in vestibular schwannoma. Ultimately, the goal of these efforts is to generate high-quality, generalizable evidence that informs shared decision-making, helping patients to weigh the potential impact of different management strategies on their quality of life and to select the treatment that best aligns with their individual preferences and clinical circumstances.

Comments (0)