The findings of our exploratory study provide critical insights into the actual prevalence and impact of the second victim phenomenon (SVP) among anesthesiologists in Germany. To our knowledge, this was the first explorative systematic evaluation performed among German anesthesiologists focusing on the SVP.
Experiences with the second victim phenomenon: The majority (76.9%) of the anesthesiologists who completed the questionnaire reported at least one adverse event that led them to perceive themselves as second victims. This prevalence aligns with the findings of previous SeViD studies, including those studies that described perioperative catastrophes and their psychological consequences, without naming the HCP who experienced this a second victim [11]. In the SeViD III study, the prevalence of SVP was 53.1% among prehospital Emergency Medical Services (EMS) physicians, whereas it was 60% and 59% among German residents in internal medicine and nurses, respectively [5, 7, 16, 19]. In our cohort, the prevalence of SVP was much higher at 76.9%. Three reasons might explain the higher level of SVP. First, anesthesiologists perform different types of work. This may expose them more often to threatening incidents. On the other hand, the majority of the EMS physicians in the SeViD III study also worked in environments similar to those of an anaesthesiologist [5]. Second, SVP is better recognized as such; therefore, participants may be more likely to identify with effects that are better known and part of educational material. This hypothesis is supported by the fact that 52% of the participants were aware of the term SV, whereas in former studies, this knowledge about the term SV was much lower (10–25%) [7, 18]. Third, our study participants had a mean work experience of 21.5 years, which was greater than that in previous studies. Consequently, the probability of being involved in an incident associated with SVP might have been greater among these participants.
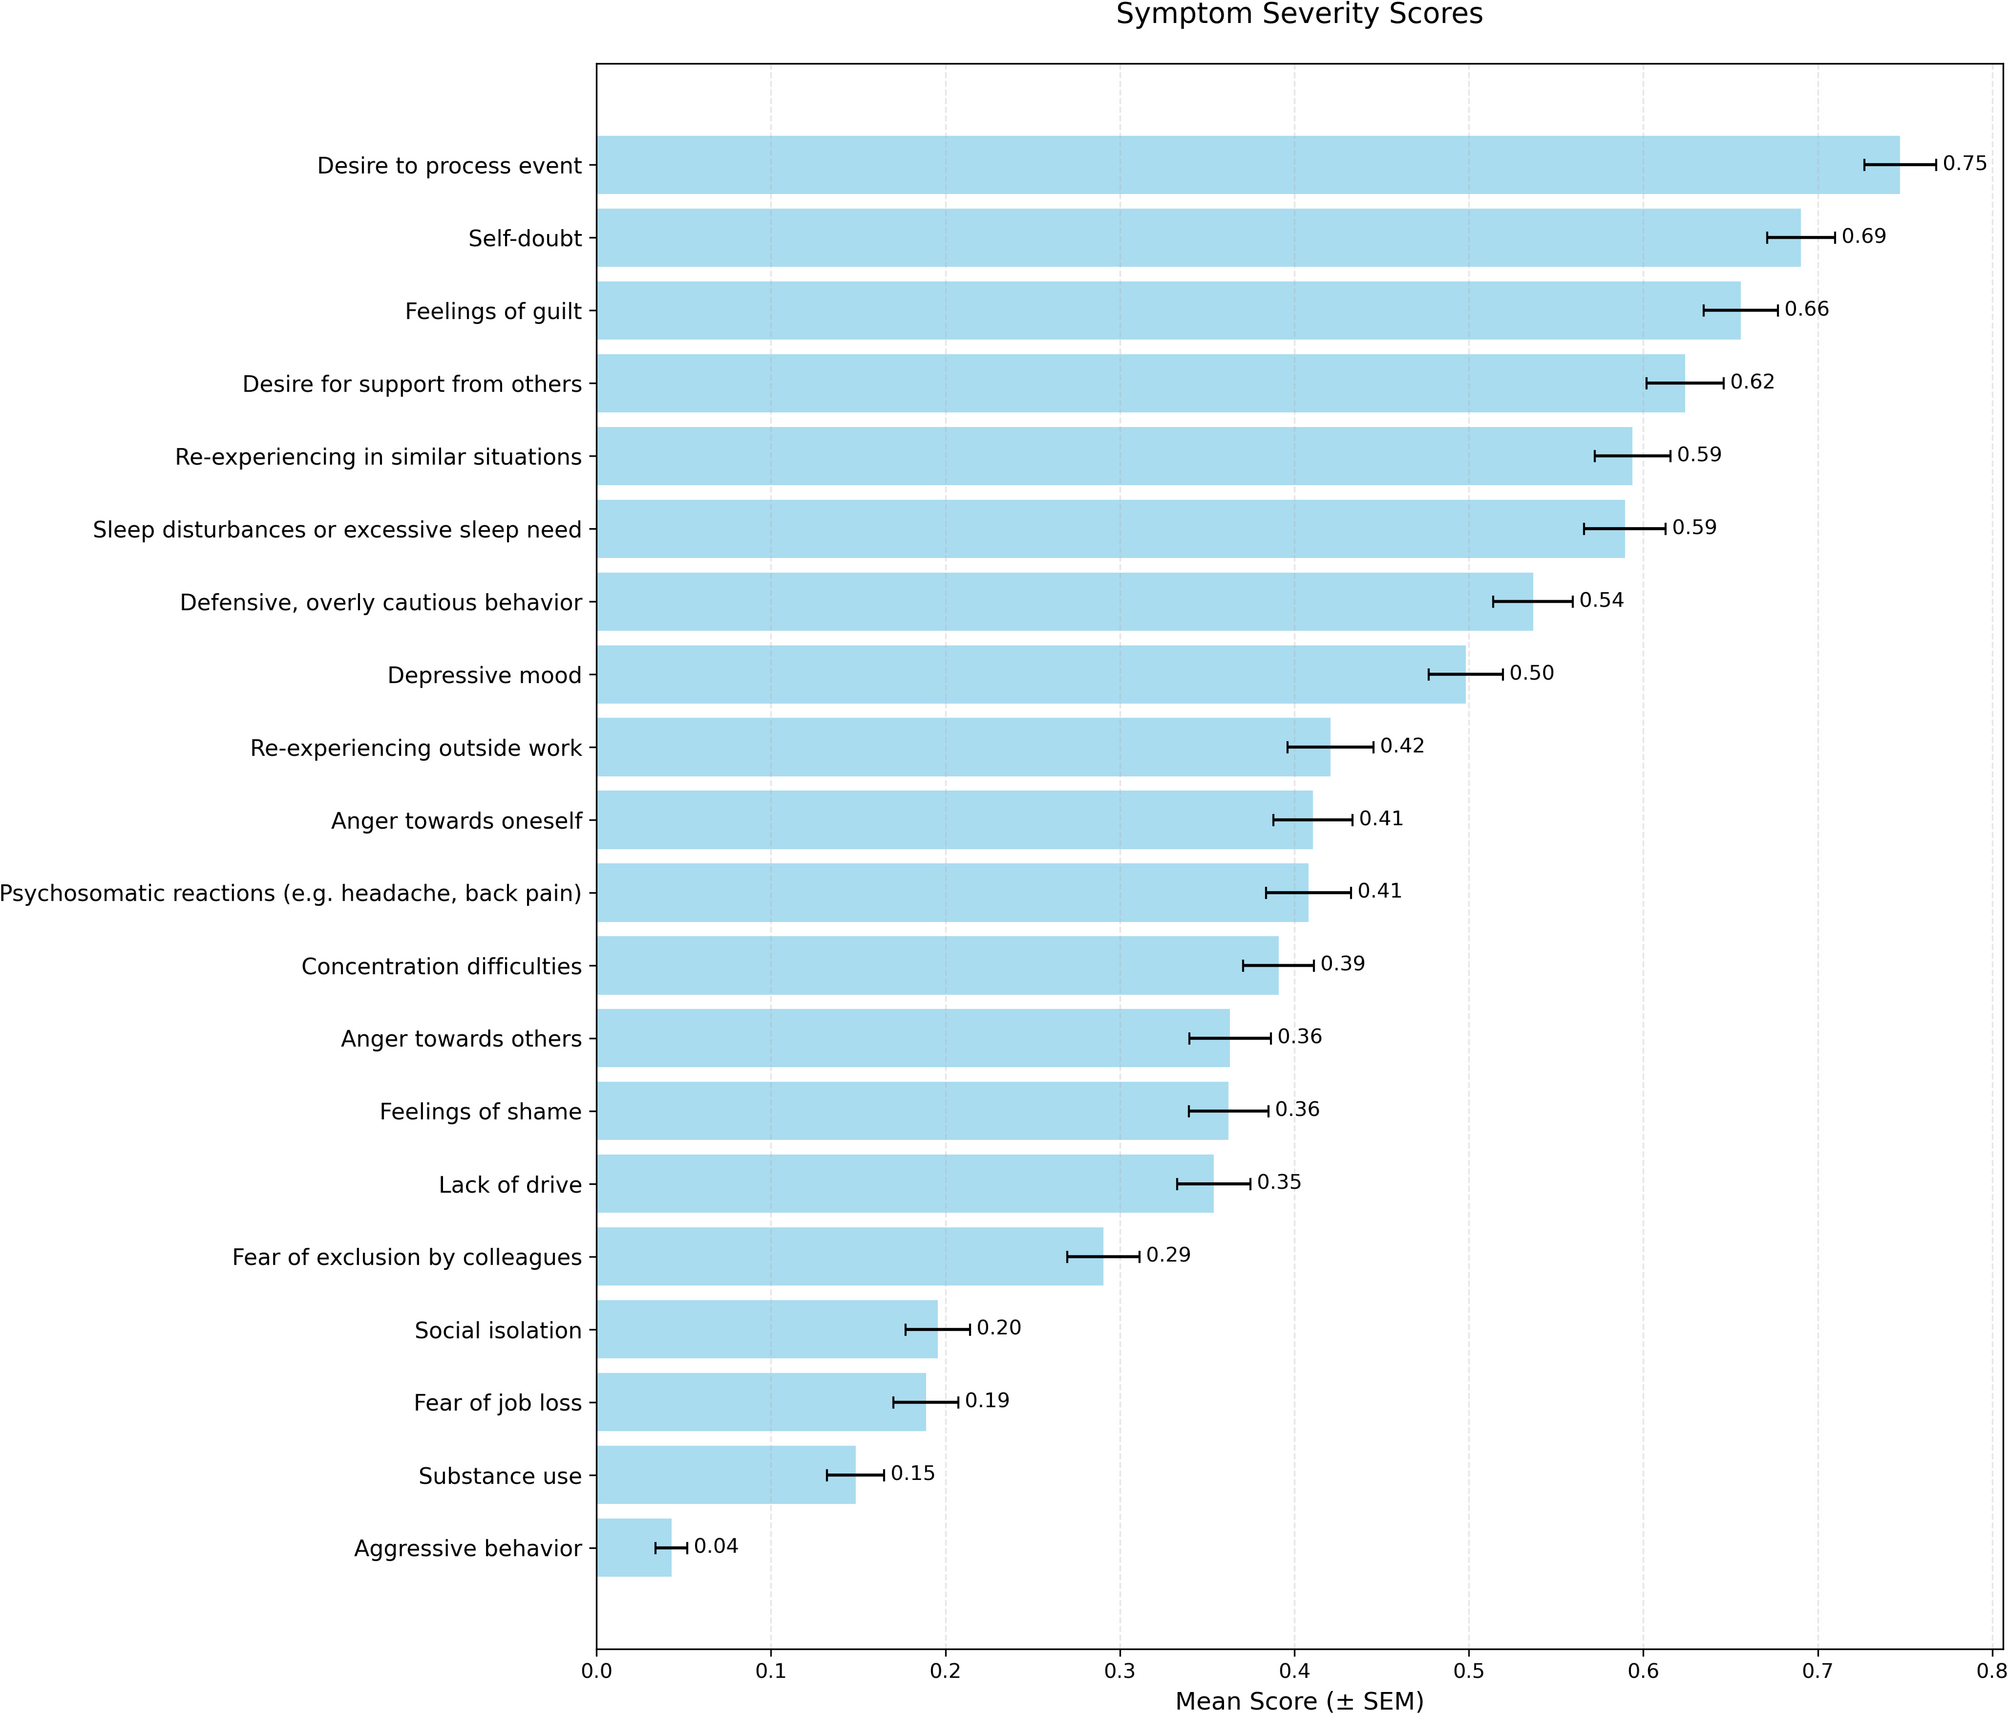
Time to recovery and burden of second victim symptoms: The burden of SVP was found to be substantial. For 46% of the participants, the recovery time was more than one month. 16% reported that they had not fully recovered, with the majority having experienced adverse events more than one year prior, indicating the long-term nature of the psychological impact. Common symptoms included reliving the situation in similar professional contexts, defensive or overly cautious behavior, sleep disturbances, feelings of guilt, self-doubt, and a strong desire for support and to understand the incident better. These symptoms are consistent with those described in other studies [8, 9, 21], underscoring that they directly affect the quality of the anesthesologists’ work and responsibility to their patients. In particular, sleep disturbances and defensive, overly cautious medicine might profoundly impact patient safety. These findings are reflected in the study by Gazoni et al., where 67% of the respondents stated that their ability to provide high-quality care was compromised for at least 24 h and 16% for more than one week [11]. In a recent small study by Ginzberg et al., surgical trainees were asked for their perceptions of the SVP. The majority, 85% of the affected trainees, reported experiencing embarrassment, 82% rumination and 65.4% fear of attempting future procedures. Additionally, 35.9% considered quitting [22]. These findings highlight the necessity of structured interventions to address the emotional and psychological needs of second victims [23, 24].
One concerning finding was the prolonged recovery time reported by many participants. More than half (56.9%) of those affected reported taking over a month to recover, and a significant proportion (16.2%) had not recovered at the time of their participation. However, no significant demographic or personality traits were found to influence recovery time, indicating that external factors, such as institutional support and workplace culture, may play a crucial role [25].
Compared with their younger colleagues, older anesthesiologists reported a greater symptom load, which could suggest an accumulative effect on the incidence rate over the years.
Risk and protective factors: The analysis of risk factors suggests that personality traits may influence an individual’s susceptibility to SVP. Extraversion and neuroticism were associated with a greater likelihood of becoming a second victim. Interventions targeting emotional regulation and stress management could therefore be beneficial in mitigating the psychological impact of adverse events.
Interestingly, neither age nor work experience significantly influenced the likelihood of becoming a second victim, suggesting that the phenomenon affects anesthesiologists across all career stages.
Second Victim Support Strategies: We asked all the participants to rate their support strategies. Interestingly, legal counselling was the highest-rated request, followed by contributing information to prevent further events, including prompt debriefing. These findings were in line with those of the former SeViD III study on EMS physicians [5]. In this case, in Germany, an excellent institution, the PSU-helpline© offers support via phone and email for all healthcare employees, managers, and peers who are experiencing SVP and stressful situations (www.psu-helpline.de). However, addressing only the top-rated support strategies is not sufficient and might lead us, in disastrous situations, to not observe the whole process. If our aim is to mitigate the duration of symptoms and reduce the burden of symptom load, with all its impacts on HCPs’ and patients´ safety, addressing all support measures, not only the top-ranked measures, might be highly important.
We also observed that if help is not provided, even when it is requested, we demonstrated markedly elevated odds for symptom persistence and burden of symptoms. However, these results should be interpreted with caution, as unmeasured confounding factors may influence group comparisons. The limitation of these findings is the rather wide CI interval, suggesting a rather lower precision of the odds ratio. However, the risk of greater symptom load in the case of poor colleague support is in line with findings from the SeViD IX pilot study, which revealed that colleague support decreases symptom load, as long as physical distress is low. In high distress, colleague support of any kind did not [26]. Therefore, our findings reinforce the need for second victim support programs, especially those asking for help, and those who are being asked first—these are colleagues and peers better available to a second victim. Conclusively, these persons have to be educated regularly in “first aid skills” to act appropriately on second victims (and themselves). With respect to anaesthesia, this applies to all professionals.
Implications for Policy and Practice: Given the high prevalence and profound impact of SVP, healthcare institutions must take proactive steps to address the needs of second victims. For this purpose, the European Researchers’ Network Working on Second Victims (ERNST) has proposed a five-level model of support that includes (1) Prevention (individuals/organizations), (2) Self-care (individual/team), (3) Peer support, (4) Professional support and (5) Structured clinical support [27].
Currently, empirical data on the effectiveness of second-victim (SV) programs are limited. A meta-analysis by Anger et al. demonstrated that intervention programs positively influence the mental health of healthcare professionals [20]. Common features of these programs include raising awareness about the second victim phenomenon, establishing professional peer support systems, and incorporating higher levels of care [28, 29].
Limitations and Future Research: While our study provides initial valuable insights, it has certain limitations. The use of self-report surveys and the recruitment of participants in a conference setting may introduce self-selection bias. Participation was voluntary and may have particularly attracted anesthesiologists already engaged with the topic or who were more willing to share their experiences. This limits the representativeness of the sample and may affect the generalizability of the results. Conversely, the survey could not reach those who had already left practice due to the effects of being a second victim.
Another limitation is that the sample appears to overrepresent experienced clinicians (mean age 50.8 years, mean of 21.5 years of experience). A cumulative effect on the development of the Second Victim Phenomenon with increasing professional experience is plausible because of greater exposure to critical incidents over time. However, resilience and adaptive coping may also increase with experience. In support of these effects, a previous study revealed that even among young physicians with an average of 4 years of experience, 59% had already experienced one or more SV incidents [18].
Furthermore, social desirability and self-awareness may have influenced responses to the item regarding second victim status. On the other hand, when asked whether they had ever heard of the second victim phenomenon, 48% reported that they had never heard of it.
In contrast to other European countries, German anesthesiologists working in different medical fields (e.g., operating theatres, intensive care medicine, in-hospital and out-of-hospital emergency medicine, pain therapy, and palliative care) should be compared with anesthesiologists in other nations with caution and remain to be explored in more detail. Although we adjusted for the workplace, interactions that do not exist in other countries may be prevalent. Additionally, and as intended, our work is explorative without adjusting for multiplicity and with subtests with partially low sample sizes. Consequently, confirmatory research in larger populations is needed for the specification of risk factors and dependency in different working fields. Future research should explore the longitudinal outcomes of second victims, investigate the efficacy of institutional interventions, and examine the role of workplace culture in modulating SVP experiences.

Comments (0)