2.1 Study Design and Patients
The study design and patients are described in detail in our previous publications [22, 23]. Briefly, this double-blind, randomised, controlled trial was conducted at 11 hospitals in Australia and included patients aged 18 years or older and without known MRSA colonisation. Patients were excluded if they were hypersensitive to cefazolin or glycopeptides, were pregnant/lactating, or were undergoing surgery for suspected or proven SSIs or for emergency or time-critical indications. A total of 4239 patients were randomised in a ratio of 1:1 to either receive 1.5 g (for body weight ≥ 50 kg) or 1 g (for body weight < 50 kg) of intravenous vancomycin (the intervention) or placebo (the comparator) in addition to 2 g of intravenous cefazolin as surgical antimicrobial prophylaxis. Recruitment began on 15 January 2019, and the patients were followed for 180 days after the arthroplasty (index surgery), and the primary outcome of the study was the occurrence of any SSI during the first 90 days. A total of 4113 patients were included in the modified intention-to-treat cohort, with 2044 receiving vancomycin and 2069 receiving placebo. Differences in baseline continuous variables between the treatment groups were assessed using Welch’s t tests. Associations between categorical variables and treatment group were assessed using χ2 tests; Fisher’s exact test was used when expected frequencies in any cell of the contingency table were < 5.
2.2 Follow-Up Procedure
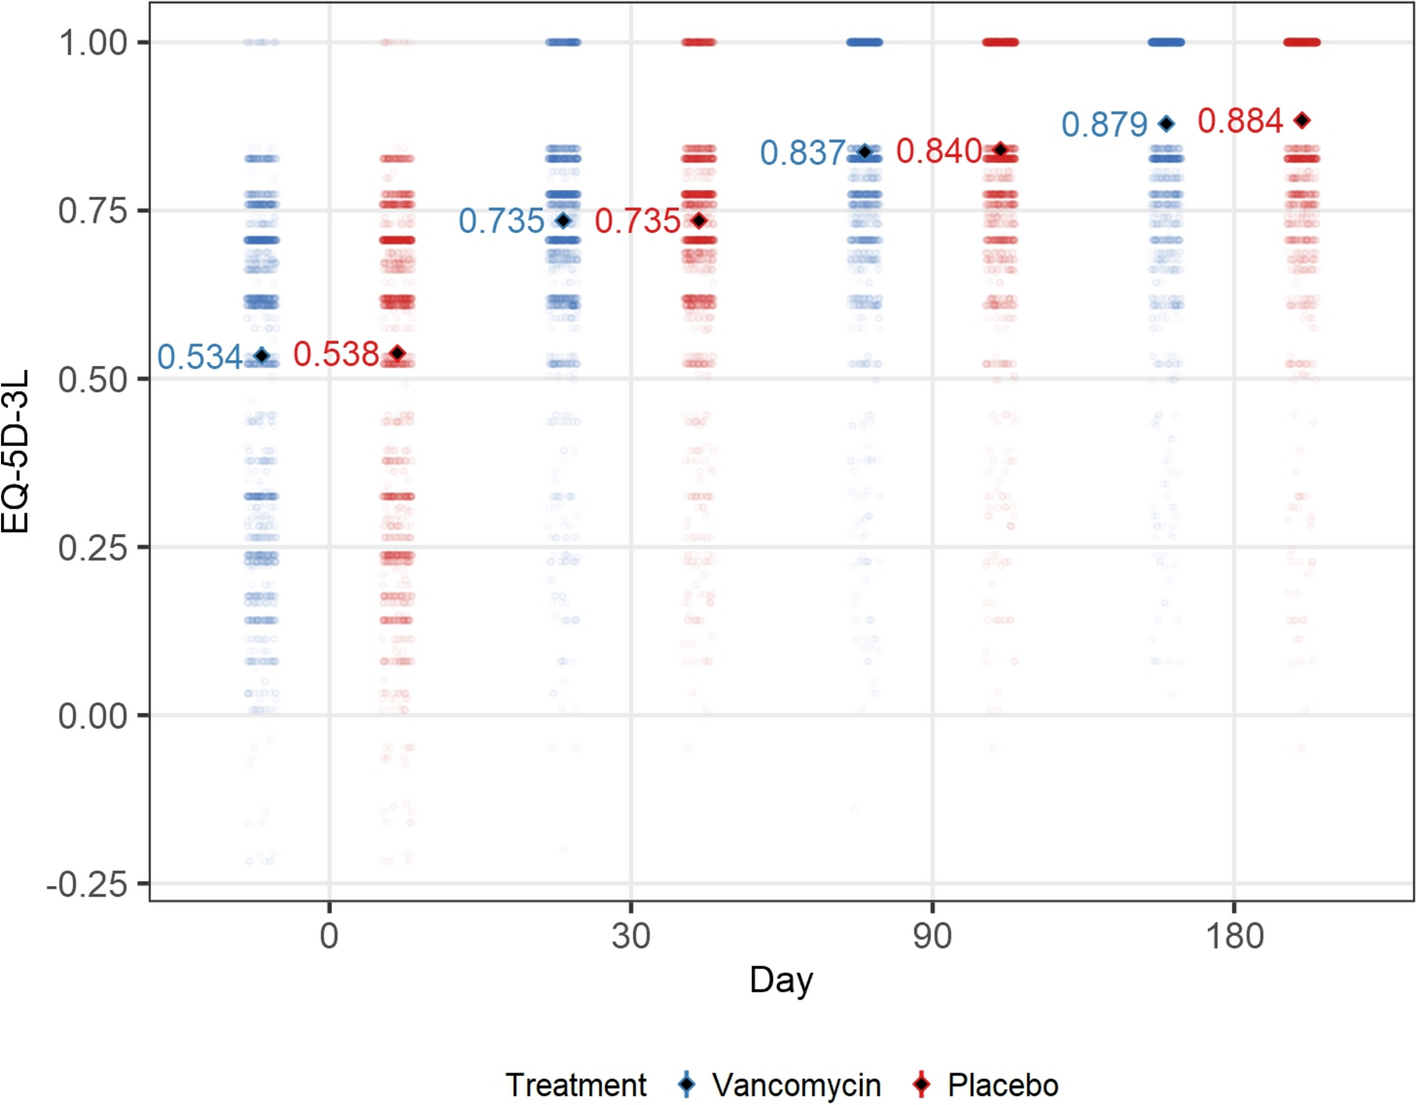
In the original trial, the longest follow-up period was 180 days. This duration was intended to capture both early and delayed postoperative complications, including SSIs and hospital readmissions, which most commonly occur within the first six months following arthroplasty. Patients were assessed at baseline (time after informed consent received and before surgery) and 30 days, 90 days, and 180 days after the index surgery. At baseline, demographic variables, height and weight, and diabetes status were collected, and screening for MRSA was conducted. Patients completed the EQ-5D-3L questionnaire at every assessment and underwent procedures for identifying SSIs and other adverse events during the follow-up period. Patients’ use of non-hospital healthcare services, including visits to general practitioners, medical specialists, allied health professionals (e.g. physiotherapists), nursing services, social workers, and diagnostic pathology, was ascertained from Medicare Benefits Schedule (MBS) claims data. Medication use was captured from Pharmaceutical Benefits Scheme (PBS) dispensing records. Hospital costs were derived from hospital administrative data provided by participating hospitals. The MBS and PBS data were individually linked to the trial participants by Services Australia (https://www.servicesaustralia.gov.au/) using personal identifying information. The hospital administrative data were individually linked to the trial participants by the participating hospitals using unique identification numbers.
2.3 Cost-Effectiveness Analysis
The health economic analysis plan was briefly outlined in our trial protocol publication [23]. Our analysis was from the healthcare sector perspective, which included healthcare costs incurred by both government and patients. Healthcare costs (in Australian dollars [AU$]) and outcomes were evaluated over a 180-day follow-up period. Treatment costs for each patient, either intravenous vancomycin and intravenous cefazolin, or placebo and intravenous cefazolin, were estimated based on the prices published by the PBS (Supplementary Table S1 in the electronic supplementary material) for one vial of vancomycin 500-mg injection [24] and the per-vial cost of cefazolin 2-g injection, derived from the PBS price for a ten-vial pack [25]. Because there were two different prices for vancomycin (AU$22.07 and AU$34.97), we used the published number of PBS services (i.e. the number of times the medicine was supplied under the PBS) associated with corresponding prices [26] over the study period (from 15 January 2019 to 13 May 2022) as weights to calculate the weighted average price of one vial. The cost of vancomycin for each patient was based on the weighted average price of one vial and the number of vials of vancomycin 500-mg injection needed (i.e. three vials for body weight ≥ 50 kg and two vials for body weight < 50 kg). There was only one price for one vial of cefazolin 2-g injection (AU$4.67), and this was used for every patient.
Non-hospital costs were calculated using costs incurred by the Medicare and patients’ out-of-pocket costs for services or medications recorded in the MBS and PBS datasets. Hospital costs were calculated based on charges to patients from hospitals participating in the trial for readmissions during the follow-up periods. All costs were adjusted to values in 2022, the final year of the study period, using consumer price indices published by the Australian Bureau of Statistics (ABS) [27].
Responses of patients to the EQ-5D-3L questionnaire were converted into health utilities using the Australian value set for the EQ-5D-3L [28]. Health utility represents patient’s HRQoL weighted by the population’ preference for a health state, typically valued on a scale from 0 (representing death) to 1 (representing perfect health). Health utilities collected at different time points were used to estimate quality-adjusted life years (QALYs) corresponding to the 180-day follow-up period for each patient. Because distributions of SSI counts, health utility, QALYs, and costs were skewed and/or multimodal (see Supplementary Figs. S1–S8 in the electronic supplementary material), we used bootstrap with the bias corrected and the accelerated method, and with 10,000 replications to estimate their means, standard deviations (SDs), and 95% confidence intervals (CIs), as well as the differences in mean values between the vancomycin and placebo arms and 95% CIs of the mean differences [29]. When normal distribution assumptions are violated, as was the case in our study, the bootstrap method is recommended to provide more accurate estimates of 95% CIs compared with parametric methods [30]. In addition, bootstrapping is the standard approach for estimating uncertainty around incremental costs and incremental QALYs, for which analytical variance estimates are not straightforward [30]. Furthermore, bootstrapping was required in trial-based cost-effectiveness analysis for the probabilistic uncertainty analysis used to construct the cost-effectiveness plane and the cost-effectiveness acceptability curve (CEAC; see next section) [30].
The percentages of participants who completed the EQ-5D-3L at baseline and at 30, 90, and 180 days were 99.98%, 96.45%, 95.53%, and 95.48%, respectively. Cost data were available for all patients. Given the very large sample size and the minimal amount of missing data, analyses were conducted using complete cases. As the time horizon of the analysis was less than 1 year, neither costs nor health outcomes were discounted.
2.4 Uncertainty Analysis
To assess uncertainty, 10,000 bootstrap replications of incremental mean costs and QALYs were plotted on the incremental cost-effectiveness plane. Each quadrant of this plane represents a different scenario: north-west (more costly, less effective), north-east (more costly, more effective; cost-effectiveness depends on a willingness-to-pay [WTP] threshold), south-east (less costly, more effective), and south-west (less costly, less effective; cost-effectiveness depends on a willingness-to-accept [WTA] threshold). The proportion of replications in each quadrant indicates the probability of the intervention falling into that scenario. The WTP threshold represents the maximum amount of money that the population is willing to pay for one additional QALY, and the WTA threshold represents the minimum saving that the population is willing to accept for one QALY lost. In Australia, the national guidelines for economic evaluation published by the Pharmaceutical Benefits Advisory Committee (PBAC), the body that advises the Minister for Health on subsidy decisions under the PBS, do not specify an explicit WTP or WTA threshold. Instead, PBAC adopts a deliberative approach to assessing value for money, in which the incremental cost-effectiveness ratio (ICER) is considered alongside other factors such as clinical significance, uncertainty, disease severity, and budget impact.
Nevertheless, empirical analyses of PBAC decision-making suggest the existence of an implicit cost-effectiveness threshold. In an analysis of 858 PBAC submissions, the mean ICER among all submissions was approximately AU$46,000 per QALY gained, and an increase of AU$10,000 in the ICER was associated with a 0.06 reduction in the probability of a positive reimbursement recommendation [31]. While no formal threshold is recommended, this and other studies indicate that interventions with ICERs below approximately AU$50,000 per QALY gained are more likely to be considered cost-effective in the Australian context [32, 33]. In our study, we adopted a WTP/WTA threshold of AU$50,000 per QALY gained/lost.
We used the net monetary benefit (NMB) framework [34] to determine whether the intervention was cost-effective at different WTP or WTA thresholds:
$$\text=\text\times \lambda -\text$$
where \(\text\) and \(\text\) are incremental QALYs and incremental cost, respectively, and \(\lambda\) is the WTP or WTA threshold. If NMB is positive, the intervention is cost-effective and if NMB is negative, the intervention is not cost-effective. For simplicity, we assumed that that WTP and WTA thresholds were equal. The CEAC was constructed by calculating the proportion of bootstrap replications with a positive NMB at each WTP or WTA threshold, representing the probability that the intervention is cost-effective at that threshold. The probability that the intervention is not cost-effective was calculated as one minus this probability. WTP/WTA thresholds were increased from zero until the CEAC reached a stable region, beyond which further increases resulted in negligible changes in the estimated probability of cost-effectiveness.
2.5 Software and Analytical Implementation
All data handling, statistical analyses, cost-effectiveness analysis, and uncertainty analysis were conducted using R (version 4.5.0) [35].


Comments (0)